Children’s Health Defense embarked on a nine-month journey across America, gathering powerful testimonies from the people. Our interviews ranged from mothers and fathers to teenagers, families, medical professionals, whistleblowers, lawyers, and people from all walks of life.
What we discovered was nothing short of staggering. We listened to harrowing accounts of COVID hospital protocols that shook us to our very core. The consistency of these stories was alarming.
People also shared their experiences after taking the COVID-19 vaccine, revealing tragic outcomes of either death or serious injury. Now, fueled by these powerful firsthand testimonies, we are creating a documentary by the people, for the people.
Learn what we uncovered on the road. You can’t afford to miss it.
A long history exists of a wave of severe injuries following new vaccinations being introduced to the market. In most cases, those injuries were swept under the rug to protect the business.
In many cases, the severe “mysterious” injuries we see now are remarkably similar to those that were observed over a century ago. Unfortunately, a widespread embargo exists on ever allowing this data to come to light (as that would instantly destroy the vaccine program).
A variety of independent studies (summarized below) have shown that vaccines cause a wide range of chronic illnesses.
A 1990 book made a strong case that widespread vaccination was also causing an epidemic of widespread brain damage which was both lowering America’s IQ and causing a massive rise in violent crime.
In this article, we will also review exactly what in that 1990 book and the classic signs that can be used to determine if someone has a vaccine injury (along with the subtle more spiritual ones).
Note: due to the recent ACIP changes (the committee which decides which vaccines you take) and past interest in this article, I revised and updated it.
My mind often overlaps the past present and future onto themselves. Because of this, I will frequently recall events that happened in the past which perfectly mirror what is unfolding before us, and in turn, I’ve lost count of how many times I’ve witnessed humanity repeat its same mistakes or can see a slow motion train-wreck ahead on the horizon. During COVID, I realized we were again reenacting the same tragedy humanity had ever experienced since the smallpox vaccine was brought to the market and I had a thought. If people became aware of what had happened before and ended our collective amnesia, perhaps this could at last stop.
As fate would have it, my wish came true, and without knowing me, Steve Kirsch gave me the opportunity to begin introducing that forgotten history to the world. This happened after he chose to publish an article I wrote illustrating how the trucker protests were identical to smallpox protests that had happened more than a century before and then for reasons I still do not understand, encouraged his readers to subscribe to me so I would start writing here. Note: At the time I chose the username “A Midwestern Doctor” (for the smallpox article), I did not put much thought into it as I was never expecting to use it again.
Over the years, I’ve noticed again and again that a vaccine disaster happens which injuries many in a very similar way, it gets swept under the rug (often by officials who are quite conflicted in their decision to do so), and then the same thing happens again a few decades later.
Given that we give dozens of vaccines to each member of society, this raises an obvious question—what is that doing to society?
The Forgotten Side of Medicine is a reader-supported publication. To receive new posts and support my work, consider becoming a free or paid subscriber. To see how others have benefitted from this newsletter, click here!
A Brief History of Vaccine Disasters
In 1798, the smallpox vaccine hit the market. Once it hit the market, it was observed to frequently cause smallpox outbreaks (rather than prevent them) and to cause a wide range of debilitating and complex injuries that many of the doctors had never seen before (and many of which I believe were examples of “blood stasis”). Curiously, rather than recognizing this was a mistake, most of the medical profession endorsed the smallpox vaccine, and governments around the world mandated it as cases kept on increasing, leading to a downward spiral that was eventually broken by mass public protest against those mandates. Having looked at it extensively, I am of the opinion the smallpox vaccine reshaped the trajectory of humanity’s health and was an inflection point in the era of chronic illness.
In the 1800s and early 1900s, a variety of early vaccines (e.g., rabies, typhoid, diphtheria, tuberculosis) and horse-generated antiserums (for most of the common infections at the time) entered the market. Since many of these vaccines were produced in small independent labs, there were a variety of quality control issues with these products, which frequently led to hot lots being released that severely injured or killing a group of people. Additionally, many of those vaccines had a high degree of toxicity. Because of this, a variety of new and severe medical conditions emerged, many of which were deemed to be due to brain inflammation (encephalitis) or brain damage (encephalopathy) and observed to occur in conjunction with cranial nerve damage. Most of these conditions (which I discussed in detail here) in turn mirrored the myriad of injuries we now too see from modern vaccinations. In addition to the injuries, two major issues stood out during this period:
•First, in addition to sometimes being directly contaminated with the disease causing organism (e.g., yellow fever or tuberculosis) and causing the illness, vaccines would often cause a temporary immune suppression which lead to disease outbreaks in those vaccinated (discussed here). However, each time this happened, rather than it being seen as a sign we needed to dial back vaccination, it was interpreted as not enough people being vaccinated and harsher and harsher vaccine mandates being instituted to enact that policy or new vaccines being created to address the existing damage of vaccination (e.g., the DPT vaccine frequently caused polio outbreaks).
•Second, public health officials and vaccine designers were well aware of the injuries vaccines were causing, but since no other treatments existed for the disease, regrettably deemed this to be a necessary sacrifice for the greater good and hence covered the injuries up so the public would continue to vaccinate. However, while I understand their perspective, it rested on a faulty premise—effective treatments did exist for the illnesses (e.g., in 1920 it was known IV hydrogen peroxide could treat severe infections and in 1928 it was known that ultraviolet blood irradiation could treat many otherwise incurable infections). Note: as you might have noticed, everything I just described also applies to the COVID-19 vaccines, hence illustrating how these dysfunctional cycles frequently perpetuate indefinitely.
In the 1940s-1950s, the original pertussis vaccine (DPT) entered the market. This vaccine excelled at causing brain inflammation and a variety of concerning differences were seen in the generations born after its mass adoption in America. Note: The rabies vaccine also excelled at causing encephalitis (around 1 in 750 injections, of which 20% were fatal), but it did not have as large an impact on society because far fewer people received it.
Between the 1950s to 1970s, numerous instances happened where a rushed and poorly produced experimental vaccine (e.g., polio or the swine flu) was brought to market to address a non-existent “emergency,” and the government chose to ignore warnings from its scientists that it was not safe to give to America. Since the press was honest at this time, they reported the disaster, it became a national scandal and the government provided compensation to the victims. Note: I compiled those media reports here, the last of which happened in 2002 with Bush’s smallpox vaccine.
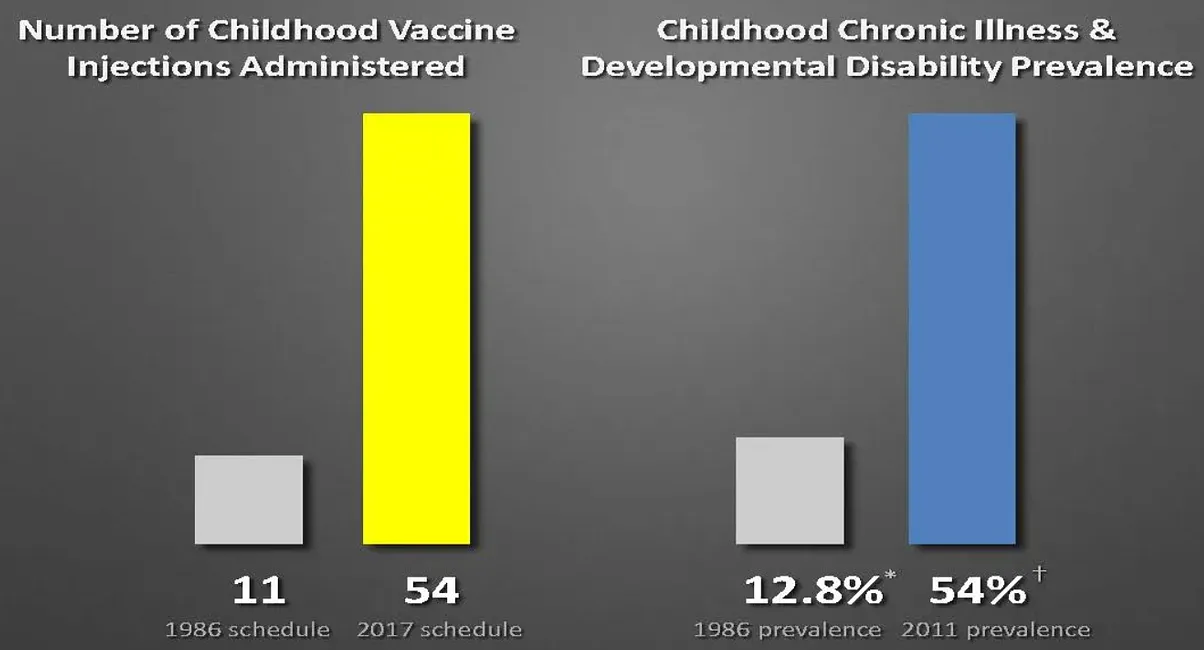
In 1986, enough public awareness existed of the dangers of the DPT vaccine that lawsuits were regularly being filed for the brain damage and sudden infant deaths it caused (discussed here). This in turn led to the 1986 vaccine injury act being passed (discussed further here), an act that both shielded vaccine manufacturers from product liability and was intended to help parents of vaccine injured children (even though it didn’t due to selective enforcement of its provisions and the Supreme Court exempting manufacturers from injuries caused by defective vaccines). This act being passed led to an industry gold rush to bring experimental and liability free vaccines to the market, and before long the childhood vaccination schedule ballooned in parallel to chronic illnesses increasing as well.
Note: since this time other vaccines (e.g., RSV and annual COVID vaccinations) were also added to the childhood schedule (but fortunately MAHA managed to recently do the impossible and remove COVID from it).
In 1990, an experimental anthrax vaccine was deployed upon the military to prepare them for invading Iraq. While the war was non-eventful (Saddam did not use anthrax and it was likely the most one-sided conflict in history), the anthrax vaccine severely injured over 100,000 servicemen (leading to what was known as Gulf War Syndrome). Despite these issues, individuals within the Department of Defense who were committed to funding their bioweapons defense program mandated it—leading to severe injuries throughout the military and widespread rebellion against this edict.
After this, new biotechnologies began emerging which made it possible to genetically engineer a plethora of new vaccines that then began to flood the market as ACIP endorses virtually every vaccine given to them regardless of its merits (in fact, throughout their dozens of endorsements I could only identify one case where ACIP did not [boosters for teachers and healthcare workers], and in that instance the CDC simply overrode ACIP). In tandem, direct to consumer pharmaceutical advertising was legalized by a 1997 FDA decision, making it possible for the pharmaceutical industry to buy the mass media’s silence, and hence end all future coverage of vaccine injury.
In 2010, Merck convinced America’s women they were at a high risk of dying from cervical cancer (which in reality only kills about 1/38,000 American women each year) so that everyone would buy their highly lucrative vaccine (which was never proven to reduce cervical cancer deaths). This vaccine had an extraordinarily high rate of injuries (e.g., severe autoimmune disorders), but nonetheless, despite a deluge of complaints, the CDC and FDA did everything they could to protect it, and to this day it is still mandated for children.
In 2021, the COVID vaccine hit the market and caused an unprecedented amount of injury (e.g., many noticed healthy adults dying “suddenly” and large polls showed 34% of vaccine recipients reported minor side effects while 7% reported major ones severely impacting their quality of life). Fortunately or unfortunately, the rate of injuries from it was so high that unlike the past disasters, the mass media could no longer sweep it under the rug, which eventually culminated in MAHA ascending as a political force and RFK Jr. being put in charge of the agency which has orchestrated the vaccine disaster for decades.
In my eyes, one of the most important points to take from this history is that at the time each of these happened, the medical profession and public were struck by the explosion of these new diseases (and their immense social cost) but before long, became acclimated to them and forgot they had ever emerged in the first place.
The Harms of Vaccination
There is a large body of evidence suggesting vaccines are either solely responsible for, or one of the primary things responsible for the tsunami of chronic illness which has followed their ever-increasing adoption.
Unfortunately, while there is a great deal of evidence suggesting a problem exists, the effects of the vaccine schedule have never been formally studied and instead concerns are simply dismissed by a chorus that echoes “vaccines are safe and effective.”
This has naturally led to calls for the vaccines to be formally tested, but this is always rejected under the argument that vaccines are “so safe and effective” it would be ‘unethical’ to withhold them from trial participants who need to receive a placebo and expose them to the severe harm vaccine preventable diseases could cause (despite the fact very few of the vaccines on the market are for life-threatening diseases which still exist within the United States).
As such, to get around this embargo, a variety of independent studies (which all faced stiff opposition) have been completed that compared unvaccinated populations to vaccinated ones, all of which show profound harm results from vaccination. However, rather than be listened to, these studies are all dismissed because they “have no placebo” (despite placebo trials being impossible to conduct). Note: this highlights why the vaccine industry was so shaken up by RFK exposing this grift by now requiring proper placebo testing for new vaccines.
In lieu of placebo trials, we are instead told large databases can be relied upon to monitor for vaccine injuries. However, with the exception of VAERS (which is continually discredited by the media, government and medical profession), all of those databases are secret to the point the government has fought for years in court to protect their release (e.g., “to protect patient privacy”) and told us to trust their assessments of them.
Note: through a series of lawsuits, we were able to get access to some of the CDC’s V-Safe data on the COVID vaccines. In addition to this showing massive harm from the COVID vaccines, access to the raw data also showed that the Lancet summary of V-Safe’s data had distorted it to provide an illusion of safety not shown by the data.
Access to the CDC’s vaccine injury database (the VSD) hence has been a longstanding goal of the vaccine safety community and one of the things RFK pledged to do if he ever assumed office. Remarkably however, right before he got access to it “rouge” H.H.S. employees decided to delete it to prevent this from happening.
All of this hence suggests that either:
No evidence exists of the harms of vaccination and it has simply not been a priority to formally publish that data (which is odd given how much effort blocking all the lawsuits and petitions requesting it takes).
There is some evidence vaccines are harmful, and there are concerns this data could be misinterpreted to suggest vaccines are much more harmful than they are.
The existing evidence shows that vaccines are incredibly dangerous to the point it is an existential threat to the vaccine program and hence all measures possible have been taken to prevent it from being disclosed.
As you might guess, I believe the latter is the most probable, particularly since:
Numerous clinical trials of individual vaccines show that vaccines cause many of the same disorders that have risen in parallel with increased vaccination (e.g., the HPV vaccine caused at least 2.3% of trial participants to develop an autoimmune disorder. Note: there are numerous cases reports of children becoming permanently disabled after receiving a higher than normal number of vaccines simultaneously (e.g., at a visit where they also get caught up on missing doses), and conversely, many have observed spacing vaccines out rather than giving them all together lowers the likelihood of a severe reactions (e.g., autism) from vaccination.
Despite relentless attempts to keep them from emerging, there are numerous retrospective studies of large medical datasets which each show vaccination results in a significantly increased incidence of chronic disease results from vaccination. For example, a recent study of 99 million people showed the COVID vaccines were 2-7 times more likely than a typical vaccine to cause a variety of life-threatening illnesses and we now have large datasets linking to the COVID vaccines to many conditions like myocarditis, cognitive impairment, along with many autoimmune, musculoskeletal and psychiatric disorders.
Established mechanisms exist to explain how many different vaccines could all cause similar injuries to their recipients (each of which are discussed here).
I periodically learn of medical practices that have low rates of vaccination and also have much lower rates of chronic illness in their patients.
Many colleagues and I frequently observe what we believe to be the harms of vaccination in our patients.
Note: I personally know many trained observers who can have a high degree of accuracy in identifying unvaccinated children. The approaches they use are discussed at the end of this article.
Vaccine Injury Datasets
Despite the embargo on conducting or publishing studies demonstrating evidence of vaccine harm, a few still have been done. They are as follows:
Paul Thomas
Paul Thomas MD, an Oregon pediatrician had a practice with a large number of unvaccinated or under-vaccinated children, and (like many of the other practices with similar patient populations) noticed that the unvaccinated children had dramatically better health. He thus decided to compare their medical records to those of variably vaccinated children and published the data in a study (which, as you are not supposed to violate that embargo, cost him his medical license and resulted in the study being retracted for spurious reasons).
Note: Paul Thomas (now retired and offering coaching services to parents) was also the author of The Vaccine Friendly Plan, an approach to vaccinating that encouraged spacing out vaccinations and resulted in a dramatically lower rate of vaccine injuries. Since his plan implied the current vaccination schedule promoted by the CDC was not safe, his plan was not popular with the medical authorities (which again illustrates the harm of the “safe and effective” dogma, as if dangers were to be acknowledged, far fewer people would be injured).
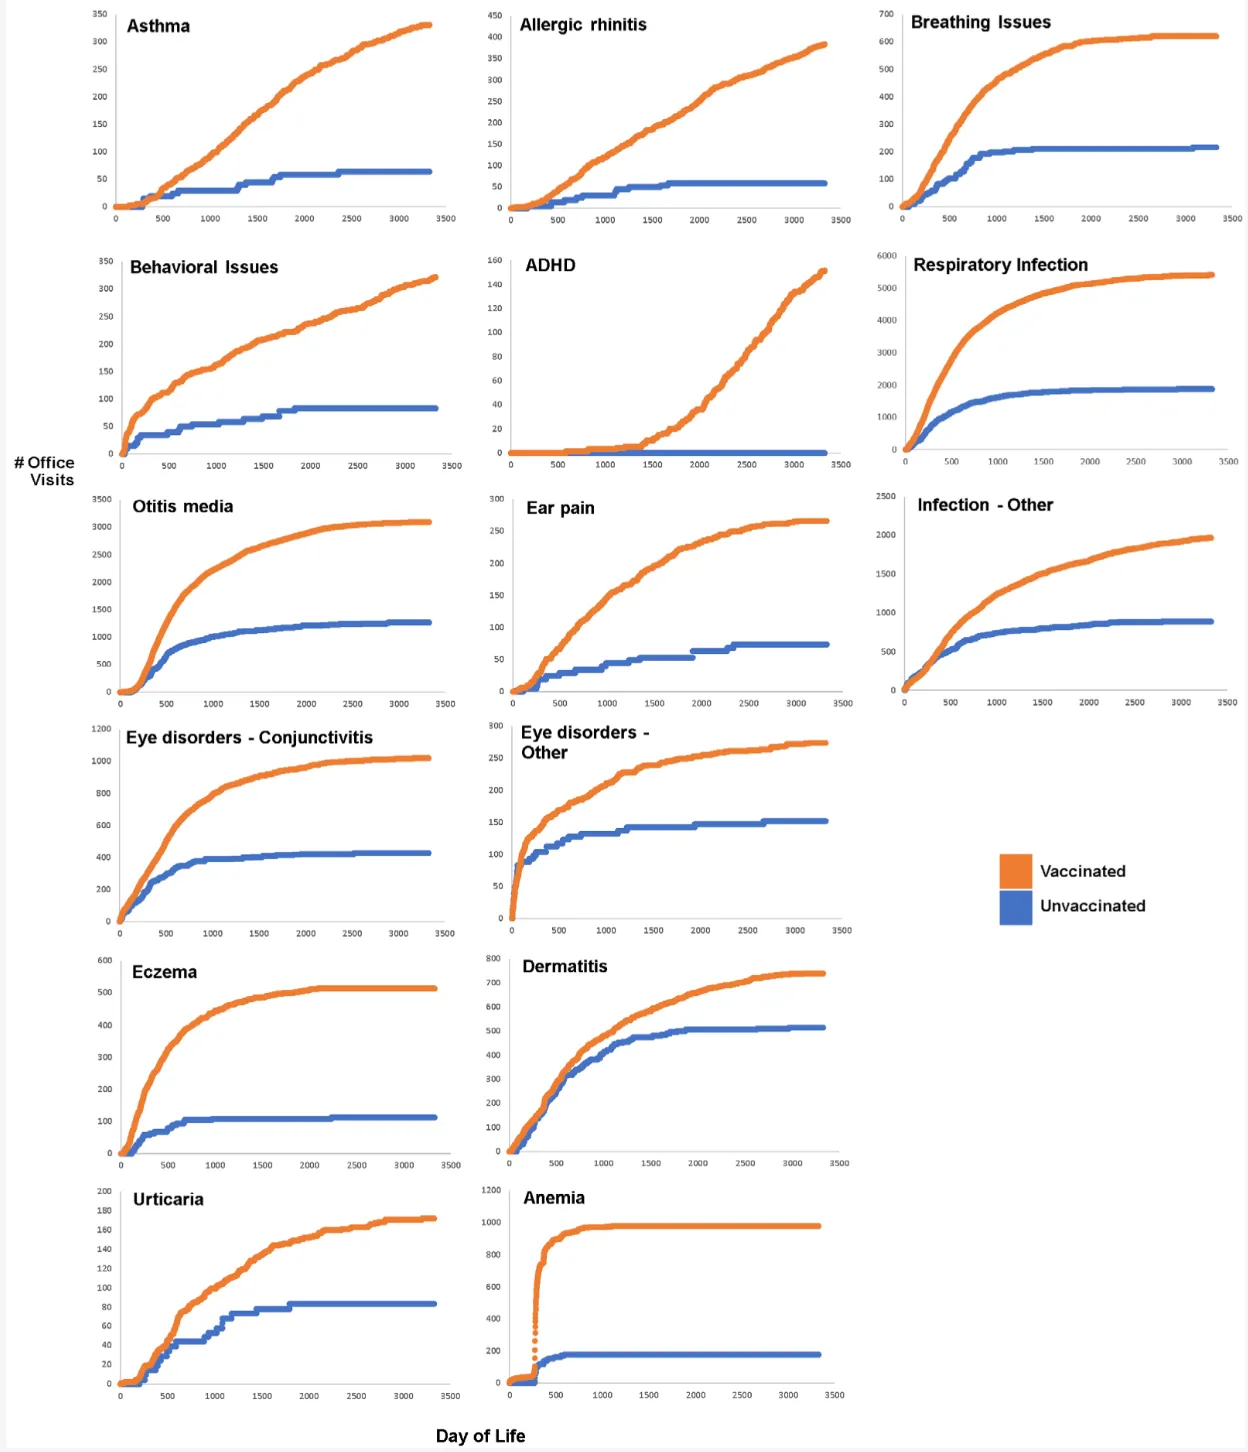
In his study, to compare the health of 2763 vaccinated children and the 561 unvaccinated children born into his practice, he plotted how many total visits each group had for a variety of issues as their age increased (e.g., how many visits for asthma in total had occurred in vaccinated children who were 1000 days old or younger) and then compared the two (with the unvaccinated group’s visits being equalized by multiplying them by 4.9 [2763/561]). This data in turn suggested vaccinations were the primary agent responsible for the epidemic of chronic diseases in our society.
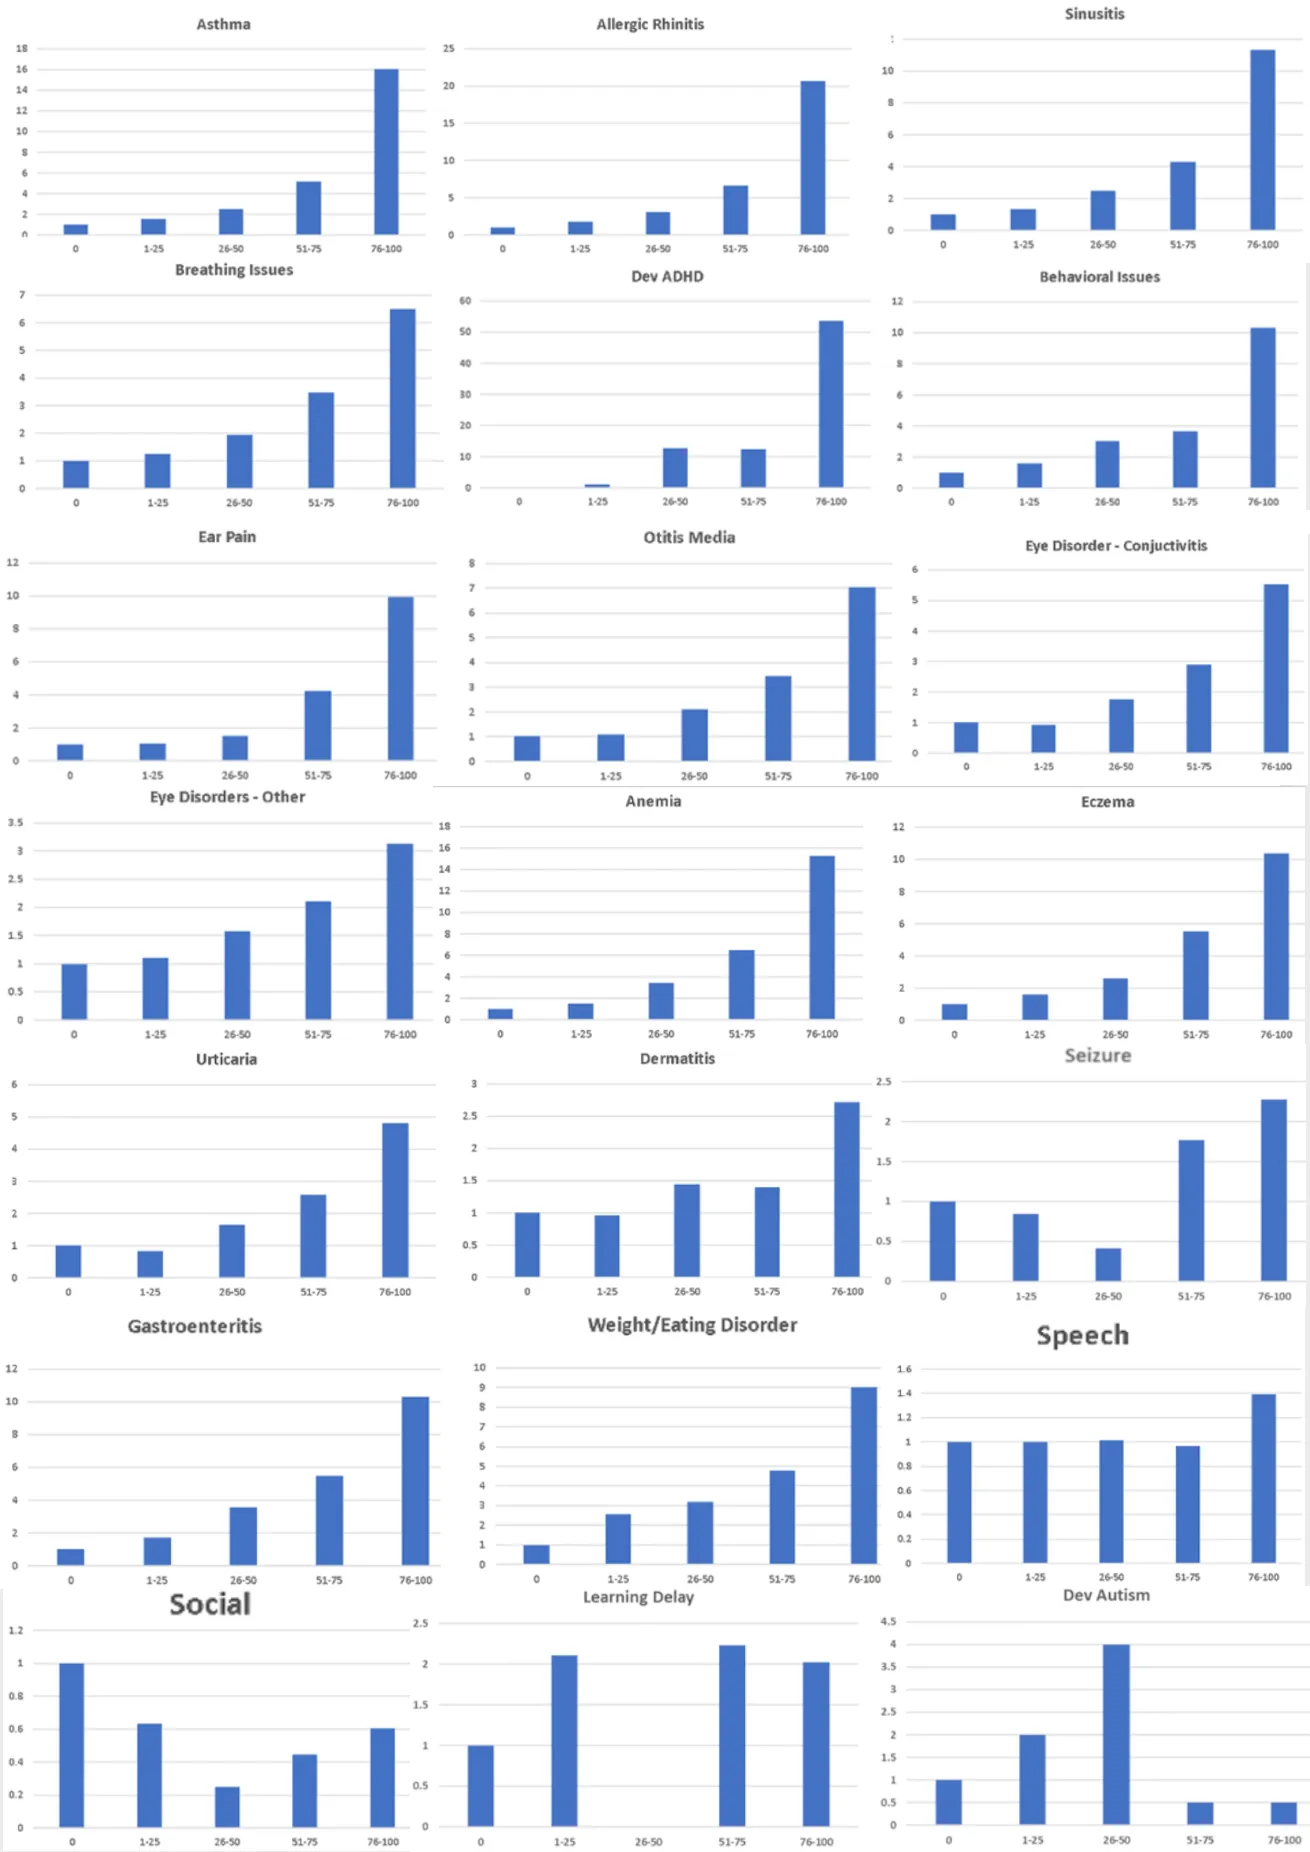
Likewise, when Thomas compared how likely a child was to come in for an office visit for a variety of health concerns, he found the greater the number of total vaccines a child received (which varied widely in his practice), the more likely they were to require an office visit for a variety of conditions.
Note: the full size version of this chart can be viewed here. In this chart, pay special attention to the fact these charts include ADHD (which was not found in any of the unvaccinated patients), behavioral issues, speech issues, social issues, learning delay and developmental autism.
Brian Hooker and Neil Miller
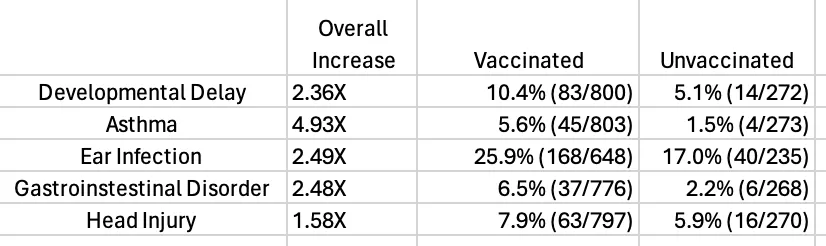
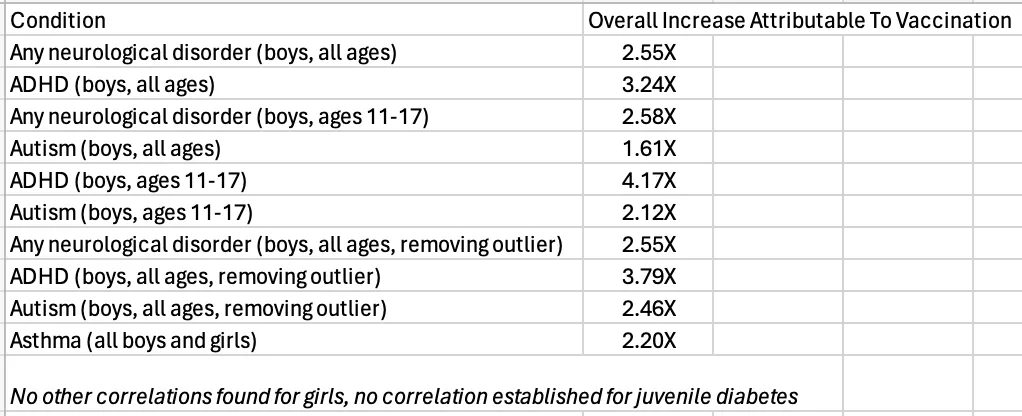
Hooker and Miller performed a similar study to Paul Thomas. However, in their study, they evaluated data from 3 different pediatric practices, and analyzed the 2,047 who had been born within the medical practice between November 2005 to June 2015 that had not received one of the selected diagnoses prior to their 1st birthday. They found:
Note: the above chart only compares the children within the sample who were at least 5 years old. When younger children were compared to each other, smaller increases were seen in the rates of each of these chronic diseases as there had been less time for the chronic effects of repeated vaccinations to manifest (which helps to explain why vaccines studies stop monitoring for side effects shortly after vaccination).
The stark differences in the rates of adverse injuries (and lack of chronic illness in groups like the Amish who do not vaccinate) have also inspired a variety of independent surveys to be commissioned which assessed if this link indeed exists. It should also be noted that there is a viable mechanism that ties almost every condition listed in this section to vaccination. Note: I reformatted most of the surveys that follow to make their data easier to see.
The 2007 Generation Rescue survey
In 2007, Generation Rescue (GR), an organization that is trying to alert Americans that vaccines cause autism, hired a third party polling firm (SurveyUSA) and paid them $200,000 to do a survey of 17,674 children (991 of whom were completely unvaccinated). It found:
The Homeschool Survey
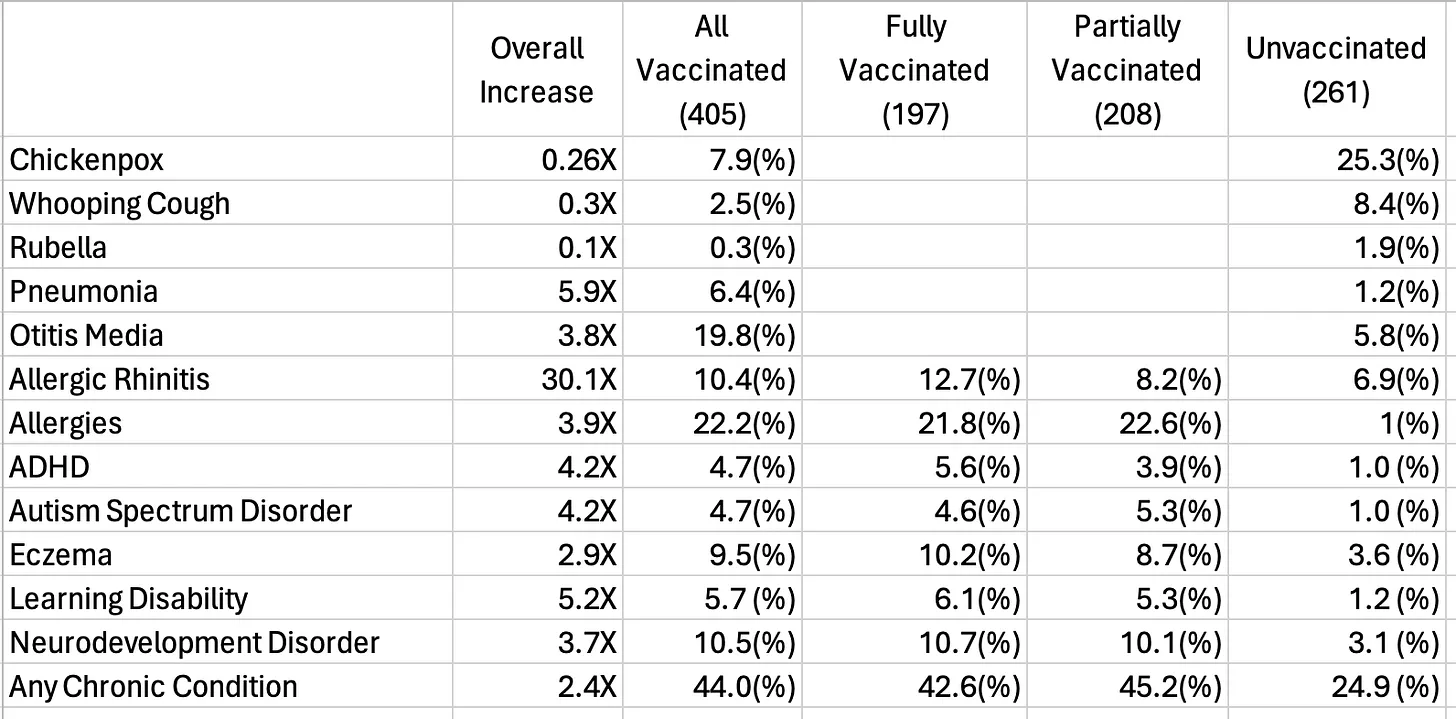
In 2017, a survey of mothers of homeschooled children from Florida, Louisiana, Mississippi and Oregon was carried out and then published. Since there are a significant number of unvaccinated children who homeschool, it was possible to compare 261 unvaccinated children to 405 fully or partially vaccinated children. Its results were as follows:
Note: since the three illnesses vaccination were supposed to prevent decreased (whereas the others increased), that data supports the validity of this survey.
The Control Group Survey
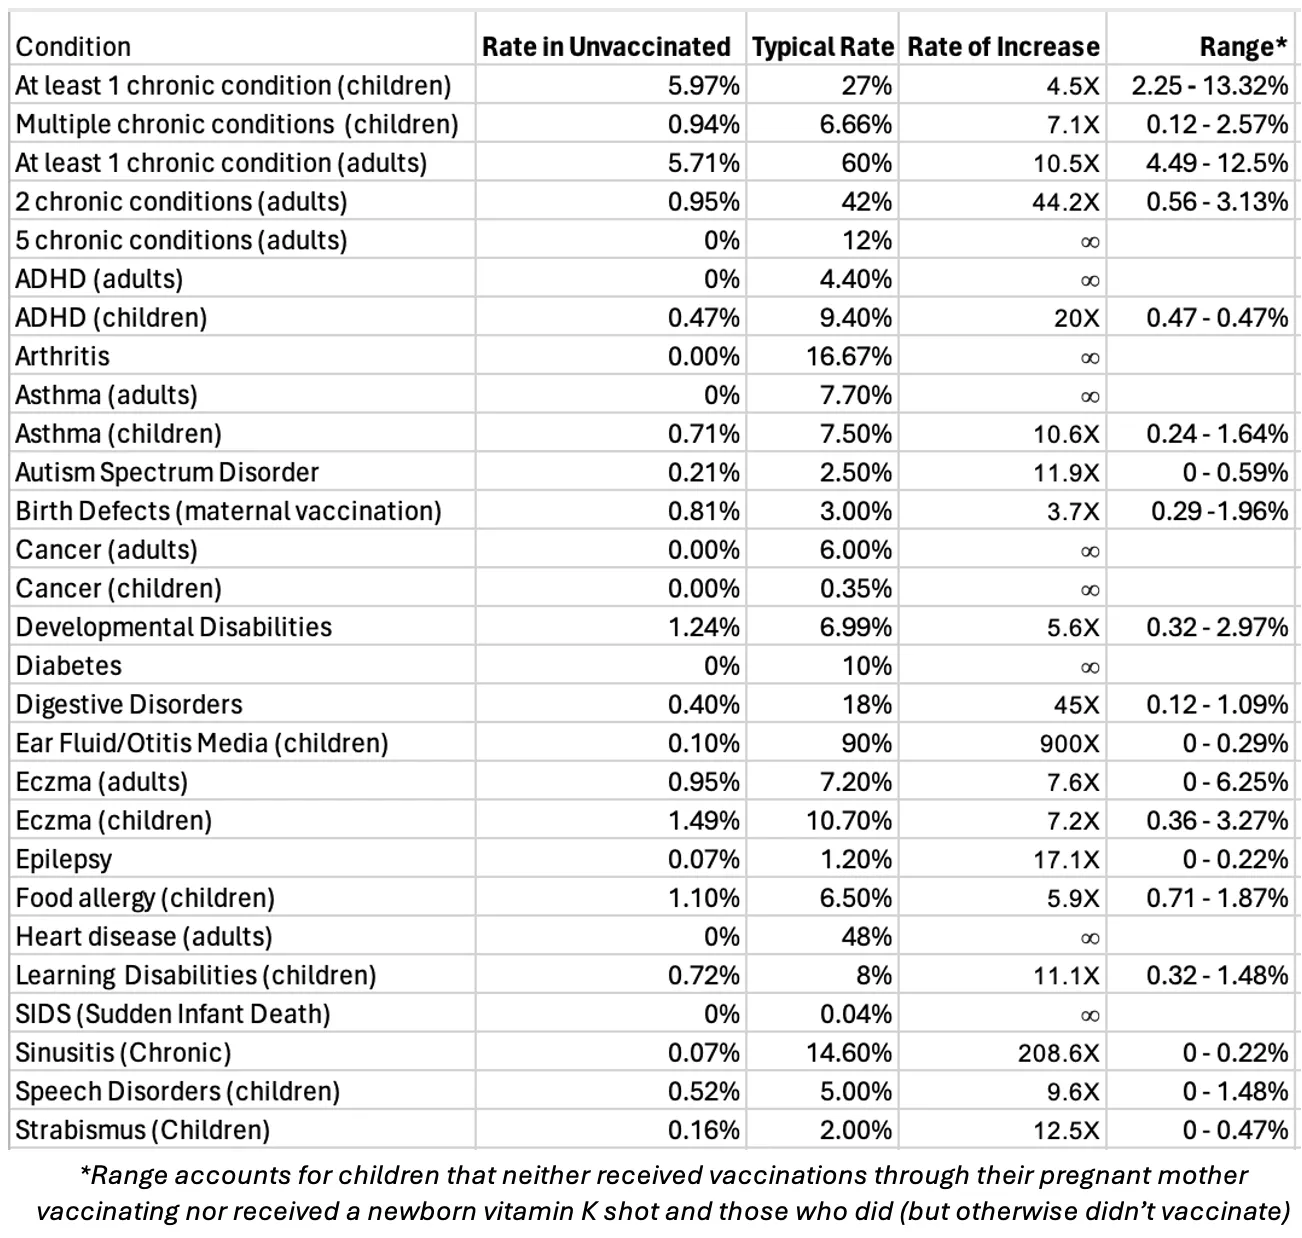
Between April 2019 to June 2020, the Control Group attempted to locate as many unvaccinated as possible to survey their health. Ultimately, they received 1544 completed surveys (1482 were from the US and represented 48 states). Once this data was obtained it was published in an easy to read 21 page set of charts that compared the rates of these events to their general occurrence in the population and a more detailed 85-page report. Like the previous groups, they found a massive increase in chronic illness following vaccination, and additionally, demonstrated that vaccinating while pregnant or a newborn receiving the vitamin K shot (about half of which contain aluminum) is not entirely safe.
Steve Kirsch
Many people in tech believe the solution to all of humanity’s problems is more data. This echoes the belief of the founder of evidence-based medicine (which has become the current dogma of modern medicine), who argued that having medical practice guided by the best available scientific evidence was essential as it would eliminate bad medical practices that had become entrenched medical dogmas and replace them with evidence-based approaches that saved lives.
While he was correct, like those in Silicon Valley, this approach was also incredibly naive as it failed to account for the obvious loophole—burying any data that provided inconvenient conclusions. As such, “the best available evidence” typically ends up being the best funded evidence, not the best evidence and at this point, trillions are spent each year to monopolize that evidence.
To illustrate: our electronic medical records which doctors are forced to spend a significant amount of each day entering data into collect an absolutely massive amount of medical data. Yet—despite countless pleas to, we almost never mine that data to determine what constitutes the best medical practice (e.g., which drug produces a better outcome for a condition or which pharmaceuticals are more likely to harm than help a patient).
This would be very easy to do, numerous people (including an acquaintance of mine) have tried to do this but got shut down (e.g., the government scrapped a system that in 2010, showed 2.6% of recipients of vaccines had an injury within 30 days of vaccination). I in turn, would argue that suggests the data in those records greatly threatens the pharmaceutical industry and hence cannot be disclosed.
Over the last few years, I’ve gotten to know Steve Kirsch and would argue the following traits hold true for him:
He has a deep desire to help people (e.g., he’s donated a lot of money to charity) and believes that better data and science are the keys to doing this.
He believes things should be fair and it really bothers him when people violate the responsibilities they are entrusted with (e.g., the CDC monitoring for vaccine safety).
When something bothers him, he often doesn’t let it go and can be relentless in trying to rectify it (which is demonstrated by how much time he has put into obtaining the minute details of the COVID-19 injury data).
He has no qualms about doing things you aren’t supposed to do or creating an uncomfortable situation to get something done he believes is important. This includes directly confronting people he thinks are being dishonest or incompetent and full of it.
Note: I am sure many of you know someone like this. Steve however is unique because I don’t know anyone else in this movement like that who has also been anywhere near as successful in the professional sphere as he has. I am hence incredibly grateful he decided to pick up the vaccine issue as we’d been waiting for decades for someone like him to do that (which is essentially why I’ve worked so hard to support him much in the same way we’ve helped Ron Johnson—the first US Senator in history to fight for vaccine safety).
Because of his personality, Steve in turn had a revelation—if no one will give us the data we need about the vaccines I should just obtain it myself. As such, beyond collecting every existing dataset demonstrating the harm of the vaccines (many of which I’ve reused here), he has also funded numerous professional surveys being conducted on the COVID vaccines (which all found between 8.6% to 16.4% of COVID vaccine recipients experienced significant harm from them, a rate similar to that of other independent surveys that were also conducted).
Additionally, he has also leveraged his large following to conduct numerous surveys on vaccine injury. While the initial ones were targeted at the COVID-19 vaccines, as he became aware of the scope of the problem we were facing, he also chose to do the same for the childhood vaccines.
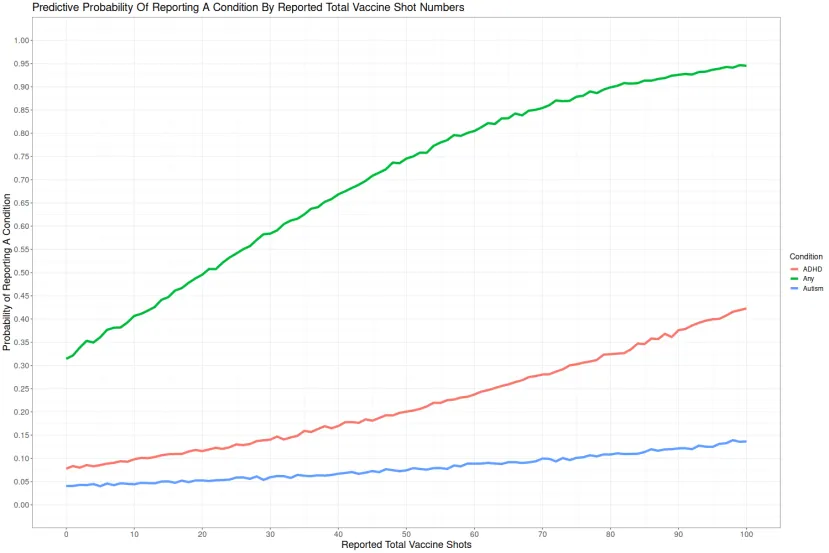
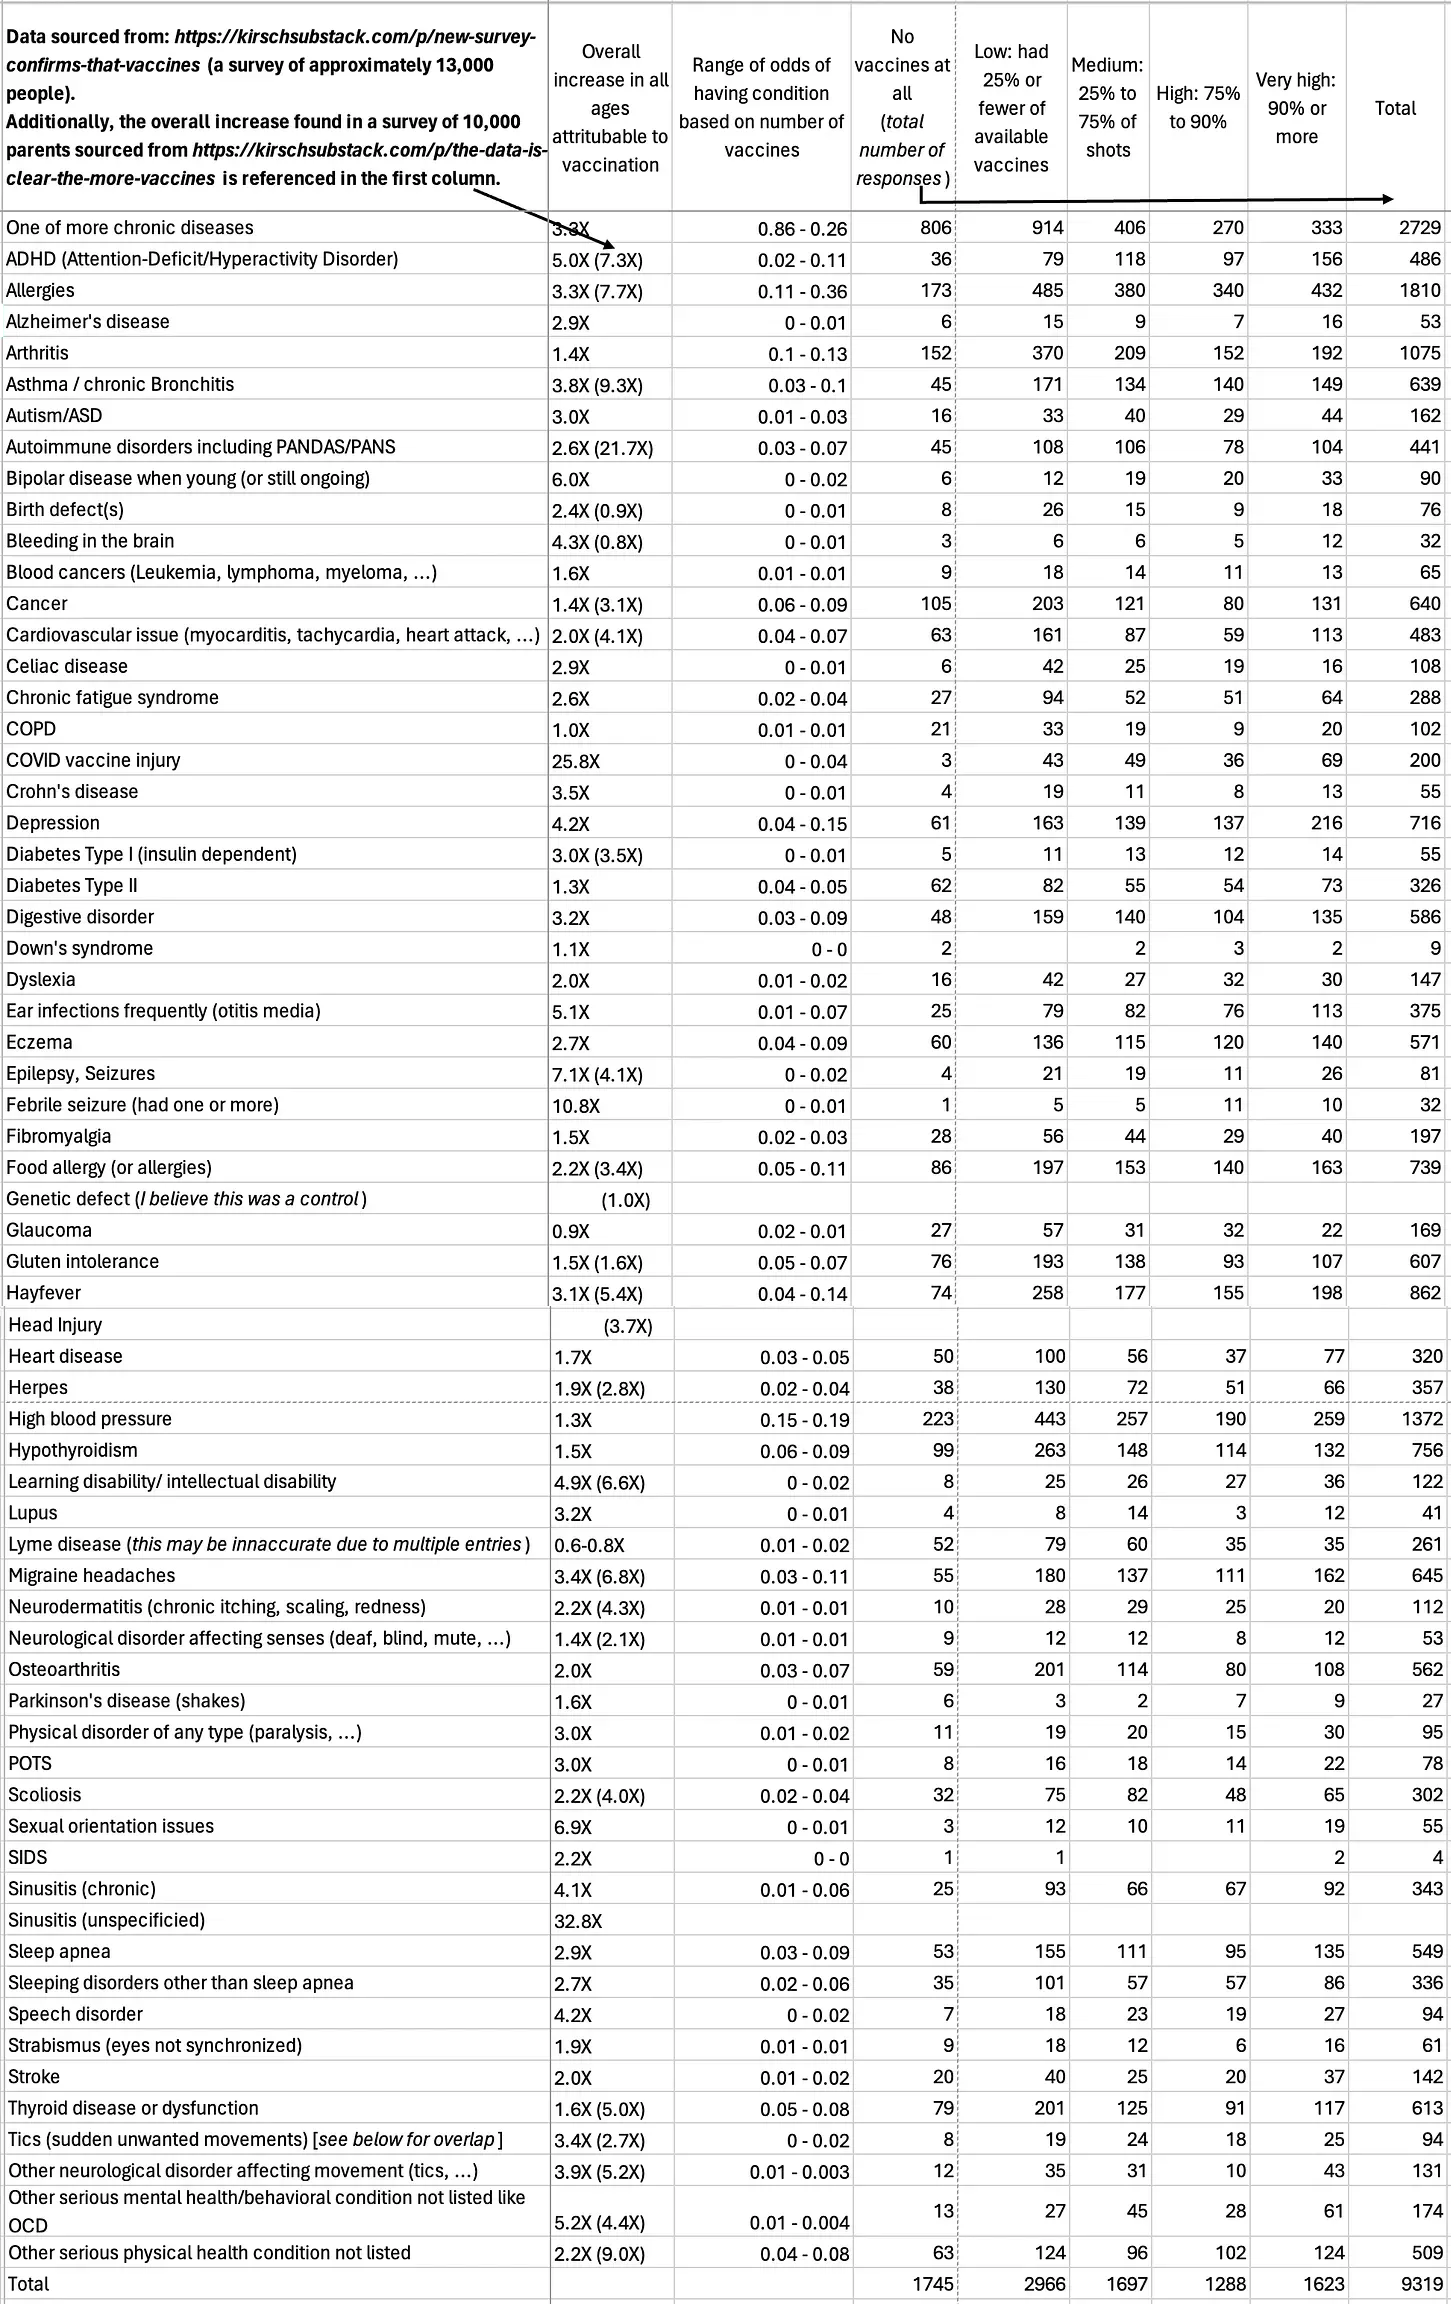
From this, he found similar results to the previously mentioned parties. For example in his first survey of ~10,000 people, he again demonstrated the dose-response relationship between vaccination and chronic illness:
Hopefully, this shocking data provides some context to why many are so ardently opposed to vaccination and why there is such a strong embargo on ever letting any of this data get out. Instead we’ve allowed an ever increasing number of vaccines to enter the market which in turn has led to us needing to spend trillions of dollars each year “treating” the complications of those vaccines.
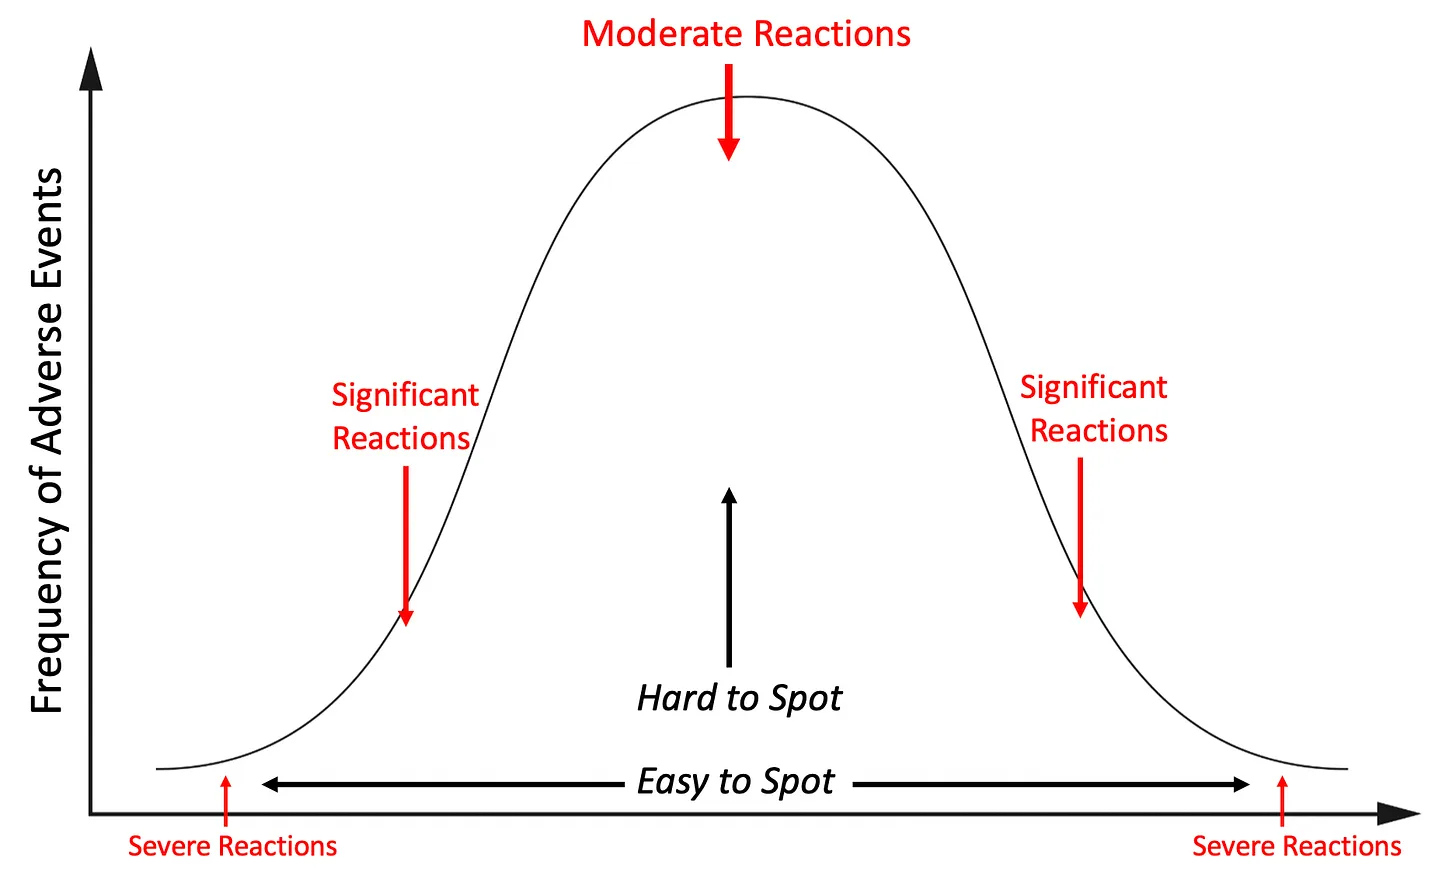
What I believe is the most important to understand about these statistics is that they only represent the tip of the iceberg, as the surveyors were only looking for the easy to observe conditions most obviously linked to vaccination (the “significant reactions”), much in the same way conventional vaccine studies only assess for a few “rare” conditions linked to vaccination. This, in turn, is reflective of a fundamental principle in toxicology—extreme reactions to a toxin (sudden death) are much rarer than minor ones.
In the next section, we will consider the middle of this bell curve—the moderate reactions that are rarely linked to vaccination.
A remarkable feature of encephalitis—whether of epidemic origin or due to an infectious disease, traumatic injury, or vaccination —is the multifarious diversity of its physical, neurologic, mental, and emotional symptom since any portion of the nervous system may be affected.
If autism is a manifestation of vaccine-induced encephalitis, the implications are very disturbing. The symptoms manifested with pathological intensity in a small group will of necessity appear in milder form in a much larger proportion of the population.
Note: in this article, I reviewed the evidence showing autism is a form of encephalitis with many accompanying neurological injuries. Remarkably, while vaccines “don’t cause autism” one of the only injuries acknowledged by the 1986 Vaccine act was MMR (the vaccine linked to autism) causing encephalitis.
Minimal Brain Damage
The 1985 Book, DPT: A Shot in the Dark is arguably the most influential book ever written for the vaccine safety movement (e.g., it was responsible for rallying Congress to do something about the epidemic of sudden deaths and brain damage being created by the original DPT vaccine). What is less known is that in 1990, one of its authors, Harris Coulter, then published a book that alleged that vaccines were responsible for the widespread increase in crime sweeping the nation.
Note: I consider this book to be one of the most eye opening and disturbing books I’ve ever read (e.g., as a child, I saw what it described happen in people I knew quite well). Since some of its content is quite graphic (and because the book is hard to find) I am including a copy of it at the end of this article for those who would like to read it (which I would strongly encourage you to do). As there are too many references to list here, to locate them, please consult the book’s bibliography.
The author (who as his obituary shows was a lovely human being and gifted researcher) in this book argued that:Many of the same complications seen after encephalitis (e.g., cranial nerve issues, seizures, paralysis, or permanent intellectual disability) also occurred after vaccination. He proved this by compiling extensive literature reports of each, which showed they overlapped and in many cases, showed the vaccine injuries were assessed to be “encephalitis” (which I likewise did so here).
This included over 400 references from the scientific literature (located prior to the internet existing), another 400-500 he reviewed but did not cite (which arrived at similar conclusions), interviews of approximately 150 families, where in many cases, he was able to show these childhood brain injuries progressed into a life of crime. Note: I believe “encephalitis” (or encephalopathy) is a combination of brain inflammation (autoimmunity is a common complication of vaccination), brain swelling, microstrokes throughout the brain (discussed further here) and an unresolved cell danger response (discussed further here). Additionally, if you read the medical literature from roughly a century ago (summarized here), its clear many doctors believed vaccines caused encephalitis based on the symptoms they observed (and in many cases the autopsies they later performed).
If the DPT vaccine can cause “acute encephalopathy” in a small number of cases (which was acknowledged by the Institute of Medicine in 1991), it must cause a milder condition in a larger number of cases as the reactions of a group of individuals to a given biological stress are never “all or nothing,” but fall along a continuum. Note: Coulter cited many different authors who observed a bell curve in post-encephalitis complications.
That it was very easy to miss that this was happening. For example, Coulter cited two different authorities on this subject who said:
Actually there is no correlation between the severity of the infectious disease and the cerebral involvement. In many cases with only a mild illness severe postencephalitic complications may arise months or even years later.
Even apparently uncomplicated attacks of infectious diseases of childhood (e.g., pertussis) may result in brain damage, which may then be the primary cause of subsequent behavior disorders.
Researchers in the epidemiology of vaccine damage invariably assume that long-term sequelae will not occur in the absence of a severe acute reaction. This assumption was accepted by us in writing DPT: A Shot in the Dark. Thus it was puzzling to find that about half of the new families interviewed for the present investigation could not remember any marked vaccine reaction, even though the child began to develop symptoms of autism or other severe neurology shortly after one of the shots.
Many of complications of encephalitis (e.g., a myriad of learning disabilities or psychiatric and neurologic illnesses such as autism) became dramatically more common in our society starting in the 1940s and 1950s, a rise which paralleled increased vaccinations and increased vaccine injuries (predominantly as a result of DPT—the vaccine most associated with brain injury) and could be directly observed rippling through society as these children grew up. For example:
Rimland and Larson have called attention to “the striking, almost mirror-image correlation, starting about 1963, between the curves showing the decline in SAT scores and the upsurge in violent crime [which was often psychotic in nature],” suggesting “the existence of one or more common causal factors.”
The contrast between then and now was emphasized in a 1987 report on school discipline by the New Jersey Human Rights Commissioner. In the 1940s the most frequent school problems were: talking, chewing gum, making noise, running in the halls, getting out of turn in line, wearing improper clothing, and not putting paper in wastebaskets. In the 1980s they were: drug and alcohol abuse, rape, robbery, assault, burglary, arson, bombings, murder, absenteeism, vandalism, extortion, gang warfare, abortion, and venereal disease.
The murder rate doubled between 1960 and 1980, from four to eight per 100,000 inhabitants, for a total of more than 20,000 in 1987, giving the United States the highest incidence of homicide of any industrialized country. The largest increase occurred between 1960 and 1970.
A 1987 Washington Post-ABC News poll made a curious discovery—that sixteen percent of Americans under thirty are left- handed or ambidextrous [this is a common consequence of encephalitis], as against only twelve percent of those over sixty. Another recent survey found an even greater disparity: thirteen percent of twenty-year olds were lefties, compared to five percent of persons in their fifties.
Autism (a condition which follows vaccination and first emerged after DPT entered the market), has a strong association with many of the consequences of encephalitis (e.g., cognitive disability and cranial nerve paralysis).
That sociopathic behavior being observed to cluster in families mirrors the observation sensitivity to vaccine injuries also clusters in families. Likewise, Coulter suggested the increased sensitivity African Americans have to vaccine injuries (best shown through the CDC’s infamous decision to bury data that showed vaccines caused black boys to develop autism) might explain the social patterns seen in those demographics. Note: in a recent article, I discussed how some patients (e.g., those with hypermobility) are also much more sensitive to vaccine injuries.
That a variety of conditions had been created by the American Psychiatric Association which spanned the range from how minor to severe brain damage manifested itself in behavioral disorders (e.g., minimal brain damage, oppositional defiance disorder, conduct disorder, sociopathy). Coulter emphasized that as the DPT encephalitis condition exploded across America, the psychiatric profession tried again and again to gaslight the population by blaming it on unresolved psychological conflicts or poor upbringings rather than providing treatments holistic doctors had consistently found could help these conditions. As far as I can tell, this psychological gaslighting continued until the newer psychiatric medications (e.g., the disastrous antidepressants) entered the market, at which point psychiatric pivoted to mass-prescribing these lucrative products to the post-encephalitic patients. Note: this is a pattern that has persisted ever since Freud’s original cases over a century ago which falsely attributed symptoms of mercury poisoning to unresolved sexual issues.
In the 1950s, a condition termed “minimal brain damage” [MBD] was coined (with the defining characteristic of it being hyperactivity), which before long became “perhaps the most common, and certainly one of the most time-consuming problems in current pediatric practice”. The symptoms of MBD (as defined by America’s Public Health Service and the American Psychiatric Association) have a significant overlap with what was seen after encephalitis, DPT injuries, and what was associated with autism.
A British physician in 1928 noted that “changes in morals and character” in patients who have had encephalitis reveal a “curious uniformity.”‘ This same “curious uniformity” stamps the autistic, the minimally brain damaged, and the sociopath.
This encephalitis may produce an intellectual, tormented, and cruel monster out of a gentle girl or boy.” “A child of previously responsible character may be so transformed as to seem a different person…cruel, destructive, abusive, indecent.
Note: as a point of clarification, autistic children typically do not demonstrate cruel or sadistic behaviors (as that is only one possible outcome of brain damage). However, they do share many of the other traits found in post-encephalitic individuals.
There was a wide range of consequences of encephalitis. Many of these were subtle and insidiously altered the child’s personality, commonly making them hyperactive, hypersexual less empathetic, and generally uncomfortable with their environment. Many of these traits in turn were also seen in violent criminals and disruptive children (who frequently then went on to become violent criminals).
Coulter then collected numerous case histories of violent and sociopathic criminals demonstrating that they displayed many of the exact same signs (e.g., cranial nerve issues) seen in victims of encephalitis (be it from vaccination or a natural infection). This included detailed reviews of infamous criminals who precisely fit the post-encephalitic pattern such as Ted Bundy.
Coulter also provided numerous statistics and studies which showed violent criminals had dramatically higher rates of brain damage and neurologic dysfunction. Many of the studies he cited (e.g., one of 321 excessively violent individuals showed 90-100% had demonstrable brain dysfunction) found these defects occurred at 5-10 times the rates seen in the general population).Note: the associations shown in the papers Coulter compiled are also supported by modern research and hence are generally accepted. Additionally, newer research made possible by functional MRIs also show that violent or sociopathic criminals often have significant brain damage and lack the normal functions (e.g., empathy) other humans have. Much of this is shown in this audiobook and the research papers its author published.
Coulter cited numerous statistics showing a small minority of the population committed a majority of the violent crimes that occurred and evidence showing the crimes in the post DPT era were often much more brutal and sociopathic.
The traits commonly associated with MBD in turn were as follows: Note: these were also frequently observed to be consequences of encephalitis and often clustered together. Additionally, quite a few of these are now known to occur more frequently in violent criminals.
Hyperactivity (this was by far the most commonly associated trait with MBD). Note: there is a well-known association between hyperactivity and stimulant drug use or violent crime. Many authors (e.g., psychiatrist Gabor Maté) in turn have argued many people become drug addicts because they have untreated ADD (which we typically treat with pharmaceutical amphetamines—which unfortunately, like the SSRI antidepressants, can cause violent psychosis).
Frequent drug and alcohol use.
Hypersexuality. Often this sexuality was detached from having any type of connection to the other person and sometimes gave rise to a variety of unusual sexual fetishes or preferences. Note: this goes hand in hand with the emotional blunting frequently observed after encephalitis. Additionally, one of the most common types of dementia (which results from poor blood flow to the brain) is characterized by hypersexual behavior.
Feeling overwhelmed by and not in control of their environment.
Having difficulty organizing their thoughts or remembering their past experience. Note: this includes a flattening of one’s affect when remembering their questionable conduct from the past, an inability to empathize with those who were affected by it and in many of the case histories Coulter compiled, a complete amnesia of it.
A very short attention span (and paradoxically in a few cases, instead an obsessive and greatly excessive attention span).
Being impulsive and easily triggered into having violent outbursts (from both external stressors and internal ones such as a severe headache).
Headaches (which sometimes necessitated banging their head against a wall).
A high incidence of seizure disorders: epilepsy, tics, tremors, choreiform (twisting) movements, facial grimaces, infantile spasms, and others. There were also frequently overt signs (e.g., EEG abnormalities) and subtle signs (e.g., poor coordination) of these disorders.
While some children with MBD had above average intelligence, on average their IQ was below average.
Bed-wetting in childhood, typically occurring in conjunction with a sleep disorder (that often had features such as teeth-grinding, night sweats, nightmares, and night terrors). Sometimes this is also accompanied by loss of bowel control (e.g., ectopresis).
Poor visual-motor coordination, clumsiness and a lack of grace to their movement (e.g., “impaired hopping ability, and a tendency to walk on the toes”).
Decreased sensation to external painful stimuli.
Left-handedness or ambidexterity. Note: I know numerous people with DPT injuries this happened to.
Various processing disorders. These include dyslexia (difficulty reading), dysgraphia (difficulty writing), dyscalcula (difficulty with numbers), impaired speech (e.g., stuttering or stammering), paucity of speech or mutism, hearing disorders (e.g., audiomotor incoordination, auditory imperceptions or deficits, developmental receptive language disorder, high-frequency hearing loss, or hypersensitivity to sound). Note: the perceptual disturbances often were accompanied with a difficulty telling left from right or up from down.
Excessive sleepiness and a wide range of sleep disturbances (including new sleep disorders the medical community had not previously witnessed such as “delayed sleep phase syndrome,” a condition where one cannot fall asleep until 3 or 4 in the morning).
Frequent food allergies (along with conduct worsening when those foods were consumed). Note: other neurological diseases (e.g., schizophrenia and autism) have also been observed to improve after allergens such as gluten are completely eliminated from the diet.
Appetitive disturbances (e.g., anorexia or bulimia). It was noted that this complication of encephalitis far more frequently affected females, whereas hyperactivity more frequently affected males.
A strong desire to seek out music due to the rhythmicity and stability it provides.
Being highly disruptive and violent from a very young age.
Note: in the second half of this series (which can be read here), I discuss the changes in personality which specifically affect human relationships (e.g., the ability to emotionally connect with one’s partner or one’s gender identity) as there seems to be a fairly profound effect here that has real life data to substantiate it.
A Vaccinated Society
Assuming Coulter’s thesis is correct, the implications are sobering, and in turn, many readers here (who recognized witnessing what I described unfold in their own lives) felt the same way.
As so much could be said about this subject, I will only share a few of my most pertinent thoughts.
Like many of you, I often encounter people who me think “Why do you have to be so difficult?” Becoming able to recognize how vaccine encephalitis manifests has allowed me to switch from being frustrated by their behavior to developing a great deal of compassion for them. Likewise, it’s also made it much easier for me to understand how to effectively interact with them because I can recognize how their brains are misfiring and bypass those issues.
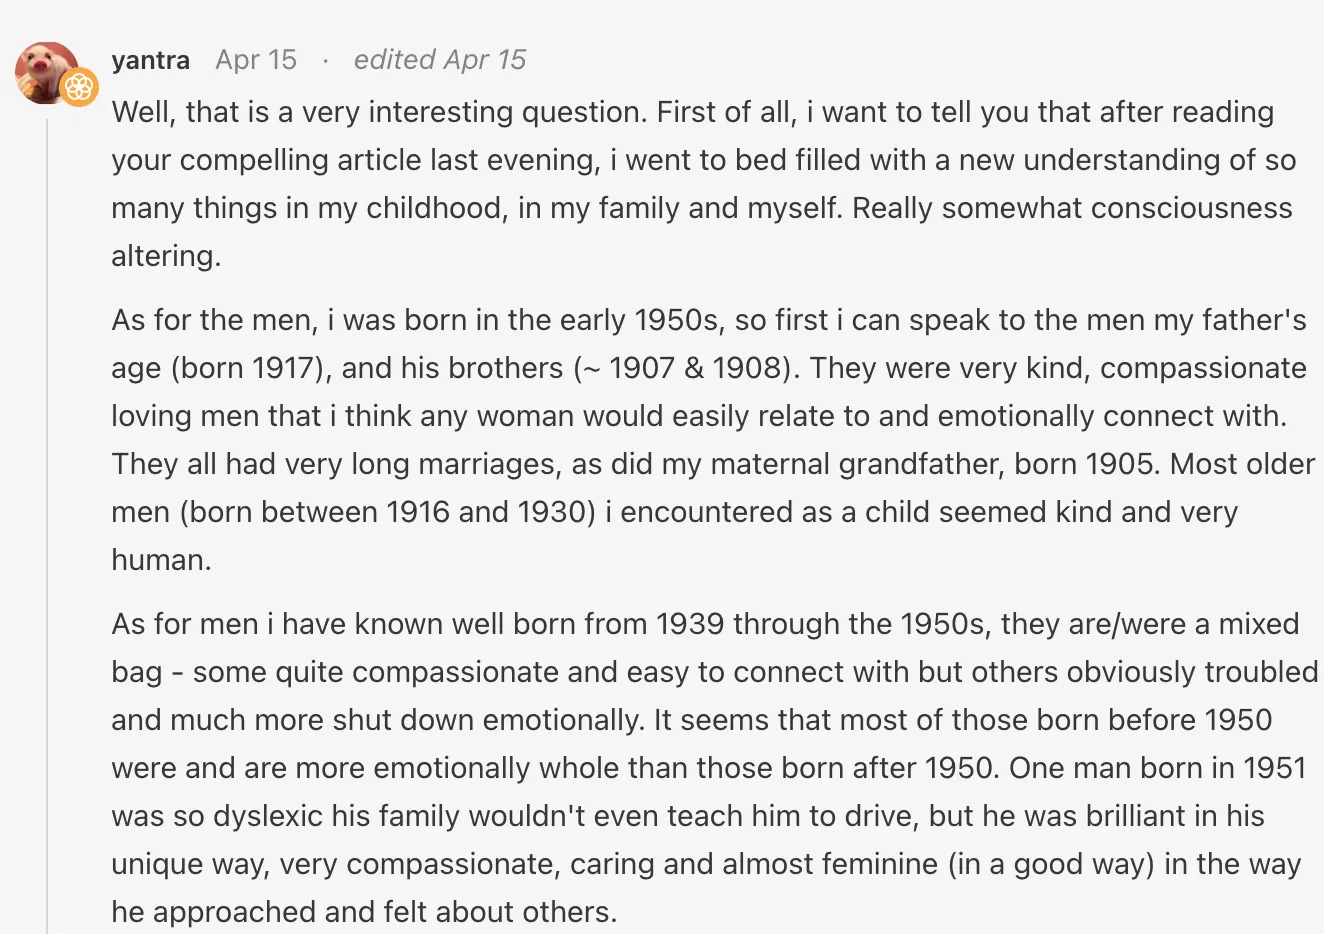
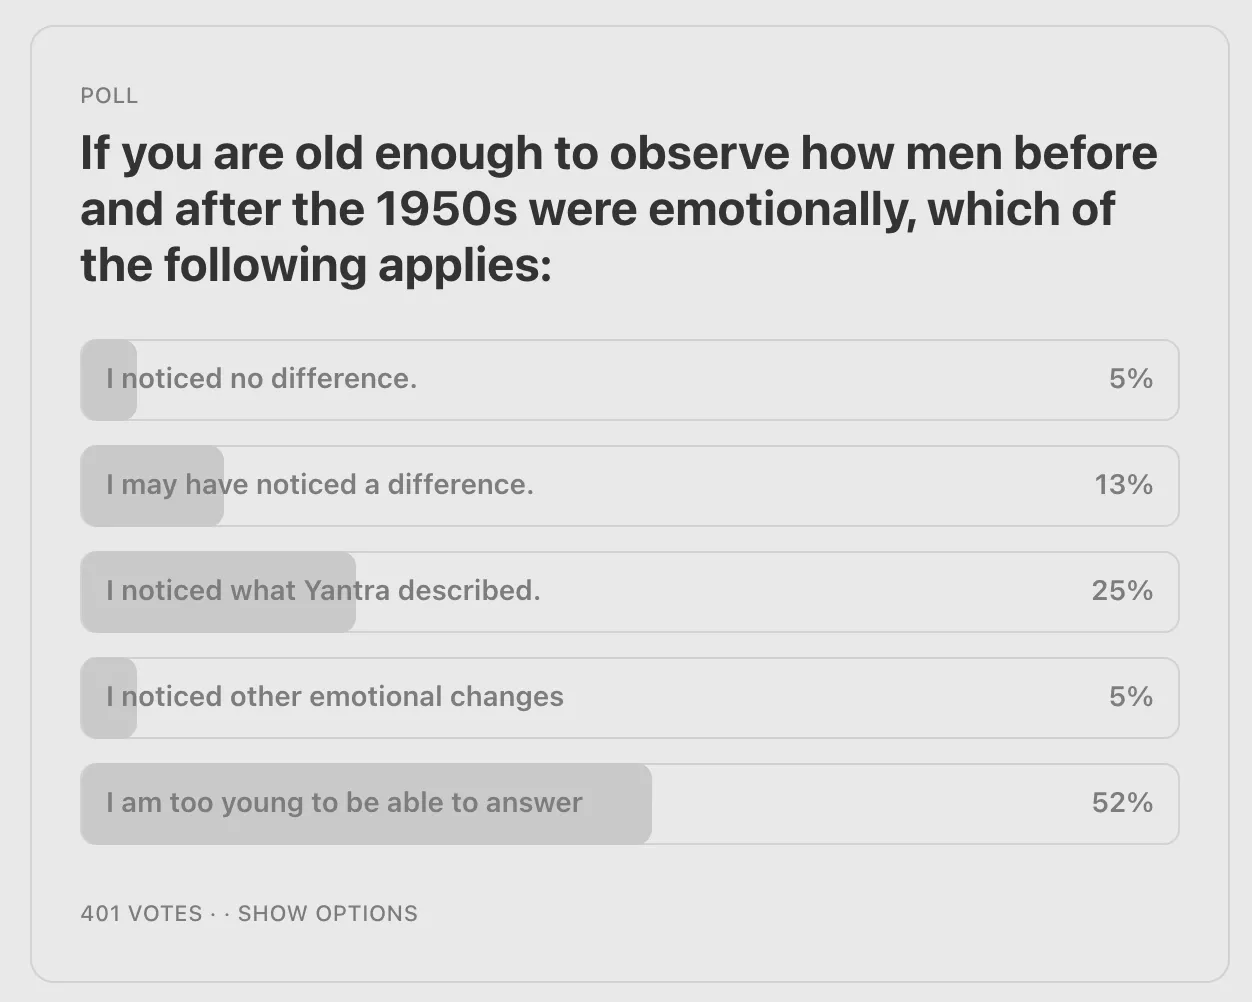
Many of the cognitive changes described in post-encephalitic patients perfectly mirror the common frustrations women have with men who cannot emotionally connect to them. This in turn has made me realize the vaccine program has likely profoundly altered the dating dynamics of the country, and from the queries I’ve made so far, my older readers who witnessed this shift occur agree it is likely an issue. For example:
I then conducted a poll (to a readership which was much smaller at the time) that found:
I believe the gravest violation of medical ethics is if the pharmaceutical harms those who never consented to taking it. This is why I have put such a heavy focus on both the COVID-19 vaccine shedding and the frequent tendency of SSRI antidepressants to cause episodes of mass violence (e.g., school shootings).
This whole concept really turns both the liberal and conservative notions of what should happen with criminal justice upside down.
There has been a longstanding observation that the quality of American education has greatly declined (e.g., that what used to be taught in 8th grade was more difficult than what is now taught in college). I long thought this was due to education being massively mismanaged as it shifted to a profit focused (student retention) based model, but after I learned of Coulter’s hypothesis, I realized that it could also instead be a symptom of the societal wide decline in cognitive function being created by mass vaccination and schools having to accommodate it. This may also be intentional, as too many intelligent and mentally healthy people would threaten any oppressive power structure, and in turn mirrors what a doctor who was mentored by Robert S. Mendelsohn M.D. (a renowned pediatrician and one of the most impactful dissidents against the medical cartel) shared with me:
Mendelsohn told me that during his appointment as Medical Director of Project Head Start’s Medical Consultation Service in 1968, he was horrified by the discussions held privately in the White House with his medical colleagues. They were openly discussing how they could control the population of the poor by promoting infant formula, vaccinations, sadistic hospital birthing practices, deficient government schools, and neighborhood abortion clinics. This was just too much of an assault on his strong Jewish faith and his Hippocratic oath.
There is presently no incentive to stop this as so much money can be made selling treatments for these diseases (which are often very harmful), while if the mistake is ever admitted, far too many people have too much to lose. This in turn is why we keep on having worse and worse vaccine tragedies inflicted upon the world.
All of the data here shows why ACIP has not only a moral obligation but also a societal obligation to consider if the vaccines they approve are beneficial and necessary enough to outweigh the real harm each one can cause, particularly as more and more of them are given in succession. Put differently, I have full confidence that if all vaccines were banned, while some vaccine preventable illnesses would increase, the overall health and rate of illness in the country would dramatically decrease. For this reason, if mass vaccination continues it must be shifted only to the illnesses where the best argument exists for it (which I reviewed here) rather than ones where the harms of a (lucrative) vaccine greatly outweigh any possible benefits it can offer.
Note: while this position is controversial, I support providing some type of amnesty for the vaccine cartel, as I believe that is the only thing short of a revolution which would make them be willing to stop protecting the vaccine racket, since without it, it is quite literally a life or death battle for them to prove vaccines are “safe and effective.”
Subtle Signs of Vaccine Injury
When I first entered the medical field, a variety of holistic doctors (and other healers) told me they could typically tell if a child had been vaccinated. While I believe this is often possible to do, it requires utilizing a variety of more subtle signs most people would not agree with (excluding say the parents who noticed “something” changed in their child after vaccination).
Note: once you start becoming able to see how vaccine injuries are and how shocked or traumatized many infants look, it gets really depressing (whereas in contrast people are often drawn to unvaccinated babies and comment on how vibrant they are).
In turn, many have asked me what the signs of vaccine injury are. The challenge with this topic is that subtle injuries are dramatically more common than severe injuries (as reactions to toxins tend to follow a bell curve, with the most severe reactions being the rarest). Thus, the more subtle signs are harder to recognize (or prove resulted from vaccination) but simultaneously are by far the most common.
Some of the most common signs we use are:
A new condition developing shortly after vaccination that is known to be linked to vaccination (e.g., those listed in the above surveys such as seizures or autism). Often, there is a fairly consistent pattern in how these injuries form (e.g., they are preceded by severe fevers and crying that immediately follow the vaccination).
Overt changes in the cranial nerves (e.g., the eyes no longer track smoothly, or the facial muscles become asymmetrical). Note: here I explain how vaccine induced microstrokes can commonly cause this to happen.
A subtle change in function to any of the cranial nerves (many of which are detailed in the copy of Coulter’s book included below and in Wilson’s earlier compilation of our first century of forgotten vaccine disasters). Note: if you train yourself to spot these, they become more and more obvious as you become able to notice when something facilitated by a neurological process seems to glitch or misfire (e.g., the eyes lose their smoothness and jump as they move to either side).
Overt (rarer) or subtle (more common) cognitive and neurological changes which can be indicative of brain inflammation or brain damage. Like the cranial nerve changes, they are also discussed in Wilson and Coulter’s book (included below).
In addition to these changes, they are some more subtle “spiritual” changes, which are amongst the most frequent changes observed (and what many of my colleagues eventually default to using to identify vaccine injuries). Given that these signs, while very apparent, are “spiritual” in nature, I went back and forth on if I wanted to discuss them, and eventually felt it needed to be to a limited audience.
For best viewing, click here or click Toggle fullscreen on the PDF tool bar to make the PDF larger. On a mobile device, you should also rotate to landscape mode.
Five clear, replicable, and related discoveries explaining how autism is triggered have formed an undeniably clear picture of autism’s causation.
STAFFORDSHIRE, England —Dr. Chris Exley of Keele University in England and his colleagues published a paper that for the first time ever looked at the brain tissue of subjects with autism to determine the level of aluminum (note: they spell “aluminum” as “aluminium” in the United Kingdom) found within their brain tissue. For anyone trying to convince the world that “the science is settled and vaccines don’t cause autism,” the study’s findings are deeply contradictory to that statement. In a blog post written by Professor Exley on the day his study was published, he explained the groundbreaking results:
Dr. Chris Exley
“…while the aluminium content of each of the 5 brains [of people with autism] was shockingly high it was the location of the aluminium in the brain tissue which served as the standout observation…The new evidence strongly suggests that aluminium is entering the brain in ASD [autism spectrum disorders] via pro-inflammatory cells which have become loaded up with aluminium in the blood and/or lymph, much as has been demonstrated for monocytes at injection sites for vaccines including aluminium adjuvants.”
Dr. Exley’s quote includes a reference to “monocytes at injection sites” and the fact that the interaction between these monocytes and aluminum has been demonstrated in previous published science. I know, that sounds pretty technical, but bear with me. A “monocyte” is a type of white blood cell, of which one form of monocyte is a “macrophage.” A macrophage can be thought of as the garbage man of the immune system, eating up foreign substances, cell debris, etc. As you will see in a moment, macrophages appear to be playing a critical and devastating role in triggering autism, serving to escort man-made aluminum injected from a vaccine directly into the brain, where it can disrupt brain development and trigger autism.
Dr. Exley’s study — “Aluminium in brain tissue and autism” — is arguably the final piece of a puzzle that first started to come together in 2004, and picked up steam after 2010, that has dramatically furthered the scientific understanding of exactly how a vaccine can trigger autism. This timeline is critical to recognize, because the Vaccine Court in the United States dismissed the vaccine-autism hypothesis in 2009, long before most of what I’m about to explain even existed. Science is a continuum, an emergence of truth through many different studies that often have to be pieced together before the picture becomes clear. And, scientific progress can sometimes move slowly until that moment when an emerging truth presents itself in such a way that it can no longer be denied. In my opinion, Dr. Exley’s study provided the only data missing from an airtight explanation of what happened to my son and so many other children, and provided all the doubters with the “biological plausibility” of how, exactly, a vaccine injected into a baby’s shoulder can trigger autism.
For Americans, the race to discover what’s causing all this autism will likely be won on foreign shores. As you’ll soon see, ALL of the science explaining how autism can be caused has come from other countries, even though a Caltech scientist pushed the first domino way back in 2006.
Why is aluminum in vaccines at all?
Aluminum is a critical component of most vaccines given to children. It serves as an “adjuvant” meaning the aluminum serves to “wake up” the immune system, provoking the immune system to recognize the “antigen” within the vaccine for whatever disease the vaccine serves to protect against. The amount of aluminum in vaccines given to children skyrocketed beginning in the early 1990s for two reasons: 1), more vaccines were added to the children’s vaccine schedule and, 2), the vaccination rate for all vaccines given to children rose (from 50–60% of children vaccinated in the mid-1980s to over 90% today). A child in the mid-1980s would have received 1,250 micrograms of aluminum from their vaccines by their 18-month birthday if they were fully vaccinated. Today, that number is 4,925 micrograms, a near-quadrupling of total aluminum. You can read more about this in an excellent study published by Neil Miller, here’s an image from the study:
Mystifyingly, aluminum has never experienced biological testing to consider its safety for being injected into babies, having been “grandfathered” into our modern safety standards. Canadian scientists Dr. Chris Shaw and Dr. Lucija Tomljenovic addressed this omission in a critical study they published in 2011 in Current Medicinal Chemistry titled, “Aluminum Vaccine Adjuvants: Are they Safe?” They wrote:
“Aluminum is an experimentally demonstrated neurotoxin and the most commonly used vaccine adjuvant. Despite almost 90 years of widespread use of aluminum adjuvants, medical science’s understanding about their mechanisms of action is still remarkably poor. There is also a concerning scarcity of data on toxicology and pharmacokinetics of these compounds. In spite of this, the notion that aluminum in vaccines is safe appears to be widely accepted. Experimental research, however, clearly shows that aluminum adjuvants have a potential to induce serious immunological disorders in humans. In particular, aluminum in adjuvant form carries a risk for autoimmunity, long-term brain inflammation and associated neurological complications and may thus have profound and widespread adverse health consequences.”
ICAN decided to test the CDC and NIH’s ability to produce any studies to show the safety of vaccine adjuvant through a FOIA lawsuit, by now I’m guessing you know how that ended…read the whole article.
“CDC and NIH’s responses to ICAN’s Freedom of Information Act (FOIA) requests regarding aluminum adjuvant reveal a stunning admission: they do not have a single study to support the safety of recommending repeated injection of this cyto- and-neuro toxic substance as part of the CDC’s childhood vaccine schedule.”
Ground zero at Caltech
When Caltech scientist Dr. Paul Patterson passed away in 2014, I had little appreciation that he had triggered a chain of events over the course of his career that may now provide a clear and unambiguous explanation of how and why my son developed autism back in 2004. Knowing exactly how my son’s autism was caused is incredibly important to my wife and I, because the more information we have about causation, the more chance we have to do something about it, and perhaps recover my son from an affliction now impacting 1 in 32 American kids.
What you’re about to read is the product of more than two dozen very recent peer-reviewed published scientific studies, with really no original thought by me. I’m a businessman and a father, but what follows is a “grand theory of autism” so complete and well-supported that I think it deserves the attention of every member of the autism community. When the totality of this explanation became clear to me, not only did my jaw hit the floor, but I was immediately consumed with thoughts about how this clear explanation might impact the way we treat our son’s autism, and I hope it does the same for you and perhaps your doctor as well. What I’m certain of is that this “grand theory” needs to be heavily debated, and I hope by putting it in the public realm I help move it along that path.
(I’m indebted to an anonymous scientist who runs a website called Vaccine Papers, where many of these insights came from. I will quote VP throughout this piece, referring to VP as “VP.” I highly recommend you read the totality of his website, where the explanations are far more scientific than what you will read here.)
It shouldn’t be a surprise that all of this science has been published outside the United States. I’ve listened closely to the stories of American scientists wanting to study autism and complaining that any studies that are even remotely controversial are nearly impossible to fund or get approved.
Discovery #1: “Maternal Immune Activation” can cause autism
While Dr. Patterson’s passing wasn’t something I was aware of at the time, it was certainly recognized by the scientific community, of which his obituary from Caltech explains in great detail.
Dr. Paul Patterson
Dr. Patterson’s “research focused on interactions between the nervous and immune systems — a connection that was not universally acknowledged in the early days of neuroscience”explains his obituary, “he became intrigued by epidemiological studies that had linked a severe viral or bacterial infection during pregnancy with the increased risk of a woman giving birth to a child with a neurodevelopmental disorder such as schizophrenia or autism. Patterson and his coworkers reproduced this human effect in mice using a viral mimic that triggers an infection-like immune response in the mother, producing in the offspring the core behavioral symptoms associated with autism and schizophrenia.”
In 2006, Dr. Patterson introduced his complex understanding of the interaction between the immune system and neurodevelopment through an excellent article in the Engineering & Science journal, titled Pregnancy, Immunity, Schizophrenia, and Autism. I hope you’ll take the time to read this for yourself, Dr. Patterson does a great job of explaining his discovery to the uninitiated, it’s really a seminal work. Here’s a quote”:
“As we learn more about the connections between the brain and the immune system, we find that these seemingly independent networks of cells are, in fact, continually talking to each other. As an adult, the activation of your immune system causes many striking changes in your behavior — increased sleep, loss of appetite, less social interaction — and, of course, headaches. Conversely, stress in your life (as perceived by your brain) can influence immune function — the brain regulates immune organs, such as the spleen, via the autonomic nervous system. Recent evidence shows that this brain-immune conversation actually starts during the development of the embryo, where the state of the mother’s immune system can alter the growth of cells in the fetal brain. As we shall see, such alterations can lead to an increased risk of schizophrenia or autism in the offspring.”
Are you with me so far? Basically, what Dr. Patterson is saying is that if a pregnant mother gets sick (virus, bacteria) while pregnant — an event that “activates” her immune system — that activation can impact the neurodevelopment (how exactly the brain is constructed) of her fetus, potentially leading to neurological problems after birth. Dr. Patterson took this explanation a step further, explaining that the brains of people with autism reflect the immune system activation that took place, even decades later, as he cites valuable work being done at Johns Hopkins:
“There is also very striking evidence of immune dysregulation in the brain itself. Just last year, a group led by Carlos Pardo at Johns Hopkins found what they’re calling a “neural inflammation” in postmortem examination of brains of patients with autism who died between the ages of eight and 44 years. But these people weren’t infected — they died of such things as drowning or heart attacks. The study found that the microglial cells, which act as the brain’s own immune system, were activated. The study also found amazing increases of certain cytokines in the brain, and of others in the cerebro- spinal fluid. This is is a landmark paper, in my opinion. It presents the first evidence that there’s an ongoing, permanent immune-system activation in the brains of autistic people. It’s a subclinical state, because there’s no overt infection. But it’s there.”
While Dr. Pardo and colleagues were the first to find this “microglial activation” in the brain of children with autism, this finding has now been replicated many times, here’s a study from Japan in 2013 finding the same thing:
“In conclusion, the present PET measurements revealed marked activation of microglia in multiple brain regions of young adults with ASD. The results strongly support the contention that immune abnormalities contribute to the etiology of ASD.”
If you’re going to take one thing away from this section, I’d recommend an excerpt from Dr. Patterson’s quote worth memorizing:
“there’s an ongoing, permanent immune-system activation in the brains of autistic people.”
Is that what happened (and still is happening) to my son?
Further Refinement of Discovery #1: Immune Activation from the Cytokine Interleukin-6
If you’re an autism parent, you’ve probably heard the expression “cytokine storm” and half-understood what that might mean (anything with “storm” at the end of it can’t be good — what this really means is a chronic, slow burn inflammation in the brain). In 2006, Dr. Patterson and his colleagues were speculating that the immune system’s cytokines might be responsible for altering the brain development of the fetus during gestation:
“Cytokines are produced by the white blood cells, and their levels in the blood increase when we get an infection…We think that maternal immune activation alters brain circuits…there’s that permanent, subclinical, altered immune state in the autistic brain — those increased cytokine levels…are they [cytokines] actually interacting with the brain in an ongoing fashion, with consequences visible in the patients’ behavior? I favor [the cytokine] hypothesis.”
Just a year after Dr. Patterson’s excellent article about Maternal Immune Activation (“MIA”), he and his colleagues produced the first study that took their understanding of cytokines to a more detailed level. Knowing that MIA was producing offspring with neurological disorders (in their mouse model), they wanted to find out what — exactly WHAT — was causing the altered brain development. They figured it was a cytokine (of which there are many), but which one? As the Patterson and his colleagues noted, “however, the mechanism by which MIA causes long-term behavioral deficits in the offspring is unknown.” That is until they discovered it:
“Here we show that the cytokine interleukin-6 (IL-6) is critical for mediating the behavioral and transcriptional changes in the offspring. A single maternal injection of IL-6 on day 12.5 of mouse pregnancy causes prepulse inhibition (PPI) and latent inhibition (LI) deficits in the adult offspring.”
In the case of the 2007 experiment, Patterson and his colleagues injected pregnant mice with a specific cytokine — interleukin-6 (“IL-6”) — and saw changes in the neurology of their offspring.
Replication of Dr. Patterson’s discovery about MIA and IL-6
Dr. Patterson’s work was groundbreaking. He tied the immune system and brain together in ways previously not recognized. Like all great new discoveries in science, Dr. Patterson’s theories have since been replicated many times. In 2012, Dr. Patterson and his colleagues produced this paper,which was more autism-specific and reached a similar conclusion:
“These results indicate that MIA yields male offspring with deficient social and communicative behavior, as well as high levels of repetitive behaviors, all of which are hallmarks of autism.”
In 2014, the M.I.N.D. Institute at UC-Davis published an important study that took Dr. Patterson’s work in mice and replicated it in monkeys. Why do monkeys matter? The study authors explained:
“Maternal infection during pregnancy is associated with an increased risk of schizophrenia and autism in the offspring. Supporting this correlation, experimentally activating the maternal immune system during pregnancy in rodents produces offspring with abnormal brain and behavioral development. We have developed a nonhuman primate model to bridge the gap between clinical populations and rodent models of maternal immune activation (MIA).”
And, the M.I.N.D. Institute scientists saw similar results to what had been found in mice:
“In this rhesus monkey model, MIA yields offspring with abnormal repetitive behaviors, communication, and social interactions. These results extended the findings in rodent MIA models to more human-like behaviors resembling those in both autism and schizophrenia.”
“In summary, our study supports a critical role of IL-6 elevation in modulating autism-like behaviors through impairments on synapse formation, dendritic spine development, as well as on neuronal circuit balance. These findings suggest that manipulation of IL-6 may be a promising avenue for therapeutic interventions.”
Dr. Patterson helped establish as scientific fact that an MIA during pregnancy can cause autism. As a parent, I’m haunted by Dr. Patterson’s words that “there’s an ongoing, permanent immune-system activation in the brains of autistic people.” If that’s really what’s happening to my son, it creates an obvious question: What can we do about it? It’s why understanding exactly what happened to my son is so important…
…And why there’s something else Dr. Patterson mentioned in his 2006 magazine article, something that today might get him run out of Caltech but was still allowed in the scientific discourse back then, he said this:
Finally, I want to ask a question that’s come up in the literature in the last few years — should we really be promoting universal maternal vaccination? The flu vaccine has been recommended routinely to pregnant women in the United States since 1957. The official policy of the Centers for Disease Control states that “administration of vaccines to women seeking prenatal care is an opportunity for preventative intervention that should not be wasted.” Now you might say, “Well, of course, you don’t want to get the flu if you’re pregnant!” But remember that double-stranded RNA experiment — we activated the immune system, and it caused all these downstream effects on the fetus. And what does a vaccination do? It activates the immune system. That’s the point of vaccination. In practice, not all pregnant women receive flu shots, and I think that universal vaccination of pregnant women could get us into a whole new set of problems.
Dr. Patterson said it, so I don’t have to be the first to bring it up. He said a vaccination “activates the immune system” and he also told us that “immune activation” can cause autism. How exactly does a vaccine activate the immune system?
Discovery #2: Aluminum Adjuvant causes immune activation and is far more neurotoxic than previously thought
Aluminum compounds (Al hydroxide and Al phospate) are the most common adjuvants used in vaccines. They are currently used in the hepatitis A, hepatitis B, diphtheria-tetanus-pertussis(DTaP, Tdap), Haemophilus influenzae type b (Hib), human papillomavirus (HPV) and pneumococcus (PCV) vaccines. Aluminum adjuvant “activates” the immune system, which induces long term immunity to antigens in the vaccine. The scientific understanding of aluminum adjuvant toxicity has changed and deepened dramatically in recent years.
In fact, the published research on aluminum adjuvant is so new it has not even been considered by our FDA or CDC, who are still basing their recommendations about aluminum use in vaccines on a study published in 2011 that erroneously concluded that aluminum from a vaccine likely ends up in the body’s skeletal system:
“While the contribution of vaccines to an infant’s aluminum body burden can be slightly higher than that of the dietary contribution in our model, the fact that the primary pool where the aluminum is residing, as a long-term storage depot, is likely to be skeletal and not a more sensitive soft organ system is reassuring.”
Most of the guess work about aluminum is based on dissolved aluminum, not aluminum hydroxide, which is the type of aluminum used in vaccines. We’re now learning that aluminum hydroxide is a nanoparticle, absorbed by our body’s macrophage (the immune system’s garbage man) where the macrophage can then easily transport the aluminum hydroxide to the brain (the macrophage passes easily through the blood-brain barrier). If you’d like to see a complete takedown of the “safe level” of aluminum argument still made by the FDA and CDC, see VP’s excellent work, here’s a short excerpt:
“It is not reasonable or scientific to use studies of ingested, water-soluble aluminum salts (like AlCl3 or Al-lactate) to establish a safe dose of injected aluminum adjuvant (comprising aluminum hydroxide/phosphate nanoparticles). The chemical forms and route of administration are different. It is well-established today that nanoparticles can have higher toxicity than bulk orsoluble forms of the same material…It’s the vaccine promoters that created this inherently-invalid approach to aluminum adjuvant safety. Vaccine critics including me argue that the safety of injected aluminum adjuvant can only be tested using injected aluminum adjuvant, not ingested aluminum salts like AlCl3 or Al lactate. This should be common sense. So, leaving aside the important issues of nanoparticle toxicity and administration route, I want to address the question: is it really true that animals (mice or rats) are not harmed by ingesting 62mg/kg/day or 26 mg/kg/day aluminum? After all, this is the fundamental basis for aluminum adjuvant safety. Vaccine promoters rely on Keith and Mitkus to make the case that aluminum adjuvant is safe, and Keith and Mitkus depend on the claim that these dosages are safe for animals to ingest. If the 26 mg/kg/day dosage is in fact harmful to animals, then the analyses by Keith and Mitkus are wrong and unsalvageable. Several studies clearly demonstrate that dosages much lower than 26 mg/kg/day are harmful, and they are presented below.”
The first time I personally woke up to the the idea that the aluminum adjuvant used in vaccines might be far more toxic and dangerous than I knew was when I started reading about the incredible work of Dr. Chris Shaw at the University of British Columbia in Canada. In 2007, Dr. Shaw published the first study looking at injected aluminum adjuvant in this paper, Aluminum Adjuvant Linked to Gulf War Illness Induces Motor Neuron Death in Mice and sounded a worldwide alarm about the dangers of aluminum adjuvant:
“In addition, the continued use of aluminum adjuvants in various vaccines (i.e., Hepatitis A and B, DPT, and so on) for the general public may have even more widespread health implications. Until vaccine safety can be comprehensively demonstrated by controlled long-term studies that examine the impact on the nervous system in detail, many of those already vaccinated as well as those currently receiving injections may be at risk in the future. Whether the risk of protection from a dreaded disease outweighs the risk of toxicity is a question that demands urgent attention.”
In 2009, Dr. Shaw’s and his colleagues in British Columbia published another study looking at injected aluminum hydroxide, and the results were deeply disturbing:
“Overall, the results reported here mirror previous work that has clearly demonstrated that aluminum, in both oral and injected forms, can be neurotoxic. Potential toxic mechanisms of action for aluminum may include enhancement of inflammation (i.e., microgliosis)…”
Three years after his groundbreaking study, Dr. Shaw and his colleague, Dr. Lucija Tomljenovic, published this paper in 2012, expressing grave concerns about the limited understanding of aluminum adjuvant’s toxicity:
“…it is somewhat surprising to find that in spite of over 80 years of use, the safety of Al adjuvants continues to rest on assumptions rather than scientific evidence.For example, nothing is known about the toxicology and pharmacokinetics of Al adjuvants in infants and children…Yet, in spite of these observations children continue regularly to be exposed to much higher levels of Al adjuvants than adults, via routine childhood vaccination programmes.”
The two scientists called for an urgent reevaluation of the safety profile of aluminum adjuvant-containing vaccines:
“However, the existing data (or lack thereof) raise questions on whether the current vaccines aimed at pediatric populations can be accepted as having adequate safety profiles. Because infants and children represent those who may be most at risk for complications following vaccination, a more rigorous evaluation of potential vaccine-related adverse health impacts in pediatric populations than what has been provided to date is urgently needed.”
In 2013, French scientists demonstrated that aluminum adjuvant, when injected into the body of a mouse, ended up in the brain 1 year later. The study authors expressed serious concerns about this very new discovery:
“However, continuously escalating doses of this poorly biodegradable adjuvant in the population may become insidiously unsafe, especially in the case of overimmunization or immature/altered blood brain barrier…”
The authors chose their words carefully, recognizing the ubiquity of aluminum adjuvant’s use in pediatric vaccines all over the world, which is why their choice to call aluminum adjuvant “insidiously unsafe” should cause any parent worry. Unfortunately, the very thing they express real concern about — escalating doses — is exactly what has been happening to children since the early 1990s, when the immunization schedule in the U.S. and all over the world more than tripled, largely due to new vaccines being introduced that contain aluminum adjuvant.
In 2015, another study from Université Paris Est Créteil (UPEC) in France further supported this new view of aluminum adjuvant as a dangerous, biopersistent, and ultimately brain-injuring toxin. (The study confirmed that aluminum adjuvant slowly makes its way to the brain, where it then stays, possibly forever.)
The study explained that aluminum adjuvant can generate a long-term immune response because of its “biopersistence”, which basically means our body has no ability to rid itself of aluminum adjuvant, because its a man-made substance we have no natural designs to eliminate:
“Thus alum and other poorly biodegradable materials taken up at the periphery by phagocytes circulate in the lymphatic and blood circulation and can enter the brain using a Trojan horse mechanism similar to that used by infectious particles. Previous experiments have shown that alum administration can cause CNS dysfunction and damage, casting doubts on the exact level of alum safety.”
And, in 2016, the most important and revealing study yet done on aluminum adjuvant provided more bad news, and more insight.
It’s safe to say that this study’s conclusions have revolutionized our understanding of aluminum adjuvant. From the journal Toxicology, the French study authors were very concerned about the widespread use of aluminum adjuvant:
“Concerns about its [aluminum adjuvant’s] safety emerged following recognition of its unexpectedly long-lasting biopersistence within immune cells in some individuals, and reports of chronic fatigue syndrome, cognitive dysfunction, myalgia, dysautonomia and autoimmune/inflammatory features temporally linked to multiple Al-containing vaccine administrations.”
They also discovered, through mouse-models, a deeply alarming unique characteristic of aluminum adjuvant: low, consistent doses were MORE neurotoxic than a single bolus dose:
“We conclude that Alhydrogel [aluminum adjuvant] injected at low dose in mouse muscle may selectively induce long-term Al cerebral accumulation and neurotoxic effects. To explain this unexpected result, an avenue that could be explored in the future relates to the adjuvant size since the injected suspensions corresponding to the lowest dose, but not to the highest doses, exclusively contained small agglomerates in the bacteria-size range known to favour capture and, presumably, transportation by monocyte-lineage cells. In any event, the view that Alhydrogel neurotoxicity obeys ‘the dose makes the poison’ rule of classical chemical toxicity appears overly simplistic.”
This a counter-intuitive conclusion, but profoundly important, so I’m bringing in VP to further explain:
A paper (Crepeaux et al.) by the Gherardi research group in France reports important results on the toxicity and transport of aluminum (Al) adjuvant in mice. This single study is especially valuable because it looked at many outcomes: behavioral effects, immune (microglial) activation in the brain, and Al transport into the brain. The study tested dosages of 200 , 400 and 800 mcg/Kg, injected intramuscularly (IM). The Al adjuvant used was AlOH (brand name Alhydrogel), the most common vaccine adjuvant in use today. It is used in the tetanus, Hep A, Hep B, HiB, pneumococcal, meningococcal, and anthrax vaccines. Remarkably, the study found that the lowest dosage (200 mcg/Kg) was the most toxic! For many outcomes, the 400 and 800 mcg/Kg dosages had no observable adverse effects, but the 200 mcg/Kg dosage did. The low toxicity of the higher dosages appears to be a consequence of dosage-dependent inflammation at the injection site. The high dosages caused intense inflammation at the injection site, forming “granulomas”. The 200 mcg/Kg dosage did not produce granulomas. Granulomas are hard nodules in tissue produced in response to injury, infection or foreign substances. Its a way the body “walls off” injured tissue and prevents the spread of infection or toxins. The granuloma appears to provide protection from Al adjuvant toxicity; apparently the granuloma prevented Al adjuvant particles from leaving the injection site. This explains why the 200 mcg/Kg dosage affected the brain and behavior, while the higher dosages did not. This suggests that it is more dangerous and harmful to administer numerous small injections of Al adjuvant, compared to a large single injection capable of inducing a granuloma.
The study authors also disputed the way the FDA and CDC currently think about aluminum adjuvant toxicity, basically saying that the current approach is wrong:
“As a possible consequence, comparing vaccine adjuvant exposure to other non- relevant aluminium exposures, e.g. soluble aluminium and other routes of exposure, may not represent valid approaches.”
And, the French scientists finish with a conclusion that all parents should find very troubling:
“In the context of massive development of vaccine-based strategies worldwide, the present study may suggest that aluminium adjuvant toxicokinetics and safety require reevaluation.”
Guillemette Crepeaux
Discovery #3: Aluminum can increase IL-6 in the brain
One of the only frustrations of the remarkable toxicity studies on aluminum adjuvant coming out of France is that many scientists did not explicitly measure the mice brains for the cytokine IL-6 which we know can be released during an immune activation event and also know is strongly associated with causing autism. But, a study from the Middle East provides a strong foundation for the IL-6-aluminum adjuvant connection.
“The results also showed that aluminum administration increased the hippocampus pro-inflammatory cytokines TNF-α by 3.8-fold, IL-6 by 4-fold, and iNOS by 3.8-fold compared to the normal control group.”
If any of this remains confusing, I think VP’s description of aluminum adjuvant in the body will fill in any holes:
Most vaccines contain aluminum, and aluminum is a proven neurotoxin, in amounts received from vaccines. Vaccines in combination can result in toxic aluminum overload. Even the aluminum in a single vaccine can be harmful because the aluminum is in a form that is more dangerous than ingested aluminum. Specifically, vaccine aluminum is in nanoparticulate form, which is harder for the body to eliminate, and because it is transported around the body differently than ingested aluminum.
It is natural and normal to ingest small doses of aluminum from food and water. Its not good for you, but the body has adequate defenses. Absorption of ingested Al is low, about 0.3%, so about 99.7% is eliminated in feces. Ingested aluminum is in ionic form (individual charged atoms), which is readily removed by the kidneys. Also, ionic aluminum is blocked from entering the brain by the blood brain barrier. The low absorption, rapid elimination by the kidneys and barrier to brain entry adequately protects the brain from aluminum.
However, nanoparticulate aluminum from vaccines cannot be removed by the kidneys. The particles are far too large to be filtered out by the kidneys. The Al nanoparticles do dissolve slowly (converting to ionic aluminum). But long before they can dissolve completely, the Al nanoparticles are “eaten” by immune system cells called macrophages. In other words, the particles wind up inside the macrophages. Once loaded with the Al nanoparticles, the macrophages spread aluminum as they travel through the body. This is dangerous, because the Al-loaded macrophages carry Al nanoparticles to tissues (e.g. the brain) that are damaged by very small amounts of aluminum.
Quick Pause: The chicken-egg of immune activation
I want to address a topic that triggered much of the exploration that drove me to write this article in the first place. Back in the day, I got into a bit of a public squabble with Dr. Peter Hotez, a vaccine patent holder who also serves as a spokesperson for the vaccine industry. Dr. Hotez also has a daughter with autism, so this debate is very personal for him, as it is for me. Dr. Hotez is convinced that autism is “created” in utero as he explained to me, “my read of the scientific literature is that brains of children with autism, like ours, were that way by the first or second trimester of pregnancy.” Dr. Hotez bases his conclusion about autism’s timing on the work of a single study by Dr. Eric Courchesne and colleagues titled, “Patches of disorganization in the neocortex of children with autism.”which was published in 2014 in the New England Journal of Medicine. Dr. Hotez even took his refutation of some of the things I have publicly written about autism and vaccines a step further, and I think this is really the dividing line for many scientists, he wrote to me:
“A vaccine given in the first year of life could not possibly cause a total reorganization of the brain architecture, it just defies reason.”
Does it? Does it defy reason that the re-wiring of the brain — that we now believe is caused by an immune activation event — could never happen after a child is born?
This is the single most important question that needs to be answered to determine autism’s cause, and I think the answer will govern the autism causation debate from here on out:
· If vaccines cannot cause a “reorganization of brain architecture” after a child is born, then vaccines are unlikely to be the cause of autism (however, vaccines given to a pregnant women may still pose a risk to triggering a Maternal Immune Activation).
· If, however, vaccines given after birth can cause the brain to “reorganize”, then we have a serious, serious problem with vaccines.
I believe the science is very clear on this point. Read on.
The evidence for post-natal autism triggers is strong
The study that Dr. Hotez mentioned to me, the study that proved to him that autism was determined in utero, I have now read probably a dozen times. You can read it for yourself, it’s a study where scientists looked at the actual post-mortem brains of children with autism, and found striking differences in brain architecture. What the study didn’t do, because it would be impossible to do with post-mortem brains, some as old as 15 years, was speculate exactly WHEN the brain disorganization took place. And, really, how could they? I’m guessing Dr. Hotez was thrown off by the conclusion of this study, where the authors offered up a guess:
“In conclusion, we identified discrete patches of disorganized cortex in the majority of postmortem samples obtained from young autistic children that we examined. These patches occurred in regions mediating the functions that are disturbed in autism: social, emotional, communication, and language functions. Such abnormalities may represent a common set of developmental neuropathological features that underlie autism and probably result from dysregulation of layer formation and layer-specific neuronal differentiation at prenatal developmental stages.”
Did you catch what the study said, the part that Dr. Hotez turned into fact to support his claim (and by the way he has cited this study repeatedly in public writings about autism’s cause)? The authors said the disregulation they saw in the brains of children “probably” happened during “prenatal development stages.” I think the evidence you will see actually points to the opposite. VP explained it well:
The “patches of disorganization” paper is actually further evidence implicating immune activation and therefore vaccines. Immune activation experiments have shown that immune activation/cytokines causes disruption of neuron layers. So a vaccine could definitely do this. I believe that autism-associated differences in the prenatal period are simply indicators that the baby is particularly susceptible to immune activation injury. Immune activation works like this: each time there is an activation event, the immune system becomes more sensitive and reactive to immune stimulus. So, an activation “hit” during gestation can render the baby more susceptible to immune activation injury postnatally. This increased reactivity is known to occur with microglia in the brain (microglia are immune cells in the brain). its called “microglial priming”. Once microglia are primed by immune activation, they become hyperreactive for a long time, perhaps a lifetime.
VP went a little farther than Dr. Hotez did, providing this image which is hard to shake once you’ve seen it:
What you can see fairly clearly is that the brain is far from done developing once a child is born. In fact, 5 separate phases of brain development are either in process or yet to start. Could an immune activation event after the child has been born impact brain development? Yes, it could.
And, the published science also supports this view. In a study done in 2012, Wei and colleagues induced autism-like symptoms in mice by injecting them with IL-6 AFTER they were born. This is NOT a maternal immune activation event, this is an immune activation event of a newborn that leads to the development of symptoms of autism.
“Here we show that mice with elevated IL-6 in the brain display many autistic features, including impaired cognitive abilities, deficits in learning, abnormal anxiety traits and habituations, as well as decreased social interactions. IL-6 elevation caused alterations in excitatory and inhibitory synaptic formations and disrupted the balance of excitatory/inhibitory synaptic transmissions. IL-6 elevation also resulted in an abnormal change in the shape, length and distributing pattern of dendritic spines. These findings suggest that IL-6 elevation in the brain could mediate autistic-like behaviors, possibly through the imbalances of neural circuitry and impairments of synaptic plasticity.”
Still think Dr. Hotez has a point, that autism happens during gestation or never? Then this study will really blow your mind, from all the way back in 1981.
In this case study of three children, published in Child Neurology, the authors describe three cases of sudden onset autism, all caused by infection and inflammation of the brain.
It appears that not only can an infection trigger an immune activation event that leads to autism after a child is born, it can even happen to a child who is 5, 7, or 11 years old (the ages of the three children in this study). Are you reading this, Dr. Hotez?
“During an acute encephalopathic illness, a clinical picture developed in three children that was consistent with infantile autism…In our cases, the abnormalities are acquired and not developmental, but they clearly fit the critical clinical features of the childhood autistic syndrome.”
Discovery #4: Hepatitis B vaccine induces IL-6 in postnatal rats
When this paper was published in China, no one I knew in the autism community mentioned it, I’m guessing because it was hard to patch together its significance. You had to appreciate all of Patterson’s work. You had to understand the IL-6 connection to autism. You had to appreciate the brand new insights about aluminum adjuvant toxicity, the low dose implications, and that aluminum adjuvant was ending up in the brain. And, you had to read a paper from China that covered a lot of other ground, as well as providing a missing link in the aluminum adjuvant-cytokine (IL-6)-autism hypothesis that it helped fortify.
VP has written extensively about this study, I will start by quoting VP, but if you want a highly detailed scientific analysis of this study, check this out.
“An important new study by Li et al. reports the effects of bacillus calmette-guerin (BCG) vaccine (for tuberculosis) and hepatitis B vaccine on brain development in infant rats. The study relates the observed brain changes to the type of immune activation (Th1 or Th2, explained below) stimulated by the vaccines. The BCG and hep B vaccines had opposite effects on the brain (BCG being beneficial, and hep B being detrimental), and a combination of both vaccines resulted in cancellation of the effects.
This is the first study to test the effects of immune activation by vaccination on brain development. All other studies of immune activation have used essentially pathological conditions that mimic infection and induce a strong fever. A criticism I have heard often from vaccine advocates is that the immune activation experiments are not relevant to vaccines because vaccines cause a milder immune activation than injections of poly-IC or lipopolysaccharide (two types of immune system activators). This new study demonstrates that vaccines can affect brain development via immune activation. Hence, the immune activation experiments are relevant to vaccines…The hep B vaccine increased IL-6 in the hippocampus (the only brain region analyzed for cytokines).”
And, VP continues, explaining the timing of the injury to the Hep B rats:
“An important finding in the rat BCG/Hep B study is that many of the effects of hep B vaccine did not appear until age 8 weeks. This finding undermines claims of vaccine safety, which are almost always based on short-term outcomes of a few days or weeks. Furthermore, 8 weeks is a long time in rats. 8 week old rats are almost fully mature adults. This suggests that adverse effects of vaccines may take years or decades to appear in humans. This is consistent with what is known about immune activation and schizophrenia. Immune activation in the fetus can cause schizophrenia 20–30 years later.
The accumulating scientific evidence and the Li et al study in particular suggest that vaccination may cause mental illness. The mental illnesses would emerge years or decades after vaccination of an infant. Vaccines are likely contributing the the rise of mental illnesses in the USA over the last 25 years. The rise in mental illnesses in the USA is coincident with the dramatic increase in vaccination that started in the 1980s.”
This study is extraordinary! There were three different groups of rats: rats receiving the BCG vaccine (not given in the U.S.), rats receiving the Hepatitis B vaccine (given on day 1 of life in the U.S.) and a control group with no vaccine. The BCG vaccine does NOT contain aluminum adjuvant and the impact on the rat’s brains from BCG was actually positive! The Hep B vaccine rats, however, showed the kind of immune activation event we are seeing in autism (high IL-6)
This is biological proof of the link between a vaccine — given to a post-natal animal — inducing an immune activation event, including the cytokine marker for autism, IL-6. A scientific first.
Discovery #5: High levels of aluminum in autism brains
Earlier, I mentioned the study published by Professor Chris Exley — “Aluminium in brain tissue and autism” — that found incredibly high levels of aluminum in the brain tissue of five people with autism. In an interview soon after his study was released, Dr. Exley explained:
“The amount of aluminum in the brain tissue was, I would say, extraordinarily high. Very high. My group has measured the aluminum content of probably more than one hundred human brains, and these brain tissues taken from the individuals with a diagnosis of autism were some of the highest we’ve measured bar none. The only ones we’ve seen that are similar were a recent study of familial Alzheimer’s. This in itself is a very important finding.”
Professor Exley and his colleagues were startled by something else: the location of the aluminum within the brains:
“Perhaps equally important if not more important were the microscopy studies. The microscopy studies enable us to identify where the aluminum was in the brain tissue. When we looked at our brains of people with a diagnosis of autism, we found something completely different and something we’ve never seen before as yet in any other set of human brains. We found that the majority of aluminum was actually inside cells, intracellular. Some of it was inside neurons, but actually the majority of it was inside non-neuronal cell populations. So we found that these cells were heavily loaded with aluminum. We also saw evidence that cells in the lymph and in the blood were passing into the brain, so they were carrying with them a cargo of aluminum from the body into the brain. This is the first time in any human brain tissue we have seen this so this is a standout and as yet unique observation in autism. For myself, it very much implicates aluminum in the etiology of autism.”
What Professor Exley found were macrophages, the kind the French scientists discovered were transporting aluminum into the brains of mice, loaded with aluminum, and serving as carriers to bring the aluminum into the brain. Dr. Exley’s study showed that the conclusion being drawn in the laboratory with mice were equally true in the brains of people with autism. It turns out the biological experiments using mice to gauge the impact of injected aluminum adjuvant were equally accurate when extrapolated to humans. In fact, Professor Exley was so shocked by the findings, it altered his view of the safety of using vaccines containing aluminum.
“I did not see a role for aluminum in autism. And I didn’t see a role for aluminum in vaccines in autism. I have to change my mind now on both of these. I have to change my mind that aluminum has a role in autism, I believe it now does. Now, because I have seen the same cells that we will see at an injection site carrying a cargo of aluminum into the brain tissue of individuals who died with autism I would now say that we have to think very carefully about who receives a vaccine that includes an aluminum adjuvant. We need to think carefully, is this vaccine a life-saving vaccine or not? If it isn’t, don’t have it with an aluminum adjuvant.”
Dr. Exley just told parents not to get vaccines that constitute MOST of the childhood vaccine schedule. Dr. Exley, a tenured professor at Keele University of Bioinorganic chemistry and without peer the leading expert in the world on the neurotoxicity of aluminum. (Of course, like all scientists willing to touch this topic, Dr. Exley was pushed out of Keele University in 2021).
As an aside, and as to be expected, Dr. Exley’s study was subjected to withering criticism. As a parent really only interested in the TRUTH, I’m fine with this, it’s important that every meaningful criticism is considered and every conclusion criticized. I sent Dr. Exley’s study to a former colleague of Dr. Paul Patterson. He’s not impressed, he writes, “I honestly don’t think it should have been published because it has a critical scientific flaw… The authors didn’t use any healthy control tissue, so we have no way of knowing what normal Al levels in a brain would by their method. Imagine, for example, if the blades they used to cut the brains had trace levels of Al that contaminated their tissue. If they had used healthy controls, you would have also seen high Al levels in the healthy brains as well. Since they had no such controls, their results are scientifically meaningless.”
I share this response, in an email exchange, with Dr. Exley himself. His unedited response:
“Our measurements of Al in human tissue are the most respected anywhere and the reasons for this are our attention to all details and specifically extraneous contamination as suggested by this person. Please see the Metallomics paper cited in our paper to provide a specifc response to this. Our quantitative analyses on the brains of 5 individuals represent the ONLY donors available at the autism brain bank in the UK. We discussed control tissues but the only available were not age-matched and nor were they true controls as the donors were individuals in their 40s and 50s who died of a certain disease or condition. No age-matched healthy donor brain tissues were available. However, we have more data on the Al content of human brain tissue than anyone else and so we are in a position to compare our autism data with other data relating to almost 100 human brains. This is how we can come to our judgement that the values measured were some of the highest values ever measured in any individuals. No one questioned similar data published this time last year for familial AD.”
I ask him that it’s been like since the study was published, is it being considered by any “mainstream” scientists or organizations? What is the political fallout from your study like? Do you have a concern of being “Wakefielded” for your study (which, of course, he was)? He responds:
“There is a blackout of this research by mainstream media. My research on Al has experienced something similar for many years though perhaps much more so in the last few years. The science is extremely robust and therefore the only defence is to ignore it!”
Five discoveries, a clear path to autism
Here’s a simple graphic that I think spells out the process of triggering autism very clearly, as demonstrated by the published science I have just shared with you:
(This graphic is from a great brochure created by Vaccine Papers, you can get a complete copy right HERE.)
Published studies are showing that autism is caused by an immune activation event. The adjuvant in vaccines — aluminum adjuvant — can activate the brain’s immune system and is far more neurotoxic than previously realized — all the new science has been published in just the last few years. Aluminum can cause IL-6, the key cytokine implicated in autism. Chinese scientists — for the first time anywhere in the world — used a vaccine to trigger an immune activation event, and recorded elevated levels of IL-6 in rats. THIS is a biological basis for HOW a vaccine can cause autism. Remember what Dr. Hotez said to me? He said:
“A vaccine given in the first year of life could not possibly cause a total reorganization of the brain architecture, it just defies reason.”
But, that’s exactly what the science is showing us. Vaccines, administered early and often, are igniting immune activation event after immune activation event. Here’s a different chart looking at the development of the brain over time, from a neuro-immunological perspective. Imagine 6–7 immune activation events (right after they receive 4–6 aluminum adjuvant containing vaccines in a single appointment) in certain vulnerable children during critical phases of brain development. With everything you’ve just read, is it really that hard to imagine?
Among the variety of environmental factors suspected to contribute to the pathophysiology of NDDs [autism], repeated early exposures to aluminum (Al)-containing vaccines during critical developmental periods of both nervous and immune systems has received unique attention. In the past five decades, growing concerns have been raised among the scientific community and the general public, through sometimes counter-productive conflicts, on the effects and safety of these compounds within the organism. Among these questions, adjuvant kinetics and potential chronic adverse effects, especially when given early in life, are noteworthy
Implications and questions
I can’t help but tie everything I read and see here to my own son’s experience. Born in 2002, my son seemed to get sicker and more confused with every vaccine appointment, and his head always seemed to be hurting. And, with each appointment, unusual behaviors and odd movements began to appear. A really sad reminder of this reality appeared in a study published just last week in Nature, that described how children with autism developed enlarged foreheads:
“Brain enlargement has been observed in children with autism spectrum disorder (ASD), but the timing of this phenomenon, and the relationship between ASD and the appearance of behavioural symptoms, are unknown. Retrospective head circumference and longitudinal brain volume studies of two-year olds followed up at four years of age have provided evidence that increased brain volume may emerge early in development.”
Wouldn’t the above theory about how autism is triggered do a pretty good job of explaining why these children have large (swollen) heads? As you know, the immune activation event leads to what Dr. Patterson called “an ongoing, permanent immune-system activation in the brains of autistic people.” And, guess what, permanent immune system activation means inflammation…which would lead to a “large brain” and a “swollen forehead.” Is that why children with autism are known to head bang? Perhaps you would too if you’re brain was in a state of permanent inflammation?
Question: What about gastrointestinal disorders?
So many children with autism experience gastrointestinal disorders, my son most certainly did. And, gastrointestinal distress is now fully appreciated to be a “co-morbid” condition of autism. But what, exactly, might cause it? You don’t have to look too far:
“Aluminum increased the intensity and duration of macroscopic and histologic inflammation, colonic myeloperoxidase activity, inflammatory cytokines expression, and decreased the epithelial cell renewal compared with control animals. Under basal conditions, aluminum impaired intestinal barrier function. In vitro, aluminum induced granuloma formation and synergized with lipopolysaccharide to stimulate inflammatory cytokines expression by epithelial cells. Deleterious effects of aluminum on intestinal inflammation and mucosal repair strongly suggest that aluminum might be an environmental IBD risk factor.”
Question: What about all the other types of autoimmunity (food allergies, etc.) that are at epidemic levels, and often co-morbid with autism?
Spearheaded by Israeli scientist Dr. Yehuda Shoenfeld, the scientific evidence that aluminum adjuvant is causing epidemics of a wide variety of auto-immune conditions is becoming overwhelming. Dr. Shoenfeld even has his own text book explaining this!
“With the discovery of autoimmune/inflammatory syndrome induced by adjuvants (ASIA), the work of leading researchers from 14 countries on the role of adjuvants in different vaccines and how they can induce diverse autoimmune clinical manifestations in genetically prone individuals has been published in the newly released medical textbook, Vaccines and Autoimmunity.”
“Notwithstanding that molecular mimicry and bystander activation in a genetically predisposed individual have been called to be responsible, the finger should be pointed at the adjuvants. One in particular has raised several distresses: aluminum. Indeed, this has been used as an adjuvant for the past 90 years but it is also an experimentally demonstrated neurotoxin. Experimental research has showed that alum adjuvants have a potential to induce serious immunological disorders in humans. Thus, efforts should be put in clarifying the potential threat of alum-containing vaccines.”
Question: What about the MMR, it has no aluminum adjuvant?
The MMR vaccine does not contain aluminum adjuvant. Yet, many (but far from all) parents point to the appointment where their child received the MMR vaccine as a trigger for autism. We need more scientific data than we have about what exactly the MMR vaccine does to the brain (does it generate IL-6 or other cytokines?), but because we don’t know, we’re left to speculate.
One obvious answer is that the MMR vaccine is the first live virus vaccine children receive (it’s typically given between age 12–18 months, most children have received 15–20 vaccines by then), and it’s a triple (measles, mumps, rubella) live virus. For an immune system bathed in aluminum adjuvant and possibly already simmering with activation events, this triple dose might push a child right over the edge. This might explain the seizures (an extreme immune activation event) that sometimes follow the MMR appointment. We also know that children who also receive the varicella vaccine (chicken pox) along with the MMR have higher rates of seizure events. This would make sense, four live viruses at once would likely challenge the immune system more than three, but we can’t explain exactly how the MMR biologically impacts the immune system the way we can for aluminum adjuvant, and now for Hepatitis B vaccine (thanks to Chinese scientists). Dr. Yehuda Shoenfeld discusses the fact that a live vaccine activates the immune system more than a vaccine using aluminum adjuvant:
“It is evident that a live attenuated vaccine is more prone than a killed vaccine to activate the immunity response.”
But, a more obvious explanation has recently emerged. Namely, the MMR vaccines triggers something in the body known as MCP-1, which serves as a beacon to encourage aluminum-laden macrophages to rush to the brain. I’ll let VP explain:
“When MCP-1 is produced by microglia, macrophages from around the body travel into the brain…‘MCP’ stands for ‘macrophage chemoattractant protein’, which of course describes its primary function of summoning macrophages…MCP-1 production is stimulated by some types of immune activation. Hence, a vaccine that stimulates MCP-1 may cause AANs [aluminum adjuvant nanoparticles](e.g. from prior vaccines) to move into the brain. Some infections or toxins induce MCP-1. Interestingly, Al adjuvant induces MCP-1, suggesting that it may stimulate its own transport…We can speculate that AANs from vaccines may remain ‘dormant’ for years, until MCP-1 production is stimulated. The MCP-1 will cause macrophages containing AANs to mobilize and transport AANs into the brain and other sensitive tissues. This may explain some of the damage from the MMR vaccine. MMR is given at 15–18 months of age, which is after Al-containing vaccines are given (at 0, 2, 4, and 6 months). The measles vaccine can stimulate MCP-1 production. Therefore, the MMR vaccine may stimulate the movement of AANs (received from prior vaccines) into the brain. This may explain how MMR could cause Al toxicity, even though it does not contain aluminum adjuvant.”
Question: Didn’t they already prove vaccines don’t cause autism?
If you’ve read this far, I assume you already know this is a fable. If you’re unsure, just look at this simple graphic. All those vaccine industry spokespeople who say “the science is settled” fail to mention that only one ingredient (thimerosal) and one vaccine (MMR) has ever been looked at for its relationship to autism.
No vaccine containing aluminum adjuvant has ever been explored for its relationship to autism, despite a growing and clear body of evidence implicating aluminum adjuvant in causing “immune activation,” the central cause of autism.
It’s also worth pointing out that in the early and mid-2000s when parents first started sounding the alarm about the connection between vaccines and autism, we had no biological evidence to support our view, we just had the collective experience of seeing our children disappear after vaccine appointments. Today, it’s a completely different world. Consider the words of Dr. Kimberley McAllister of the UC Davis Mind Institute in 2016:
“These MIA (maternal immune activation) animal models meet all of the criteria required for validity for a disease model: They mimic a known disease-related risk factor (construct validity), they exhibit a wide range of disease-related symptoms (face validity), and they can be used to predict the efficacy of treatments (predictive validity).”
It’s time for the CDC, FDA, Autism Speaks, and the American Academy of Pediatrics to face the biological evidence staring us all in the face!
Question: Aren’t you just “moving the goalposts” on the autism-vaccine hypothesis?
Of course, critics will say this. First it was the MMR. Then it was mercury. Then it was “too many, too soon.” What’s different now is very important: overwhelming published, peer-reviewed science making a clear connection between immune activation events, aluminum adjuvant, and autism. That’s why this article is filled with study references, not conjecture.
What’s been true throughout the autism epidemic remains true today: an overwhelming (tens of thousands) number of parental reports of regression of their children into autism after vaccination.
Implications
I want to know what, exactly, happened to my son. When he was diagnosed with autism in 2004, the prevailing understanding of autism in the parent community was that it was growing exponentially, many parents were seeing changes after vaccine appointments, and that mercury or a live virus (measles) were the most likely causes. We had no biological science. The understanding of aluminum or the aluminum adjuvant was comically simplistic, almost a throw away point. We had no idea what an immune activation event, a cytokine, or IL-6 meant. (In fact, if you want a good laugh, see how Dr. Paul Offit is still describing aluminum adjuvant, despite its now proven extreme neurotoxicity. He states: “Parents can be reassured that the trace quantities of aluminum in vaccines can’t possibly do harm.” Based on published science beginning in 2009, this is an unsupportable lie.)
Everything you have read so far is based on published science. The grand theory of autism’s causation, in my opinion, holds together pretty strongly.
Will we look back one day and say that aluminum adjuvant caused the autism epidemic the way we say that Thalidomide triggered birth defects? I think we will, but that’s just my opinion.
Next Steps
I believe we may be far closer to a complete explanation of how autism — and many related autoimmune conditions — are being caused. Scientists from all over the world have created a compelling body of work to support an almost complete biological understanding of how autism is triggered by aluminum adjuvant inside the body, creating an immune activation event, and leading to autism — most of this research has been published in just the last 10 years. And none of it from Americans.
Is everything published and written here true? Could the explanation really be that simple? Did a rising number of vaccines containing the aluminum adjuvant trigger an autoimmune epidemic, of which autism is the most severe, but not only, manifestation? Does an epidemic of food allergies, ADHD, learning disabilities, eczema, and diabetes fall into the same realm of causation?
Dr. Chris Shaw of Canada
Is is possible that injecting an immune system antagonist (aluminum adjuvant), all but guaranteed to cause immune activation events, has done just that in the brains of many of our children? Do even mildly impacted children also suffer from a permanent, simmering brain immune system activation? Should we believe the growing body of scientists from all over the world who are sounding the alarm about the impact injected aluminum adjuvant is having on our children?
Will these scientists who have published all this wonderful work pool their collective expertise and let the world know what they are learning? Will they take their exhortations for caution and further exploration — all buried inside their published studies — and publicly warn parents about what is becoming so clear? (In fact, many scientists tried to do just that, see the Appendix.)
In my opinion, we are much, much closer to understanding how autism has been triggered in so many children, and I hope this article is another step on the path to the truth. And, for so many of you out there doing everything you can to help your son or daughter with autism live the best possible life, perhaps a clearer understanding of how their autism was triggered will improve their chances for recovery.
Because VP was really my teacher on this topic, I will give them the last word:
Like any other medical treatment, vaccination must be justified in view of an objective risk/benefit analysis. All risks and benefits must be considered. Any rational medical treatment must do more good than harm. This is universally accepted.
The problem with vaccines is that risks have been underestimated, and the benefits overestimated. In particular, the risk of brain injury from vaccines is much higher than commonly believed. Brain injury can be devastating to the life of a child, and the child’s family. The personal and financial costs of vaccine injury are often enormous. Therefore, even a small risk of brain injury must be considered seriously. And the science strongly suggests that the risk is not small.