My 16-minute interview of Jennifer, a former police detective in a major US city who handled over 250 SIDS investigations over 7 years implicates the childhood vaccines as the major cause of SIDS.
The best way to prevent SIDS is to stop vaccinating kids. In every study published in the medical peer-reviewed literature comparing fully vaccinated with fully unvaccinated children in the US, the fully unvaccinated kids were dramatically healthier with far fewer chronic diseases including autism. In 2009, nine House members co-sponsored a bill to require the NIH to do a study that would show this, but the bill never made it out of committee. Congress doesn’t believe that the American public want to know the truth about the childhood vaccines.
Executive summary
Sudden Infant Death Syndrome (SIDS) happens to babies, from 1 month to 1 year in age, but most frequently between 2 and 4 months of age.
Recently I interviewed a former police detective who handled over 250 SIDS cases for a major US city. She revealed her full name and I was able to independently verify her employment at the police department.
In the interview, she revealed that 50% of the SIDS cases happened within 48 hours after a vaccine was given and about 70% of the cases happened within one week of a vaccine.
This can only mean one thing: that the childhood vaccines are the leading cause of SIDS deaths.
There is no other explanation.
Even her pediatrician acknowledged this, but they aren’t allowed to talk about it. She said that the American Academy of Pediatrics trains the pediatricians in how to gaslight parents who seek to blame the vaccine.
This is the first time these statistics have ever been revealed publicly.
All the information is independently verifiable in the police records for any health authority who has any doubts.
Also, I am working with the police department to make these statistics public directly from the police department itself (I cannot compel the production of these records because the FOIA laws in the state exempt these records).
My 16-minute interview
The key points
3 to 4 cases per month, so over 250 cases total during her tenure
50% of SIDS cases happened within 48 hours of a vaccine administration. Assuming kids are vaccinated every month (which is the most conservative assumption), the chance of this happening by chance is 1.23e-64. This means the cases were caused by the vaccine since there is no other viable hypothesis that can explain the evidence.
70% of SIDS cases happened within 1 week of a vaccination.
Her pediatrician acknowledged this and didn’t argue with the data.
The American Academy of Pediatrics trains doctors on how to gaslight patients who suspect the vaccine caused their child’s death.
Jennifer declined to publicly reveal her name or the police department she worked for, but revealed this to me so I could verify everything using independent sources.
The police department declined to respond to my records count request because it is outside the scope of the state’s FOIA laws since it cannot be accomplished with a straightforward query and “research” would be required. I agree with their interpretation, but I’ve requested they comply anyway as a matter of public benefit. I will update this article when I hear back from them.
Police policy is to “leave no stone unturned.” But even after they made the vaccine connection, the coroner ALWAYS ignored even mentioning the vaccine in the autopsy report!
Jennifer wrote me:
Standard police policy was to ask about ANY pharmaceuticals. So while no detective is given a script per se, they are trained on ANY death investigation, of any age, to ask about pharmaceuticals so I guess you’d say unwritten policy only because the official training is “leave no stone unturned “ and ask every single thing that person was doing in the moments hours days and weeks leading up to their death (if it was not an obvious cause of death)…so with a baby: “when was the last time he saw a doc? Was he healthy? any meds or shots ? What has he been eating? What kind of soap do you wash him with? Was he ever out of your care? And if so who was with him?” Would be a typical line of questioning. And my husband just reminded me that the coroner who we had to often report to was especially a stickler on everything that went into that kid food and drug wise. So we just by default always asked since odds were we’d have him answering the call and if we didn’t we’d he’d to go back and get the info for him. Now the irony in that of course is even though we got him all the info, vaccines were never the “cause of death” or even mentioned in final death reports.
Jennifer’s SIDS statistics are validated in the peer-reviewed medical literature!
Of all reported SIDS cases post-vaccination, 75 % occurred within 7 days (p < 0.00001).
This almost exactly matches what Jennifer said in my interview (70% within one week). Neither of us was aware of this article at the time we made the video.
This is impossible if the vaccines aren’t causing SIDS. There is simply no other viable explanation for the association. But of course, you won’t get your paper published if you say that. You have to say that the association is interesting.
Paper by CDC authors observes that nearly 80% the child deaths reported in VAERS happened after multiple vaccinations were given on the same day
Jennifer is not the only police detective to figure out the connection; Helen Grus in Ottawa found the same thing
In Canada, if you are a police officer and suspect that vaccines cause SIDS, they will prosecute you. It seems that is illegal in Ottawa to question the safety of the vaccines:
Helen Grus is a Forensic Police Detective in Canada who was looking into the sudden infant deaths that appeared to be connected to mothers being vaccinated.
For the last 2 years she was stoned walled by her own police force. Her court case resumes Oct 2023 and will drag into 2024.
She is being persecuted for seeking the truth. I hope that Detective Helen Grus will be exonerated and continue to investigate the “baffling mystery” of dead babies.
She was suspended without pay for not taking the COVID vaccine and she doesn’t think masks are effective either.
In short, they are trying to get rid of critical thinkers that are trying to get to the truth in the Ottawa police department.
See also these articles which cast Grus as the problem, rather than the vaccines:
Here’s a story casting Grus in a favorable light, pointing out that she didn’t violate any policy of the department and that the police department illegally provided documents to CBC Ottawa reporter Shaamini Yogaretnam which is a criminal offense, yet nobody in the police department is being charged with a crime. Former Toronto police detective Donald Best is baffled that Grus was charged at all, given the investigative discretion bestowed to all police officers. He pointed out that “a fourth-class constable on his or her first day on the job has all the authority to initiate any investigation they want to from parking tickets to homicide.”
That article points out that the investigating official, Chris Renwick, is denying discovery requests and refusing to investigate the source of the leak even though it is a criminal offense.
In short, this isn’t justice. They are stacking the deck against Grus, rather than following the law. CBC is ghosting requests for comment from True North.
Please check out Helen Grus on X
I agree with most of the commenters that Helen Grus is a hero who should be recognized as such.
There is a wealth of information on X here and here.
Here’s one that sticks out for me. Basically, the Ottawa police are instructed never to investigate the vaccine as a cause of harm:
How do they explain a 2X to 3X rise in SIDS in 2021 vs. 2020?
Watch this video starting at 0:56 which points out that there was a 2X to 3X increase in SIDS cases after the vaccines rolled out. Are you surprised? This is what got Helen’s attention.
A case history of how vaccines cause SIDS and that the medical examiners are gaslighting parents
Read this article. It describes how Sawyer, just 8 weeks old, died just 34 hours after a series of vaccines. The police suspected the parents were at fault and the medical examiner said the death was caused by improper sleeping position and refused to do any tests that might implicate the vaccine. The psychiatrist also told the mom she had an “adjustment disorder.” Four months later, a pathologist ordered the requested tests be done, and it clearly implicated the vaccines as the cause of the SIDS death.
Peer-reviewed literature says the more vaccines, the higher infant deaths. The r value is a stunning .992. You rarely a correlation coefficient this close to 1 in any real-world data.
The peer reviewed medical literature says this: “The mean IMRs of all nations within each group were then calculated. Linear regression analysis of unweighted mean IMRs showed a high statistically significant correlation between increasing number of vaccine doses and increasing infant mortality rates, with r = 0.992 (p = 0.0009).”
In plain English, yes, the more vaccine doses, the higher the infant mortality rates.
A real world experiment in Japan is consistent with the hypothesis
I will post a reference when I get it, but in the meantime:
A real world experiment in New Zealand
Thirty years ago in New Zealand the vaccine schedule was changed from the first being at 3 months down to 6 weeks. SIDS moved with it.
Hilary Butler in New Zealand compiled a gold mine of information as she ran the “Immunisation Awareness Society” at that time and published a monthly newsletter.
In 2020 when we were locked down at least through June, Nicole DeGraf, the former executive director of Oregonians for Medical Freedom, and myself, looked at the infant deaths under the age of 1 through the first six months of that year. All medical procedures, including well baby visits were cancelled through the end of June. The number of infant deaths during that period of time dropped to 42% of the ten year annual average of infant deaths in the state.
Seven more studies showing vaccines cause SIDS compiled here
See Vitamin D wiki which was instantly updated to add a link to this article as well.
The connection between vaccines and SIDS has been known for decades
Viera Scheibner, a Slovak research scientist living in Australia, accidentally discovered during her testing of baby monitors that babies were dying soon after receiving vaccines.
This book is essential reading for anyone who has any interest in the issue of vaccinations. There are numerous commentaries, opinions, and statistics on the subject, but Scheibner takes you to the source: the actual data from 100 years of mainstream studies conducted on vaccinations and their effects. A Ph.D. scientist, Scheibner has written a first-rate literature review that would allow readers to judge for themselves what the data has to say about each vaccine and its surrounding issues (e.g. effectiveness, risk of disease without vaccination, side effects, and more). To top it off, the book is an engrossing and easy read. Scheibner presents not only summaries of shocking empirical evidence, but she narrates it in a broad historical context that offers insight on how vaccines persisted despite damaging data throughout their history.
Scheibner stumbled onto this field after finding a temporal correlation between the DPT vaccine and a baby breathing monitor she co-invented to help prevent SIDS.
This book is a result of years of subsequent literature research she conducted to investigate the issue further. She concludes from both the literature and her own research that vaccines “represent a medical assault on the immune system,” and shares with the reader the studies that convinced her–complete with information on results, sample sizes, control groups, and other details that would allow the reader to have perspective on the validity and limits of each study.
Summary
The childhood vaccines are causing most of the SIDS deaths.
It will take decades for the medical community to acknowledge this.
But the evidence is now in plain sight. The statistics don’t lie.
I’m working with the police department to release the actual statistics for all to see. Once that happens, we’ll publish a paper in the peer-reviewed medical literature.
But in the meantime, I thought you all should know the truth about the dangers of the childhood vaccines. This is just the tip of the iceberg for the harms caused by the childhood vaccines that the CDC will never acknowledge.
A long history exists of a wave of severe injuries following new vaccinations being introduced to the market. In most cases, those injuries were swept under the rug to protect the business.
In many cases, the severe “mysterious” injuries we see now are remarkably similar to those that were observed over a century ago. Unfortunately, a widespread embargo exists on ever allowing this data to come to light (as that would instantly destroy the vaccine program).
A variety of independent studies (summarized below) have shown that vaccines cause a wide range of chronic illnesses.
A 1990 book made a strong case that widespread vaccination was also causing an epidemic of widespread brain damage which was both lowering America’s IQ and causing a massive rise in violent crime.
In this article, we will also review exactly what in that 1990 book and the classic signs that can be used to determine if someone has a vaccine injury (along with the subtle more spiritual ones).
Note: due to the recent ACIP changes (the committee which decides which vaccines you take) and past interest in this article, I revised and updated it.
My mind often overlaps the past present and future onto themselves. Because of this, I will frequently recall events that happened in the past which perfectly mirror what is unfolding before us, and in turn, I’ve lost count of how many times I’ve witnessed humanity repeat its same mistakes or can see a slow motion train-wreck ahead on the horizon. During COVID, I realized we were again reenacting the same tragedy humanity had ever experienced since the smallpox vaccine was brought to the market and I had a thought. If people became aware of what had happened before and ended our collective amnesia, perhaps this could at last stop.
As fate would have it, my wish came true, and without knowing me, Steve Kirsch gave me the opportunity to begin introducing that forgotten history to the world. This happened after he chose to publish an article I wrote illustrating how the trucker protests were identical to smallpox protests that had happened more than a century before and then for reasons I still do not understand, encouraged his readers to subscribe to me so I would start writing here. Note: At the time I chose the username “A Midwestern Doctor” (for the smallpox article), I did not put much thought into it as I was never expecting to use it again.
Over the years, I’ve noticed again and again that a vaccine disaster happens which injuries many in a very similar way, it gets swept under the rug (often by officials who are quite conflicted in their decision to do so), and then the same thing happens again a few decades later.
Given that we give dozens of vaccines to each member of society, this raises an obvious question—what is that doing to society?
The Forgotten Side of Medicine is a reader-supported publication. To receive new posts and support my work, consider becoming a free or paid subscriber. To see how others have benefitted from this newsletter, click here!
A Brief History of Vaccine Disasters
In 1798, the smallpox vaccine hit the market. Once it hit the market, it was observed to frequently cause smallpox outbreaks (rather than prevent them) and to cause a wide range of debilitating and complex injuries that many of the doctors had never seen before (and many of which I believe were examples of “blood stasis”). Curiously, rather than recognizing this was a mistake, most of the medical profession endorsed the smallpox vaccine, and governments around the world mandated it as cases kept on increasing, leading to a downward spiral that was eventually broken by mass public protest against those mandates. Having looked at it extensively, I am of the opinion the smallpox vaccine reshaped the trajectory of humanity’s health and was an inflection point in the era of chronic illness.
In the 1800s and early 1900s, a variety of early vaccines (e.g., rabies, typhoid, diphtheria, tuberculosis) and horse-generated antiserums (for most of the common infections at the time) entered the market. Since many of these vaccines were produced in small independent labs, there were a variety of quality control issues with these products, which frequently led to hot lots being released that severely injured or killing a group of people. Additionally, many of those vaccines had a high degree of toxicity. Because of this, a variety of new and severe medical conditions emerged, many of which were deemed to be due to brain inflammation (encephalitis) or brain damage (encephalopathy) and observed to occur in conjunction with cranial nerve damage. Most of these conditions (which I discussed in detail here) in turn mirrored the myriad of injuries we now too see from modern vaccinations. In addition to the injuries, two major issues stood out during this period:
•First, in addition to sometimes being directly contaminated with the disease causing organism (e.g., yellow fever or tuberculosis) and causing the illness, vaccines would often cause a temporary immune suppression which lead to disease outbreaks in those vaccinated (discussed here). However, each time this happened, rather than it being seen as a sign we needed to dial back vaccination, it was interpreted as not enough people being vaccinated and harsher and harsher vaccine mandates being instituted to enact that policy or new vaccines being created to address the existing damage of vaccination (e.g., the DPT vaccine frequently caused polio outbreaks).
•Second, public health officials and vaccine designers were well aware of the injuries vaccines were causing, but since no other treatments existed for the disease, regrettably deemed this to be a necessary sacrifice for the greater good and hence covered the injuries up so the public would continue to vaccinate. However, while I understand their perspective, it rested on a faulty premise—effective treatments did exist for the illnesses (e.g., in 1920 it was known IV hydrogen peroxide could treat severe infections and in 1928 it was known that ultraviolet blood irradiation could treat many otherwise incurable infections). Note: as you might have noticed, everything I just described also applies to the COVID-19 vaccines, hence illustrating how these dysfunctional cycles frequently perpetuate indefinitely.
In the 1940s-1950s, the original pertussis vaccine (DPT) entered the market. This vaccine excelled at causing brain inflammation and a variety of concerning differences were seen in the generations born after its mass adoption in America. Note: The rabies vaccine also excelled at causing encephalitis (around 1 in 750 injections, of which 20% were fatal), but it did not have as large an impact on society because far fewer people received it.
Between the 1950s to 1970s, numerous instances happened where a rushed and poorly produced experimental vaccine (e.g., polio or the swine flu) was brought to market to address a non-existent “emergency,” and the government chose to ignore warnings from its scientists that it was not safe to give to America. Since the press was honest at this time, they reported the disaster, it became a national scandal and the government provided compensation to the victims. Note: I compiled those media reports here, the last of which happened in 2002 with Bush’s smallpox vaccine.
In 1986, enough public awareness existed of the dangers of the DPT vaccine that lawsuits were regularly being filed for the brain damage and sudden infant deaths it caused (discussed here). This in turn led to the 1986 vaccine injury act being passed (discussed further here), an act that both shielded vaccine manufacturers from product liability and was intended to help parents of vaccine injured children (even though it didn’t due to selective enforcement of its provisions and the Supreme Court exempting manufacturers from injuries caused by defective vaccines). This act being passed led to an industry gold rush to bring experimental and liability free vaccines to the market, and before long the childhood vaccination schedule ballooned in parallel to chronic illnesses increasing as well.
Note: since this time other vaccines (e.g., RSV and annual COVID vaccinations) were also added to the childhood schedule (but fortunately MAHA managed to recently do the impossible and remove COVID from it).
In 1990, an experimental anthrax vaccine was deployed upon the military to prepare them for invading Iraq. While the war was non-eventful (Saddam did not use anthrax and it was likely the most one-sided conflict in history), the anthrax vaccine severely injured over 100,000 servicemen (leading to what was known as Gulf War Syndrome). Despite these issues, individuals within the Department of Defense who were committed to funding their bioweapons defense program mandated it—leading to severe injuries throughout the military and widespread rebellion against this edict.
After this, new biotechnologies began emerging which made it possible to genetically engineer a plethora of new vaccines that then began to flood the market as ACIP endorses virtually every vaccine given to them regardless of its merits (in fact, throughout their dozens of endorsements I could only identify one case where ACIP did not [boosters for teachers and healthcare workers], and in that instance the CDC simply overrode ACIP). In tandem, direct to consumer pharmaceutical advertising was legalized by a 1997 FDA decision, making it possible for the pharmaceutical industry to buy the mass media’s silence, and hence end all future coverage of vaccine injury.
In 2010, Merck convinced America’s women they were at a high risk of dying from cervical cancer (which in reality only kills about 1/38,000 American women each year) so that everyone would buy their highly lucrative vaccine (which was never proven to reduce cervical cancer deaths). This vaccine had an extraordinarily high rate of injuries (e.g., severe autoimmune disorders), but nonetheless, despite a deluge of complaints, the CDC and FDA did everything they could to protect it, and to this day it is still mandated for children.
In 2021, the COVID vaccine hit the market and caused an unprecedented amount of injury (e.g., many noticed healthy adults dying “suddenly” and large polls showed 34% of vaccine recipients reported minor side effects while 7% reported major ones severely impacting their quality of life). Fortunately or unfortunately, the rate of injuries from it was so high that unlike the past disasters, the mass media could no longer sweep it under the rug, which eventually culminated in MAHA ascending as a political force and RFK Jr. being put in charge of the agency which has orchestrated the vaccine disaster for decades.
In my eyes, one of the most important points to take from this history is that at the time each of these happened, the medical profession and public were struck by the explosion of these new diseases (and their immense social cost) but before long, became acclimated to them and forgot they had ever emerged in the first place.
The Harms of Vaccination
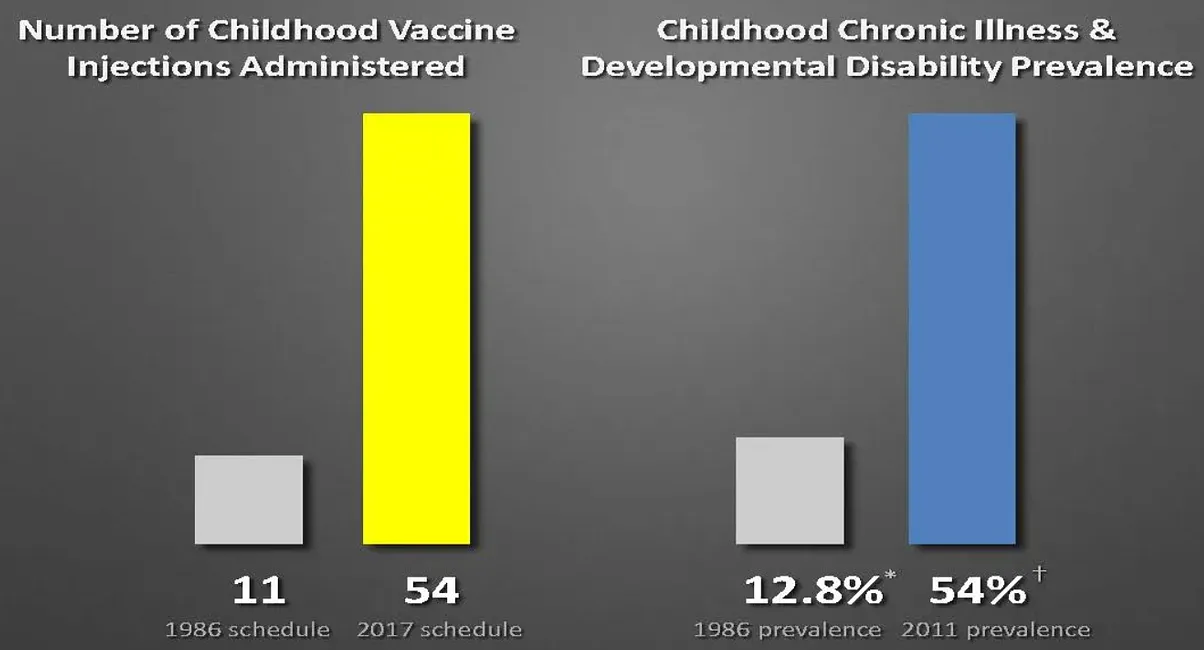
There is a large body of evidence suggesting vaccines are either solely responsible for, or one of the primary things responsible for the tsunami of chronic illness which has followed their ever-increasing adoption.
Unfortunately, while there is a great deal of evidence suggesting a problem exists, the effects of the vaccine schedule have never been formally studied and instead concerns are simply dismissed by a chorus that echoes “vaccines are safe and effective.”
This has naturally led to calls for the vaccines to be formally tested, but this is always rejected under the argument that vaccines are “so safe and effective” it would be ‘unethical’ to withhold them from trial participants who need to receive a placebo and expose them to the severe harm vaccine preventable diseases could cause (despite the fact very few of the vaccines on the market are for life-threatening diseases which still exist within the United States).
As such, to get around this embargo, a variety of independent studies (which all faced stiff opposition) have been completed that compared unvaccinated populations to vaccinated ones, all of which show profound harm results from vaccination. However, rather than be listened to, these studies are all dismissed because they “have no placebo” (despite placebo trials being impossible to conduct). Note: this highlights why the vaccine industry was so shaken up by RFK exposing this grift by now requiring proper placebo testing for new vaccines.
In lieu of placebo trials, we are instead told large databases can be relied upon to monitor for vaccine injuries. However, with the exception of VAERS (which is continually discredited by the media, government and medical profession), all of those databases are secret to the point the government has fought for years in court to protect their release (e.g., “to protect patient privacy”) and told us to trust their assessments of them.
Note: through a series of lawsuits, we were able to get access to some of the CDC’s V-Safe data on the COVID vaccines. In addition to this showing massive harm from the COVID vaccines, access to the raw data also showed that the Lancet summary of V-Safe’s data had distorted it to provide an illusion of safety not shown by the data.
Access to the CDC’s vaccine injury database (the VSD) hence has been a longstanding goal of the vaccine safety community and one of the things RFK pledged to do if he ever assumed office. Remarkably however, right before he got access to it “rouge” H.H.S. employees decided to delete it to prevent this from happening.
All of this hence suggests that either:
No evidence exists of the harms of vaccination and it has simply not been a priority to formally publish that data (which is odd given how much effort blocking all the lawsuits and petitions requesting it takes).
There is some evidence vaccines are harmful, and there are concerns this data could be misinterpreted to suggest vaccines are much more harmful than they are.
The existing evidence shows that vaccines are incredibly dangerous to the point it is an existential threat to the vaccine program and hence all measures possible have been taken to prevent it from being disclosed.
As you might guess, I believe the latter is the most probable, particularly since:
Numerous clinical trials of individual vaccines show that vaccines cause many of the same disorders that have risen in parallel with increased vaccination (e.g., the HPV vaccine caused at least 2.3% of trial participants to develop an autoimmune disorder. Note: there are numerous cases reports of children becoming permanently disabled after receiving a higher than normal number of vaccines simultaneously (e.g., at a visit where they also get caught up on missing doses), and conversely, many have observed spacing vaccines out rather than giving them all together lowers the likelihood of a severe reactions (e.g., autism) from vaccination.
Despite relentless attempts to keep them from emerging, there are numerous retrospective studies of large medical datasets which each show vaccination results in a significantly increased incidence of chronic disease results from vaccination. For example, a recent study of 99 million people showed the COVID vaccines were 2-7 times more likely than a typical vaccine to cause a variety of life-threatening illnesses and we now have large datasets linking to the COVID vaccines to many conditions like myocarditis, cognitive impairment, along with many autoimmune, musculoskeletal and psychiatric disorders.
Established mechanisms exist to explain how many different vaccines could all cause similar injuries to their recipients (each of which are discussed here).
I periodically learn of medical practices that have low rates of vaccination and also have much lower rates of chronic illness in their patients.
Many colleagues and I frequently observe what we believe to be the harms of vaccination in our patients.
Note: I personally know many trained observers who can have a high degree of accuracy in identifying unvaccinated children. The approaches they use are discussed at the end of this article.
Vaccine Injury Datasets
Despite the embargo on conducting or publishing studies demonstrating evidence of vaccine harm, a few still have been done. They are as follows:
Paul Thomas
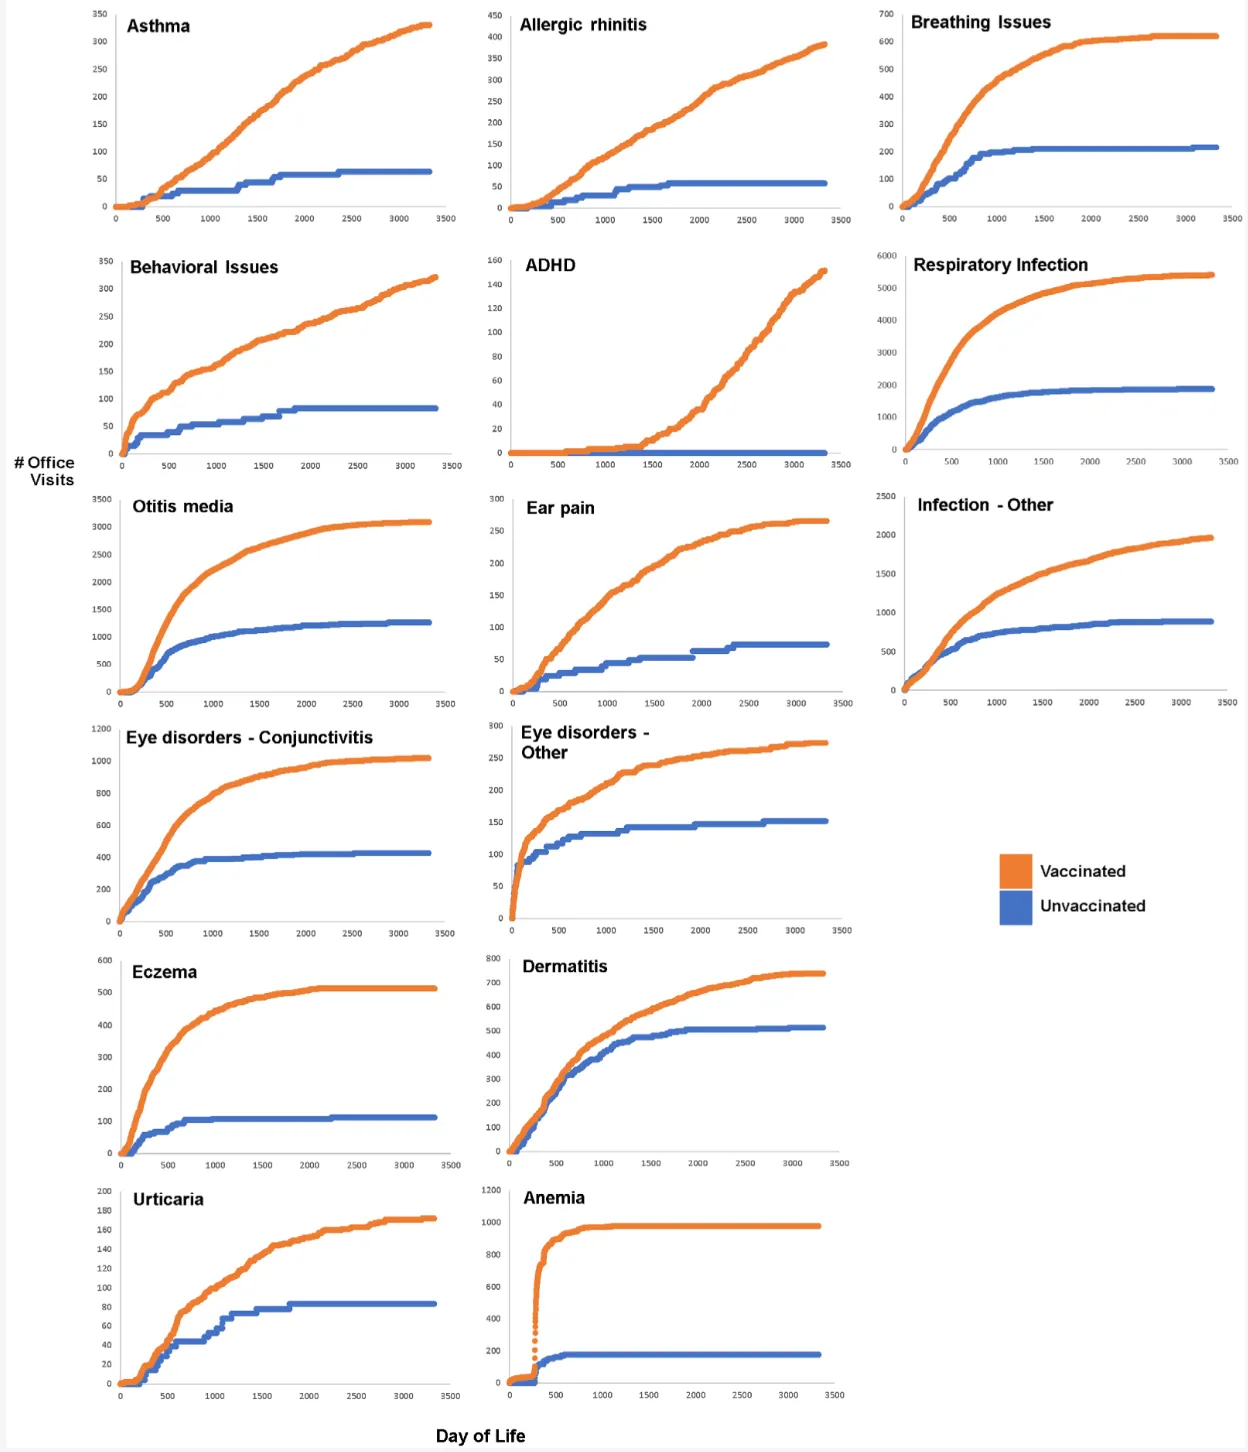
Paul Thomas MD, an Oregon pediatrician had a practice with a large number of unvaccinated or under-vaccinated children, and (like many of the other practices with similar patient populations) noticed that the unvaccinated children had dramatically better health. He thus decided to compare their medical records to those of variably vaccinated children and published the data in a study (which, as you are not supposed to violate that embargo, cost him his medical license and resulted in the study being retracted for spurious reasons).
Note: Paul Thomas (now retired and offering coaching services to parents) was also the author of The Vaccine Friendly Plan, an approach to vaccinating that encouraged spacing out vaccinations and resulted in a dramatically lower rate of vaccine injuries. Since his plan implied the current vaccination schedule promoted by the CDC was not safe, his plan was not popular with the medical authorities (which again illustrates the harm of the “safe and effective” dogma, as if dangers were to be acknowledged, far fewer people would be injured).
In his study, to compare the health of 2763 vaccinated children and the 561 unvaccinated children born into his practice, he plotted how many total visits each group had for a variety of issues as their age increased (e.g., how many visits for asthma in total had occurred in vaccinated children who were 1000 days old or younger) and then compared the two (with the unvaccinated group’s visits being equalized by multiplying them by 4.9 [2763/561]). This data in turn suggested vaccinations were the primary agent responsible for the epidemic of chronic diseases in our society.
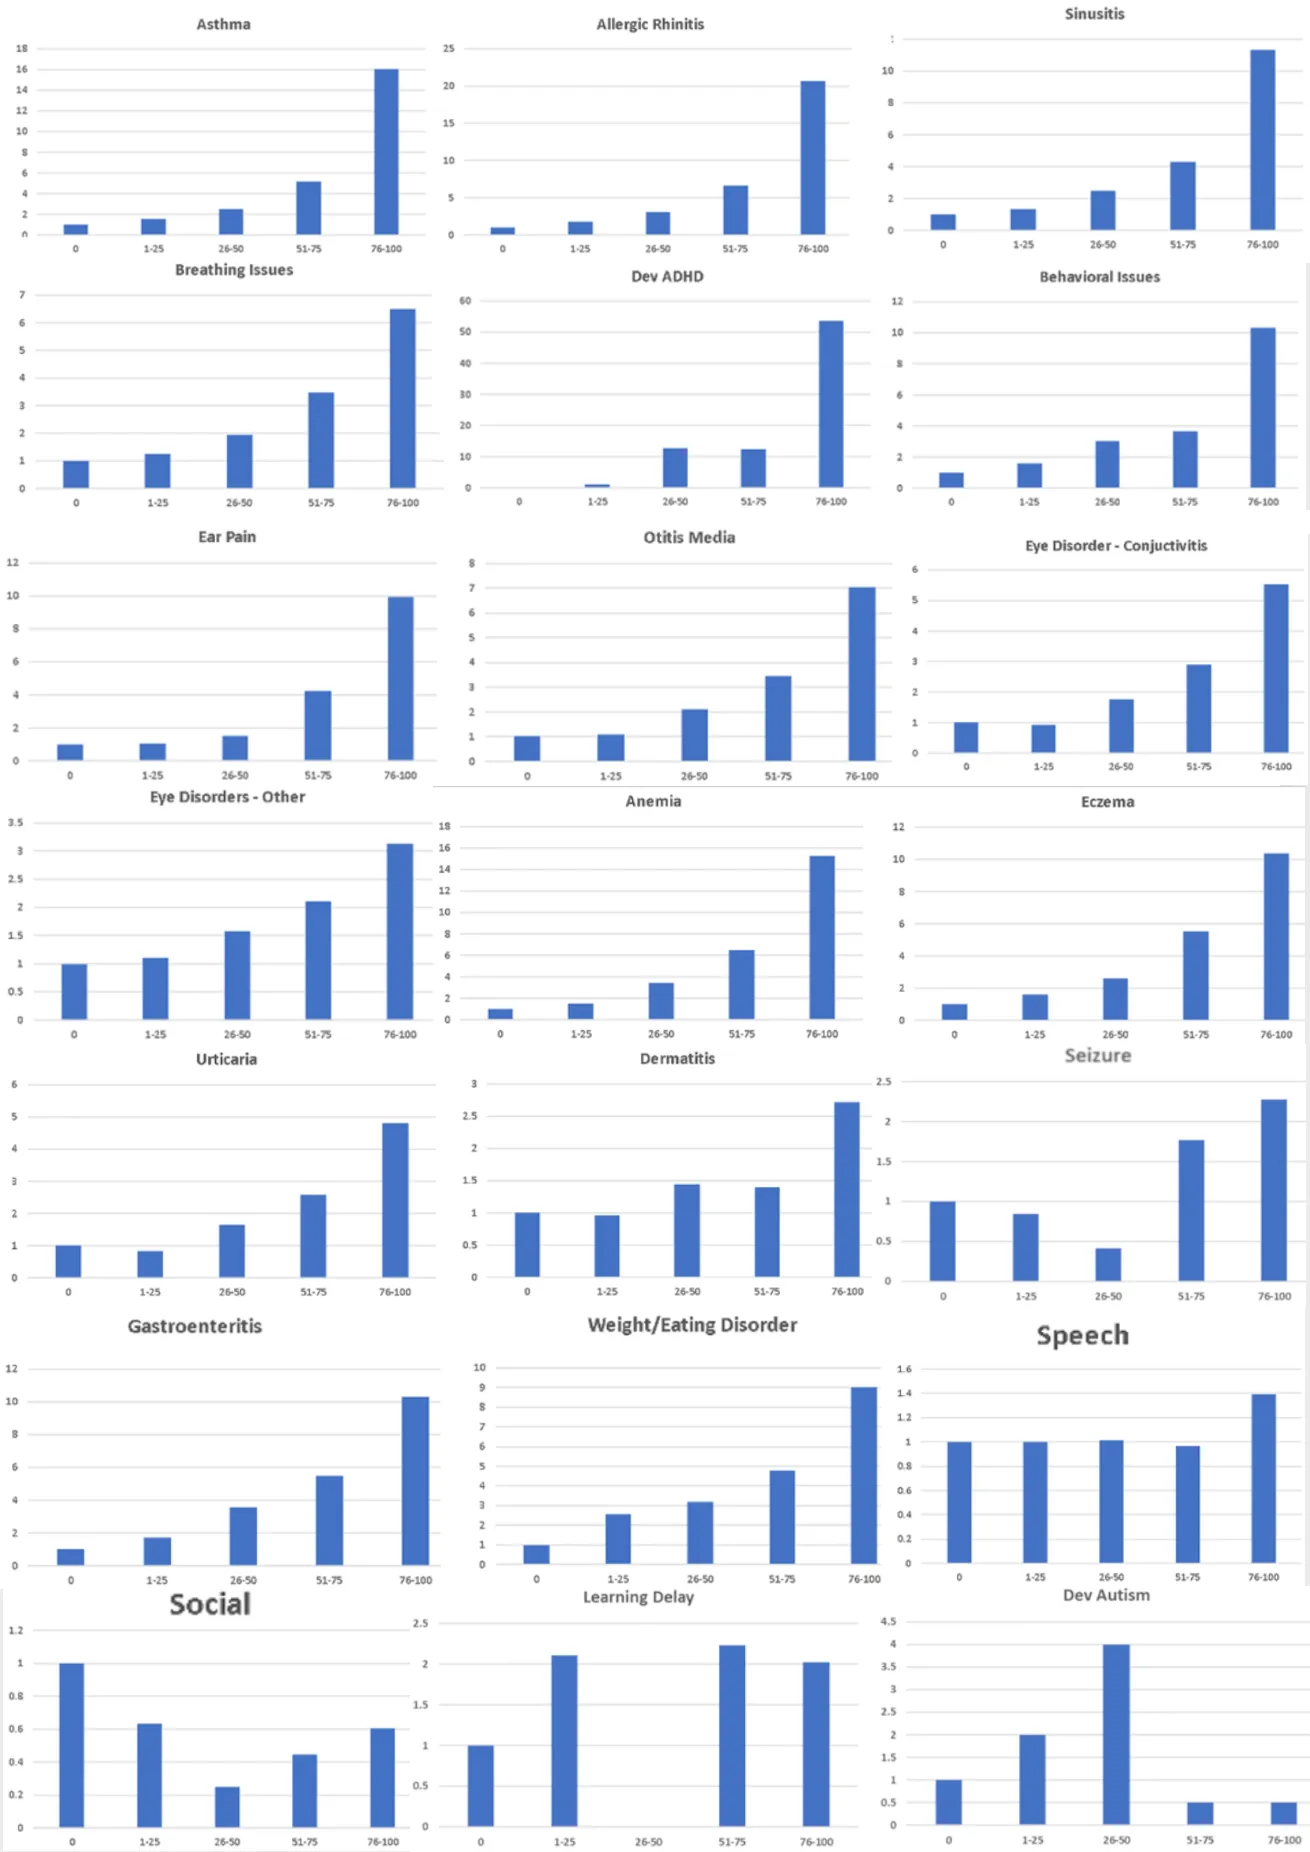
Likewise, when Thomas compared how likely a child was to come in for an office visit for a variety of health concerns, he found the greater the number of total vaccines a child received (which varied widely in his practice), the more likely they were to require an office visit for a variety of conditions.
Note: the full size version of this chart can be viewed here. In this chart, pay special attention to the fact these charts include ADHD (which was not found in any of the unvaccinated patients), behavioral issues, speech issues, social issues, learning delay and developmental autism.
Brian Hooker and Neil Miller
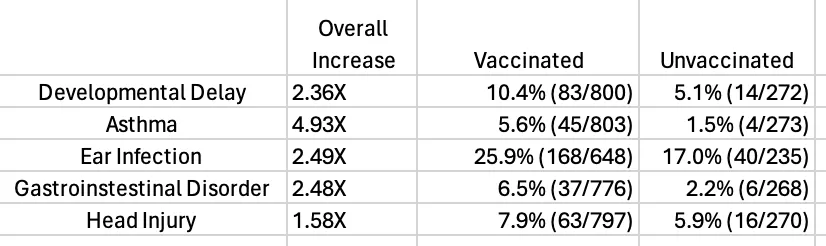
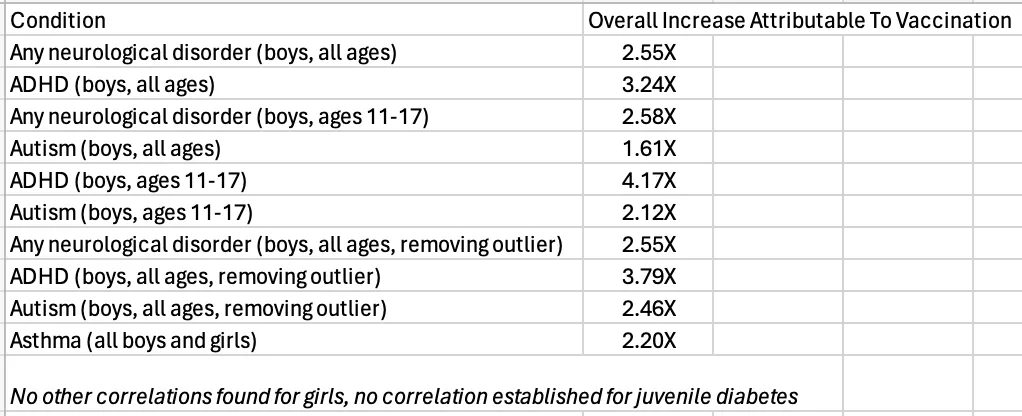
Hooker and Miller performed a similar study to Paul Thomas. However, in their study, they evaluated data from 3 different pediatric practices, and analyzed the 2,047 who had been born within the medical practice between November 2005 to June 2015 that had not received one of the selected diagnoses prior to their 1st birthday. They found:
Note: the above chart only compares the children within the sample who were at least 5 years old. When younger children were compared to each other, smaller increases were seen in the rates of each of these chronic diseases as there had been less time for the chronic effects of repeated vaccinations to manifest (which helps to explain why vaccines studies stop monitoring for side effects shortly after vaccination).
The stark differences in the rates of adverse injuries (and lack of chronic illness in groups like the Amish who do not vaccinate) have also inspired a variety of independent surveys to be commissioned which assessed if this link indeed exists. It should also be noted that there is a viable mechanism that ties almost every condition listed in this section to vaccination. Note: I reformatted most of the surveys that follow to make their data easier to see.
The 2007 Generation Rescue survey
In 2007, Generation Rescue (GR), an organization that is trying to alert Americans that vaccines cause autism, hired a third party polling firm (SurveyUSA) and paid them $200,000 to do a survey of 17,674 children (991 of whom were completely unvaccinated). It found:
The Homeschool Survey
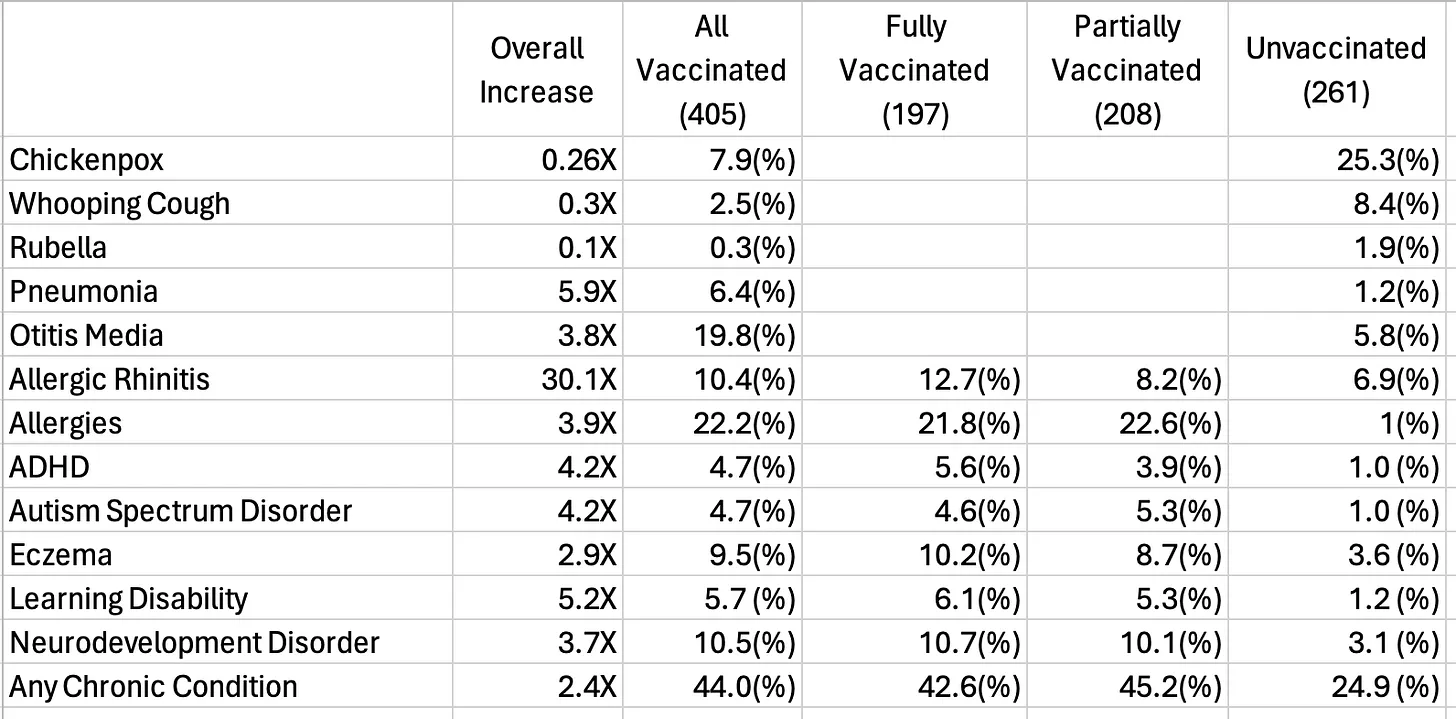
In 2017, a survey of mothers of homeschooled children from Florida, Louisiana, Mississippi and Oregon was carried out and then published. Since there are a significant number of unvaccinated children who homeschool, it was possible to compare 261 unvaccinated children to 405 fully or partially vaccinated children. Its results were as follows:
Note: since the three illnesses vaccination were supposed to prevent decreased (whereas the others increased), that data supports the validity of this survey.
The Control Group Survey
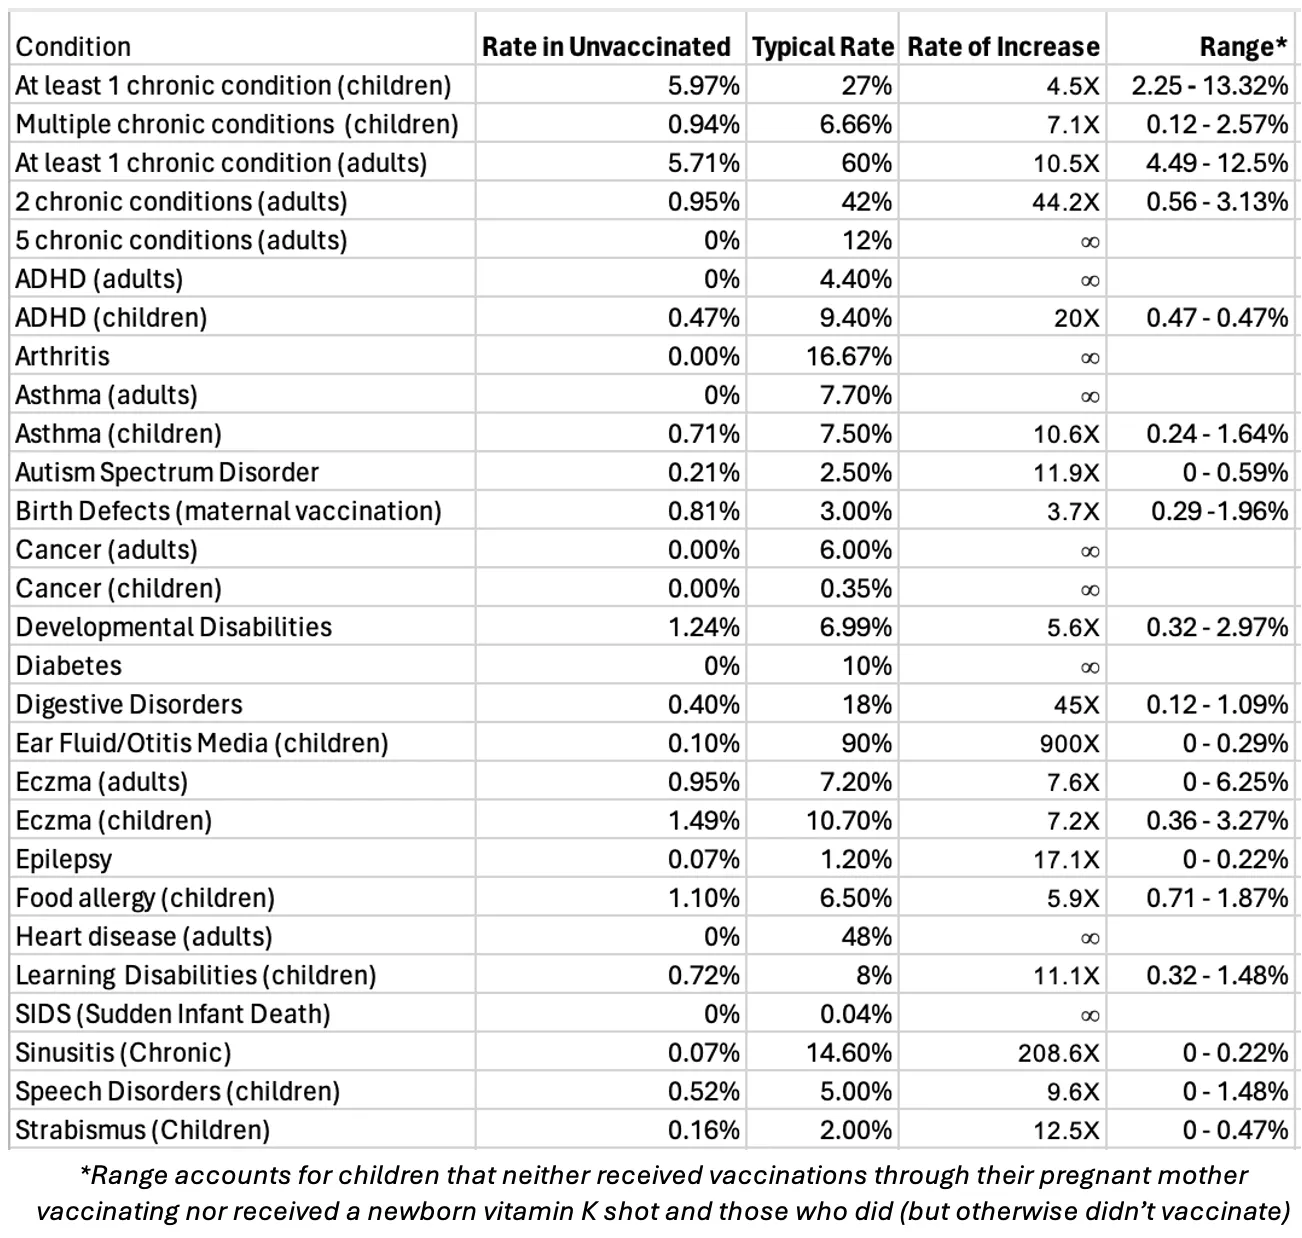
Between April 2019 to June 2020, the Control Group attempted to locate as many unvaccinated as possible to survey their health. Ultimately, they received 1544 completed surveys (1482 were from the US and represented 48 states). Once this data was obtained it was published in an easy to read 21 page set of charts that compared the rates of these events to their general occurrence in the population and a more detailed 85-page report. Like the previous groups, they found a massive increase in chronic illness following vaccination, and additionally, demonstrated that vaccinating while pregnant or a newborn receiving the vitamin K shot (about half of which contain aluminum) is not entirely safe.
Steve Kirsch
Many people in tech believe the solution to all of humanity’s problems is more data. This echoes the belief of the founder of evidence-based medicine (which has become the current dogma of modern medicine), who argued that having medical practice guided by the best available scientific evidence was essential as it would eliminate bad medical practices that had become entrenched medical dogmas and replace them with evidence-based approaches that saved lives.
While he was correct, like those in Silicon Valley, this approach was also incredibly naive as it failed to account for the obvious loophole—burying any data that provided inconvenient conclusions. As such, “the best available evidence” typically ends up being the best funded evidence, not the best evidence and at this point, trillions are spent each year to monopolize that evidence.
To illustrate: our electronic medical records which doctors are forced to spend a significant amount of each day entering data into collect an absolutely massive amount of medical data. Yet—despite countless pleas to, we almost never mine that data to determine what constitutes the best medical practice (e.g., which drug produces a better outcome for a condition or which pharmaceuticals are more likely to harm than help a patient).
This would be very easy to do, numerous people (including an acquaintance of mine) have tried to do this but got shut down (e.g., the government scrapped a system that in 2010, showed 2.6% of recipients of vaccines had an injury within 30 days of vaccination). I in turn, would argue that suggests the data in those records greatly threatens the pharmaceutical industry and hence cannot be disclosed.
Over the last few years, I’ve gotten to know Steve Kirsch and would argue the following traits hold true for him:
He has a deep desire to help people (e.g., he’s donated a lot of money to charity) and believes that better data and science are the keys to doing this.
He believes things should be fair and it really bothers him when people violate the responsibilities they are entrusted with (e.g., the CDC monitoring for vaccine safety).
When something bothers him, he often doesn’t let it go and can be relentless in trying to rectify it (which is demonstrated by how much time he has put into obtaining the minute details of the COVID-19 injury data).
He has no qualms about doing things you aren’t supposed to do or creating an uncomfortable situation to get something done he believes is important. This includes directly confronting people he thinks are being dishonest or incompetent and full of it.
Note: I am sure many of you know someone like this. Steve however is unique because I don’t know anyone else in this movement like that who has also been anywhere near as successful in the professional sphere as he has. I am hence incredibly grateful he decided to pick up the vaccine issue as we’d been waiting for decades for someone like him to do that (which is essentially why I’ve worked so hard to support him much in the same way we’ve helped Ron Johnson—the first US Senator in history to fight for vaccine safety).
Because of his personality, Steve in turn had a revelation—if no one will give us the data we need about the vaccines I should just obtain it myself. As such, beyond collecting every existing dataset demonstrating the harm of the vaccines (many of which I’ve reused here), he has also funded numerous professional surveys being conducted on the COVID vaccines (which all found between 8.6% to 16.4% of COVID vaccine recipients experienced significant harm from them, a rate similar to that of other independent surveys that were also conducted).
Additionally, he has also leveraged his large following to conduct numerous surveys on vaccine injury. While the initial ones were targeted at the COVID-19 vaccines, as he became aware of the scope of the problem we were facing, he also chose to do the same for the childhood vaccines.
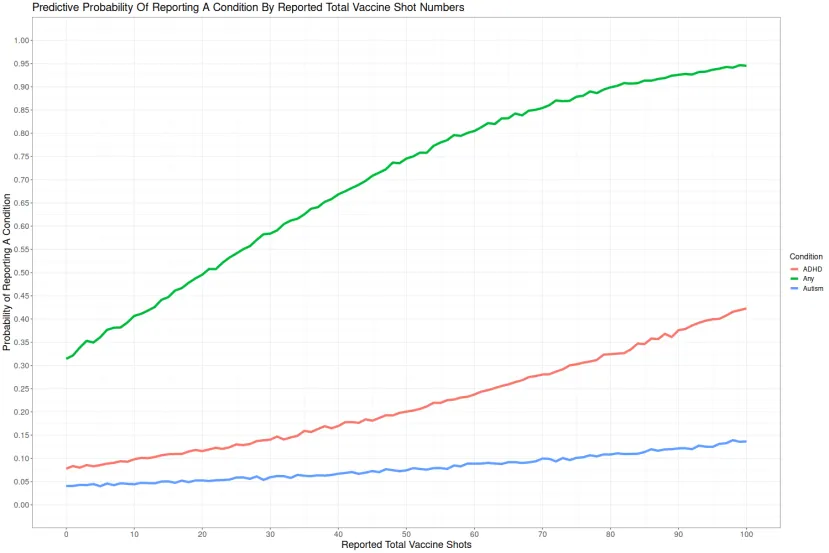
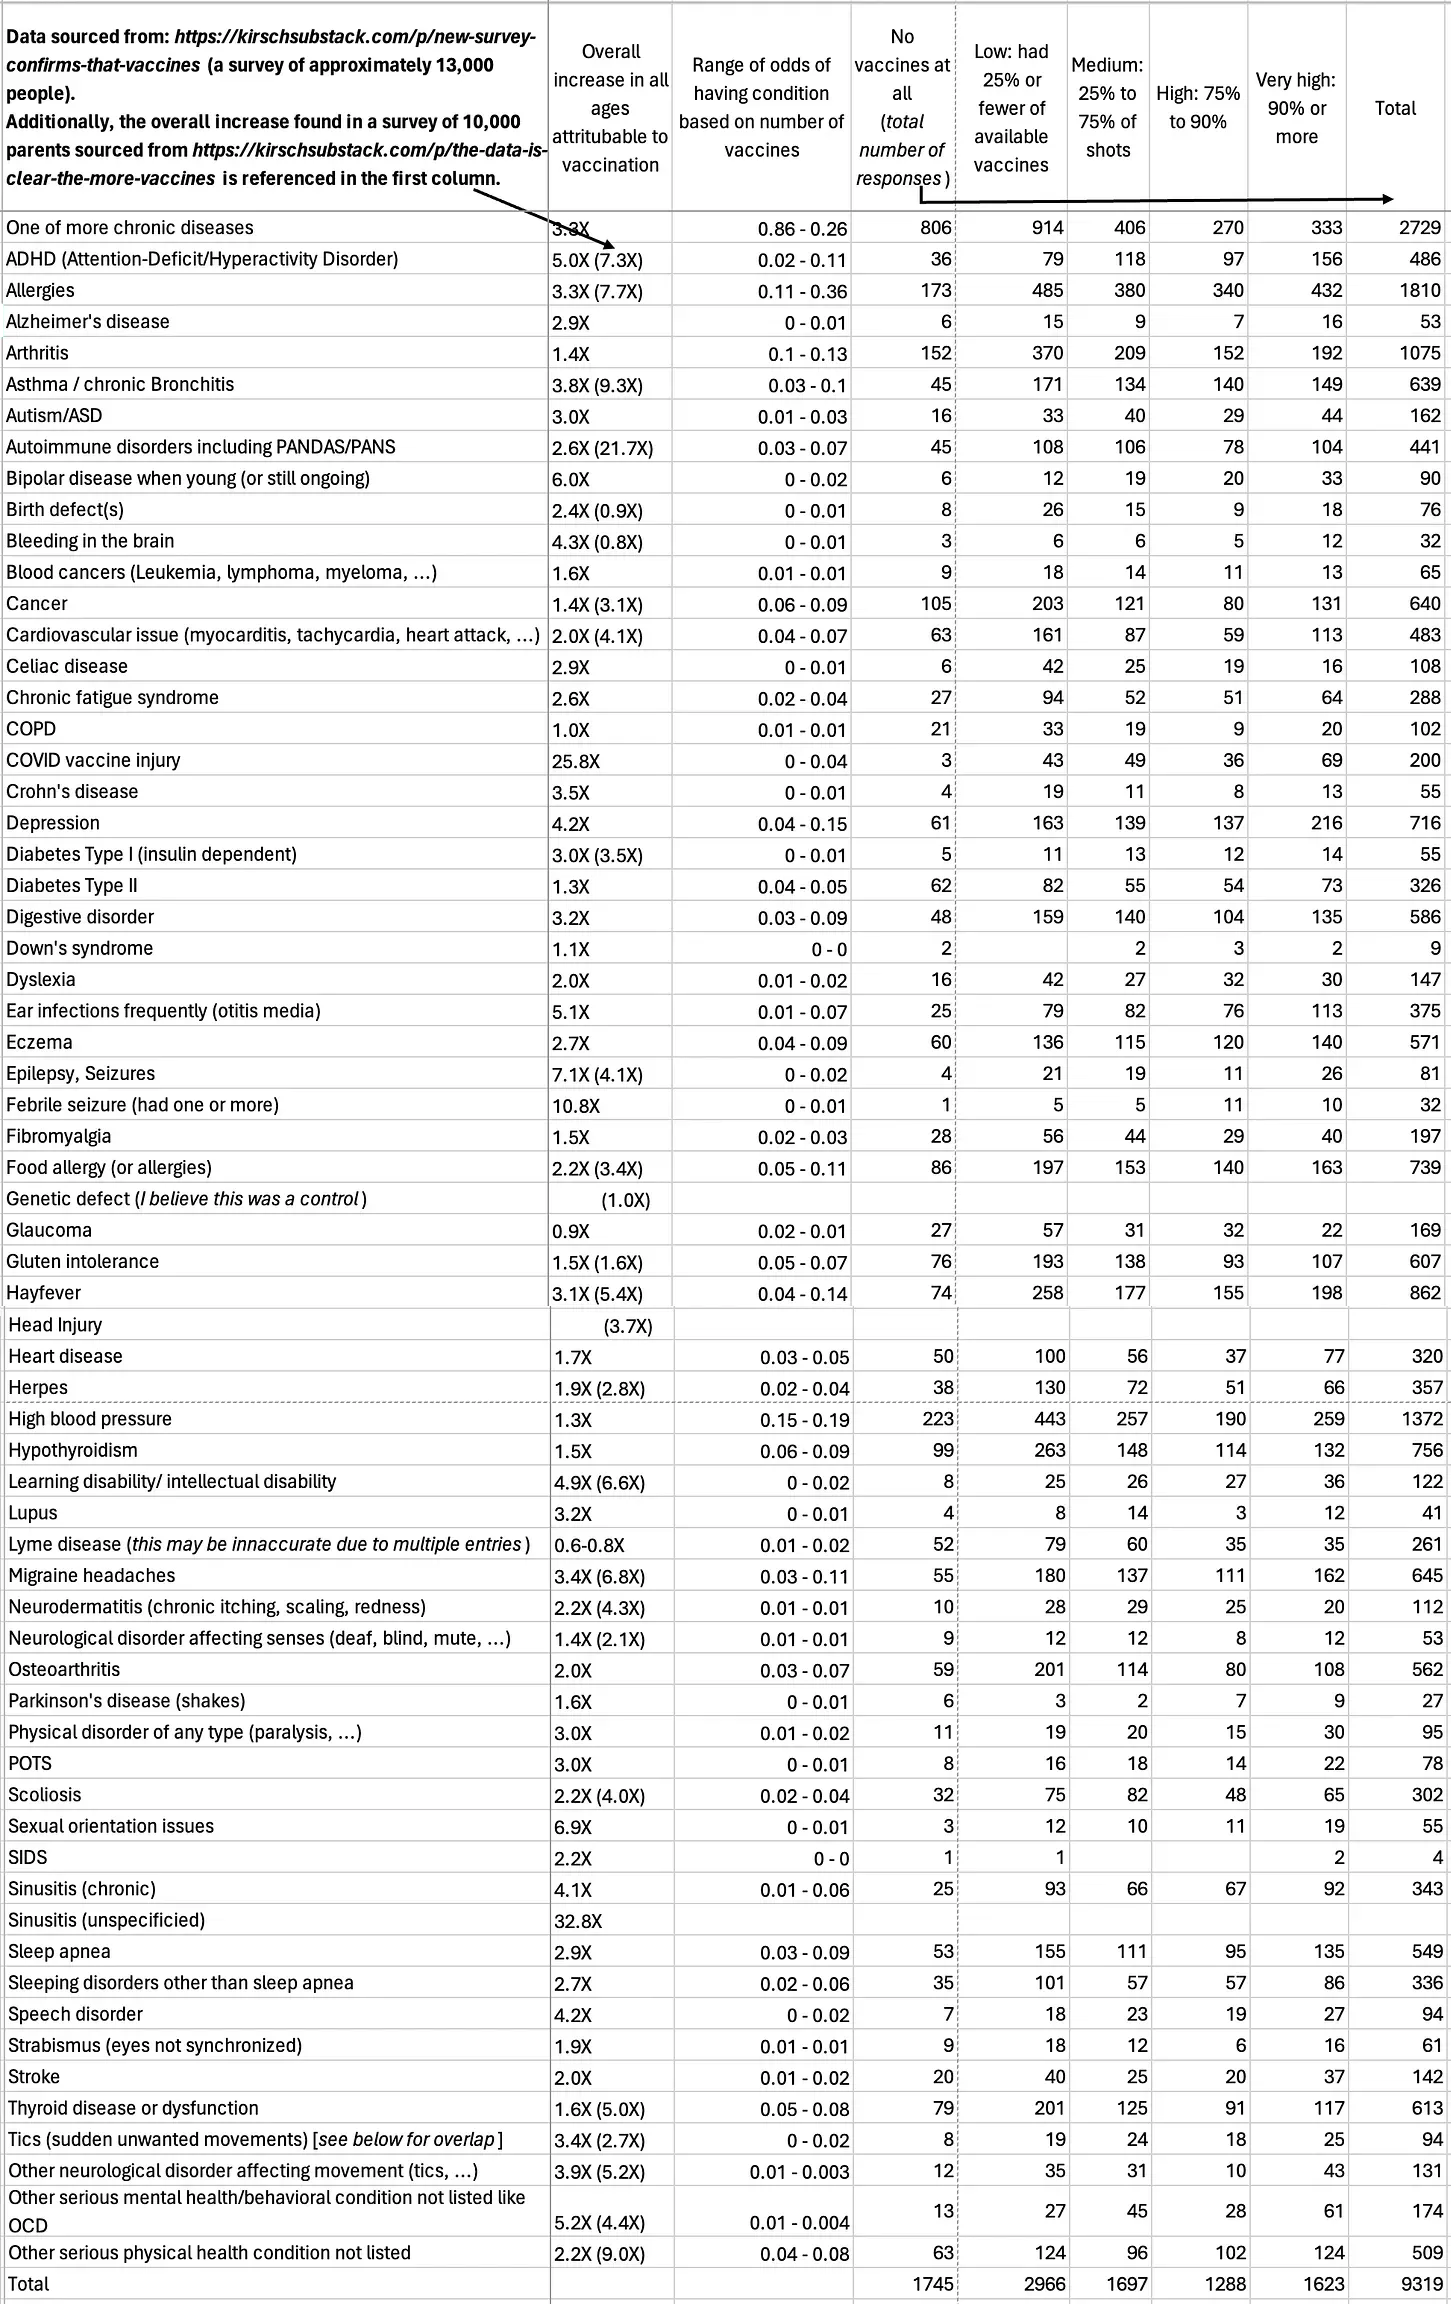
From this, he found similar results to the previously mentioned parties. For example in his first survey of ~10,000 people, he again demonstrated the dose-response relationship between vaccination and chronic illness:
Hopefully, this shocking data provides some context to why many are so ardently opposed to vaccination and why there is such a strong embargo on ever letting any of this data get out. Instead we’ve allowed an ever increasing number of vaccines to enter the market which in turn has led to us needing to spend trillions of dollars each year “treating” the complications of those vaccines.
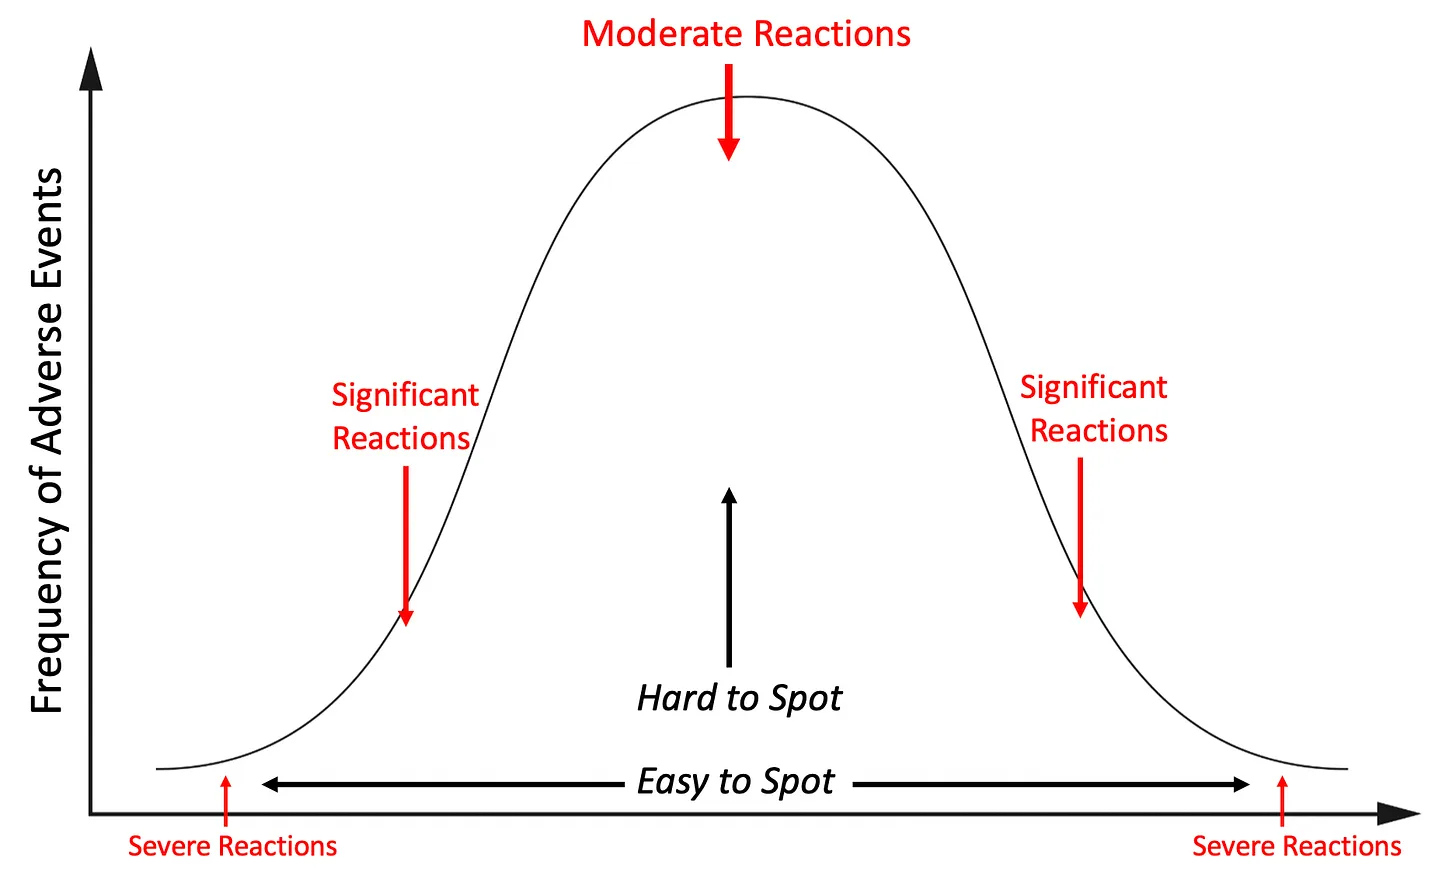
What I believe is the most important to understand about these statistics is that they only represent the tip of the iceberg, as the surveyors were only looking for the easy to observe conditions most obviously linked to vaccination (the “significant reactions”), much in the same way conventional vaccine studies only assess for a few “rare” conditions linked to vaccination. This, in turn, is reflective of a fundamental principle in toxicology—extreme reactions to a toxin (sudden death) are much rarer than minor ones.
In the next section, we will consider the middle of this bell curve—the moderate reactions that are rarely linked to vaccination.
A remarkable feature of encephalitis—whether of epidemic origin or due to an infectious disease, traumatic injury, or vaccination —is the multifarious diversity of its physical, neurologic, mental, and emotional symptom since any portion of the nervous system may be affected.
If autism is a manifestation of vaccine-induced encephalitis, the implications are very disturbing. The symptoms manifested with pathological intensity in a small group will of necessity appear in milder form in a much larger proportion of the population.
Note: in this article, I reviewed the evidence showing autism is a form of encephalitis with many accompanying neurological injuries. Remarkably, while vaccines “don’t cause autism” one of the only injuries acknowledged by the 1986 Vaccine act was MMR (the vaccine linked to autism) causing encephalitis.
Minimal Brain Damage
The 1985 Book, DPT: A Shot in the Dark is arguably the most influential book ever written for the vaccine safety movement (e.g., it was responsible for rallying Congress to do something about the epidemic of sudden deaths and brain damage being created by the original DPT vaccine). What is less known is that in 1990, one of its authors, Harris Coulter, then published a book that alleged that vaccines were responsible for the widespread increase in crime sweeping the nation.
Note: I consider this book to be one of the most eye opening and disturbing books I’ve ever read (e.g., as a child, I saw what it described happen in people I knew quite well). Since some of its content is quite graphic (and because the book is hard to find) I am including a copy of it at the end of this article for those who would like to read it (which I would strongly encourage you to do). As there are too many references to list here, to locate them, please consult the book’s bibliography.
The author (who as his obituary shows was a lovely human being and gifted researcher) in this book argued that:Many of the same complications seen after encephalitis (e.g., cranial nerve issues, seizures, paralysis, or permanent intellectual disability) also occurred after vaccination. He proved this by compiling extensive literature reports of each, which showed they overlapped and in many cases, showed the vaccine injuries were assessed to be “encephalitis” (which I likewise did so here).
This included over 400 references from the scientific literature (located prior to the internet existing), another 400-500 he reviewed but did not cite (which arrived at similar conclusions), interviews of approximately 150 families, where in many cases, he was able to show these childhood brain injuries progressed into a life of crime. Note: I believe “encephalitis” (or encephalopathy) is a combination of brain inflammation (autoimmunity is a common complication of vaccination), brain swelling, microstrokes throughout the brain (discussed further here) and an unresolved cell danger response (discussed further here). Additionally, if you read the medical literature from roughly a century ago (summarized here), its clear many doctors believed vaccines caused encephalitis based on the symptoms they observed (and in many cases the autopsies they later performed).
If the DPT vaccine can cause “acute encephalopathy” in a small number of cases (which was acknowledged by the Institute of Medicine in 1991), it must cause a milder condition in a larger number of cases as the reactions of a group of individuals to a given biological stress are never “all or nothing,” but fall along a continuum. Note: Coulter cited many different authors who observed a bell curve in post-encephalitis complications.
That it was very easy to miss that this was happening. For example, Coulter cited two different authorities on this subject who said:
Actually there is no correlation between the severity of the infectious disease and the cerebral involvement. In many cases with only a mild illness severe postencephalitic complications may arise months or even years later.
Even apparently uncomplicated attacks of infectious diseases of childhood (e.g., pertussis) may result in brain damage, which may then be the primary cause of subsequent behavior disorders.
Researchers in the epidemiology of vaccine damage invariably assume that long-term sequelae will not occur in the absence of a severe acute reaction. This assumption was accepted by us in writing DPT: A Shot in the Dark. Thus it was puzzling to find that about half of the new families interviewed for the present investigation could not remember any marked vaccine reaction, even though the child began to develop symptoms of autism or other severe neurology shortly after one of the shots.
Many of complications of encephalitis (e.g., a myriad of learning disabilities or psychiatric and neurologic illnesses such as autism) became dramatically more common in our society starting in the 1940s and 1950s, a rise which paralleled increased vaccinations and increased vaccine injuries (predominantly as a result of DPT—the vaccine most associated with brain injury) and could be directly observed rippling through society as these children grew up. For example:
Rimland and Larson have called attention to “the striking, almost mirror-image correlation, starting about 1963, between the curves showing the decline in SAT scores and the upsurge in violent crime [which was often psychotic in nature],” suggesting “the existence of one or more common causal factors.”
The contrast between then and now was emphasized in a 1987 report on school discipline by the New Jersey Human Rights Commissioner. In the 1940s the most frequent school problems were: talking, chewing gum, making noise, running in the halls, getting out of turn in line, wearing improper clothing, and not putting paper in wastebaskets. In the 1980s they were: drug and alcohol abuse, rape, robbery, assault, burglary, arson, bombings, murder, absenteeism, vandalism, extortion, gang warfare, abortion, and venereal disease.
The murder rate doubled between 1960 and 1980, from four to eight per 100,000 inhabitants, for a total of more than 20,000 in 1987, giving the United States the highest incidence of homicide of any industrialized country. The largest increase occurred between 1960 and 1970.
A 1987 Washington Post-ABC News poll made a curious discovery—that sixteen percent of Americans under thirty are left- handed or ambidextrous [this is a common consequence of encephalitis], as against only twelve percent of those over sixty. Another recent survey found an even greater disparity: thirteen percent of twenty-year olds were lefties, compared to five percent of persons in their fifties.
Autism (a condition which follows vaccination and first emerged after DPT entered the market), has a strong association with many of the consequences of encephalitis (e.g., cognitive disability and cranial nerve paralysis).
That sociopathic behavior being observed to cluster in families mirrors the observation sensitivity to vaccine injuries also clusters in families. Likewise, Coulter suggested the increased sensitivity African Americans have to vaccine injuries (best shown through the CDC’s infamous decision to bury data that showed vaccines caused black boys to develop autism) might explain the social patterns seen in those demographics. Note: in a recent article, I discussed how some patients (e.g., those with hypermobility) are also much more sensitive to vaccine injuries.
That a variety of conditions had been created by the American Psychiatric Association which spanned the range from how minor to severe brain damage manifested itself in behavioral disorders (e.g., minimal brain damage, oppositional defiance disorder, conduct disorder, sociopathy). Coulter emphasized that as the DPT encephalitis condition exploded across America, the psychiatric profession tried again and again to gaslight the population by blaming it on unresolved psychological conflicts or poor upbringings rather than providing treatments holistic doctors had consistently found could help these conditions. As far as I can tell, this psychological gaslighting continued until the newer psychiatric medications (e.g., the disastrous antidepressants) entered the market, at which point psychiatric pivoted to mass-prescribing these lucrative products to the post-encephalitic patients. Note: this is a pattern that has persisted ever since Freud’s original cases over a century ago which falsely attributed symptoms of mercury poisoning to unresolved sexual issues.
In the 1950s, a condition termed “minimal brain damage” [MBD] was coined (with the defining characteristic of it being hyperactivity), which before long became “perhaps the most common, and certainly one of the most time-consuming problems in current pediatric practice”. The symptoms of MBD (as defined by America’s Public Health Service and the American Psychiatric Association) have a significant overlap with what was seen after encephalitis, DPT injuries, and what was associated with autism.
A British physician in 1928 noted that “changes in morals and character” in patients who have had encephalitis reveal a “curious uniformity.”‘ This same “curious uniformity” stamps the autistic, the minimally brain damaged, and the sociopath.
This encephalitis may produce an intellectual, tormented, and cruel monster out of a gentle girl or boy.” “A child of previously responsible character may be so transformed as to seem a different person…cruel, destructive, abusive, indecent.
Note: as a point of clarification, autistic children typically do not demonstrate cruel or sadistic behaviors (as that is only one possible outcome of brain damage). However, they do share many of the other traits found in post-encephalitic individuals.
There was a wide range of consequences of encephalitis. Many of these were subtle and insidiously altered the child’s personality, commonly making them hyperactive, hypersexual less empathetic, and generally uncomfortable with their environment. Many of these traits in turn were also seen in violent criminals and disruptive children (who frequently then went on to become violent criminals).
Coulter then collected numerous case histories of violent and sociopathic criminals demonstrating that they displayed many of the exact same signs (e.g., cranial nerve issues) seen in victims of encephalitis (be it from vaccination or a natural infection). This included detailed reviews of infamous criminals who precisely fit the post-encephalitic pattern such as Ted Bundy.
Coulter also provided numerous statistics and studies which showed violent criminals had dramatically higher rates of brain damage and neurologic dysfunction. Many of the studies he cited (e.g., one of 321 excessively violent individuals showed 90-100% had demonstrable brain dysfunction) found these defects occurred at 5-10 times the rates seen in the general population).Note: the associations shown in the papers Coulter compiled are also supported by modern research and hence are generally accepted. Additionally, newer research made possible by functional MRIs also show that violent or sociopathic criminals often have significant brain damage and lack the normal functions (e.g., empathy) other humans have. Much of this is shown in this audiobook and the research papers its author published.
Coulter cited numerous statistics showing a small minority of the population committed a majority of the violent crimes that occurred and evidence showing the crimes in the post DPT era were often much more brutal and sociopathic.
The traits commonly associated with MBD in turn were as follows: Note: these were also frequently observed to be consequences of encephalitis and often clustered together. Additionally, quite a few of these are now known to occur more frequently in violent criminals.
Hyperactivity (this was by far the most commonly associated trait with MBD). Note: there is a well-known association between hyperactivity and stimulant drug use or violent crime. Many authors (e.g., psychiatrist Gabor Maté) in turn have argued many people become drug addicts because they have untreated ADD (which we typically treat with pharmaceutical amphetamines—which unfortunately, like the SSRI antidepressants, can cause violent psychosis).
Frequent drug and alcohol use.
Hypersexuality. Often this sexuality was detached from having any type of connection to the other person and sometimes gave rise to a variety of unusual sexual fetishes or preferences. Note: this goes hand in hand with the emotional blunting frequently observed after encephalitis. Additionally, one of the most common types of dementia (which results from poor blood flow to the brain) is characterized by hypersexual behavior.
Feeling overwhelmed by and not in control of their environment.
Having difficulty organizing their thoughts or remembering their past experience. Note: this includes a flattening of one’s affect when remembering their questionable conduct from the past, an inability to empathize with those who were affected by it and in many of the case histories Coulter compiled, a complete amnesia of it.
A very short attention span (and paradoxically in a few cases, instead an obsessive and greatly excessive attention span).
Being impulsive and easily triggered into having violent outbursts (from both external stressors and internal ones such as a severe headache).
Headaches (which sometimes necessitated banging their head against a wall).
A high incidence of seizure disorders: epilepsy, tics, tremors, choreiform (twisting) movements, facial grimaces, infantile spasms, and others. There were also frequently overt signs (e.g., EEG abnormalities) and subtle signs (e.g., poor coordination) of these disorders.
While some children with MBD had above average intelligence, on average their IQ was below average.
Bed-wetting in childhood, typically occurring in conjunction with a sleep disorder (that often had features such as teeth-grinding, night sweats, nightmares, and night terrors). Sometimes this is also accompanied by loss of bowel control (e.g., ectopresis).
Poor visual-motor coordination, clumsiness and a lack of grace to their movement (e.g., “impaired hopping ability, and a tendency to walk on the toes”).
Decreased sensation to external painful stimuli.
Left-handedness or ambidexterity. Note: I know numerous people with DPT injuries this happened to.
Various processing disorders. These include dyslexia (difficulty reading), dysgraphia (difficulty writing), dyscalcula (difficulty with numbers), impaired speech (e.g., stuttering or stammering), paucity of speech or mutism, hearing disorders (e.g., audiomotor incoordination, auditory imperceptions or deficits, developmental receptive language disorder, high-frequency hearing loss, or hypersensitivity to sound). Note: the perceptual disturbances often were accompanied with a difficulty telling left from right or up from down.
Excessive sleepiness and a wide range of sleep disturbances (including new sleep disorders the medical community had not previously witnessed such as “delayed sleep phase syndrome,” a condition where one cannot fall asleep until 3 or 4 in the morning).
Frequent food allergies (along with conduct worsening when those foods were consumed). Note: other neurological diseases (e.g., schizophrenia and autism) have also been observed to improve after allergens such as gluten are completely eliminated from the diet.
Appetitive disturbances (e.g., anorexia or bulimia). It was noted that this complication of encephalitis far more frequently affected females, whereas hyperactivity more frequently affected males.
A strong desire to seek out music due to the rhythmicity and stability it provides.
Being highly disruptive and violent from a very young age.
Note: in the second half of this series (which can be read here), I discuss the changes in personality which specifically affect human relationships (e.g., the ability to emotionally connect with one’s partner or one’s gender identity) as there seems to be a fairly profound effect here that has real life data to substantiate it.
A Vaccinated Society
Assuming Coulter’s thesis is correct, the implications are sobering, and in turn, many readers here (who recognized witnessing what I described unfold in their own lives) felt the same way.
As so much could be said about this subject, I will only share a few of my most pertinent thoughts.
Like many of you, I often encounter people who me think “Why do you have to be so difficult?” Becoming able to recognize how vaccine encephalitis manifests has allowed me to switch from being frustrated by their behavior to developing a great deal of compassion for them. Likewise, it’s also made it much easier for me to understand how to effectively interact with them because I can recognize how their brains are misfiring and bypass those issues.
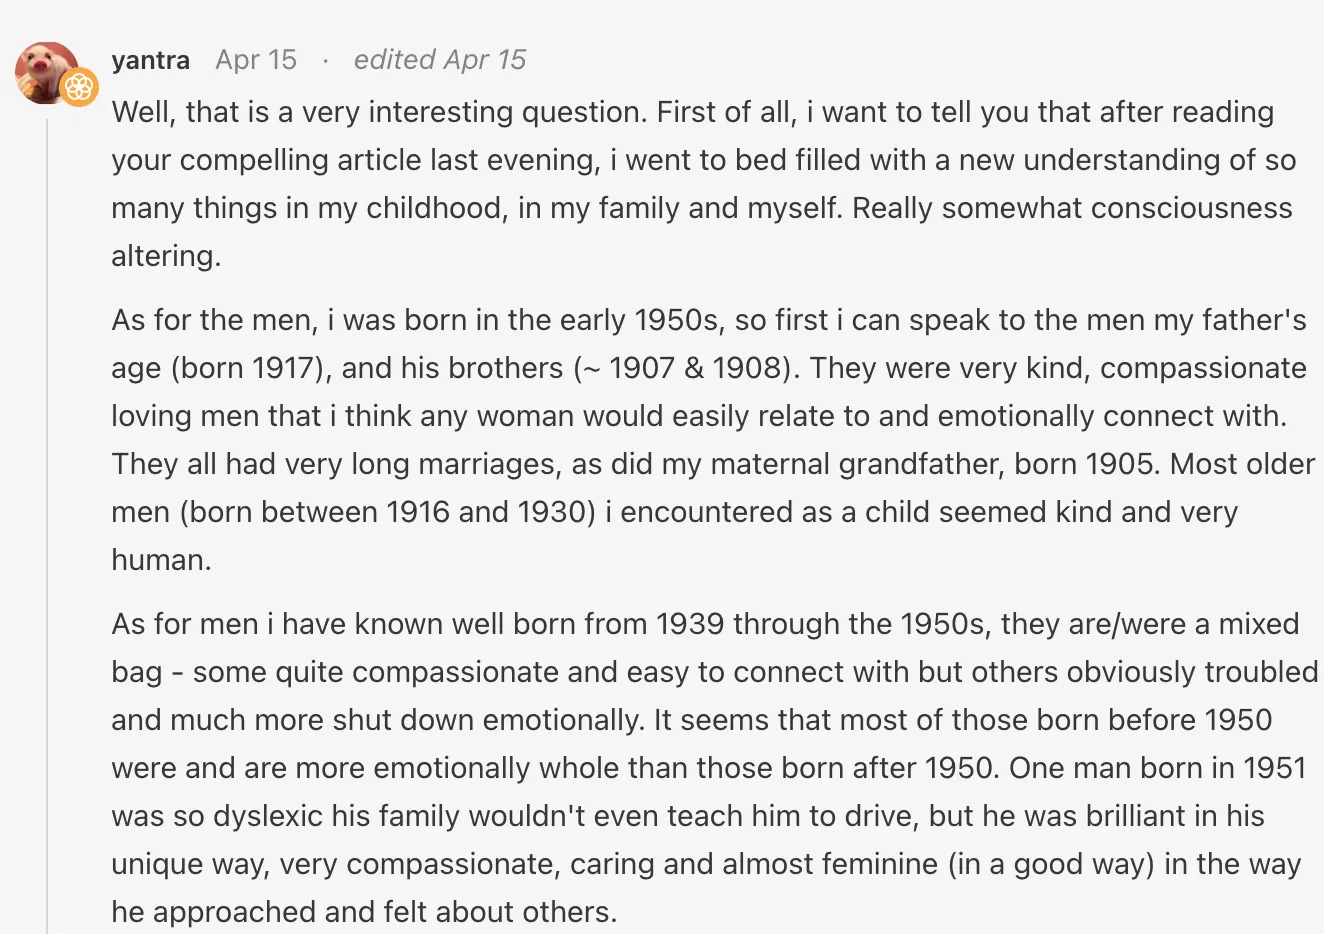
Many of the cognitive changes described in post-encephalitic patients perfectly mirror the common frustrations women have with men who cannot emotionally connect to them. This in turn has made me realize the vaccine program has likely profoundly altered the dating dynamics of the country, and from the queries I’ve made so far, my older readers who witnessed this shift occur agree it is likely an issue. For example:
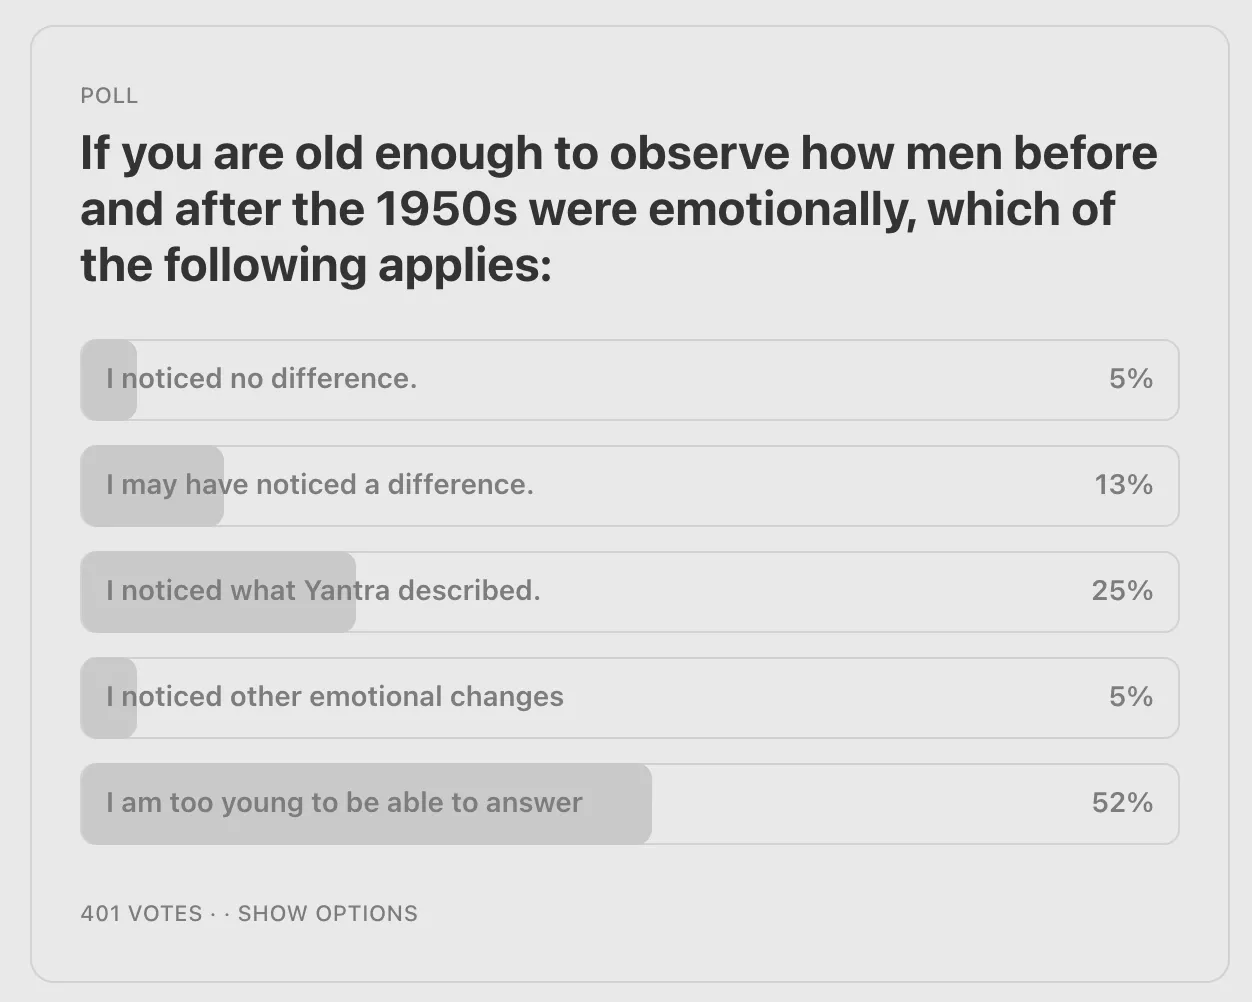
I then conducted a poll (to a readership which was much smaller at the time) that found:
I believe the gravest violation of medical ethics is if the pharmaceutical harms those who never consented to taking it. This is why I have put such a heavy focus on both the COVID-19 vaccine shedding and the frequent tendency of SSRI antidepressants to cause episodes of mass violence (e.g., school shootings).
This whole concept really turns both the liberal and conservative notions of what should happen with criminal justice upside down.
There has been a longstanding observation that the quality of American education has greatly declined (e.g., that what used to be taught in 8th grade was more difficult than what is now taught in college). I long thought this was due to education being massively mismanaged as it shifted to a profit focused (student retention) based model, but after I learned of Coulter’s hypothesis, I realized that it could also instead be a symptom of the societal wide decline in cognitive function being created by mass vaccination and schools having to accommodate it. This may also be intentional, as too many intelligent and mentally healthy people would threaten any oppressive power structure, and in turn mirrors what a doctor who was mentored by Robert S. Mendelsohn M.D. (a renowned pediatrician and one of the most impactful dissidents against the medical cartel) shared with me:
Mendelsohn told me that during his appointment as Medical Director of Project Head Start’s Medical Consultation Service in 1968, he was horrified by the discussions held privately in the White House with his medical colleagues. They were openly discussing how they could control the population of the poor by promoting infant formula, vaccinations, sadistic hospital birthing practices, deficient government schools, and neighborhood abortion clinics. This was just too much of an assault on his strong Jewish faith and his Hippocratic oath.
There is presently no incentive to stop this as so much money can be made selling treatments for these diseases (which are often very harmful), while if the mistake is ever admitted, far too many people have too much to lose. This in turn is why we keep on having worse and worse vaccine tragedies inflicted upon the world.
All of the data here shows why ACIP has not only a moral obligation but also a societal obligation to consider if the vaccines they approve are beneficial and necessary enough to outweigh the real harm each one can cause, particularly as more and more of them are given in succession. Put differently, I have full confidence that if all vaccines were banned, while some vaccine preventable illnesses would increase, the overall health and rate of illness in the country would dramatically decrease. For this reason, if mass vaccination continues it must be shifted only to the illnesses where the best argument exists for it (which I reviewed here) rather than ones where the harms of a (lucrative) vaccine greatly outweigh any possible benefits it can offer.
Note: while this position is controversial, I support providing some type of amnesty for the vaccine cartel, as I believe that is the only thing short of a revolution which would make them be willing to stop protecting the vaccine racket, since without it, it is quite literally a life or death battle for them to prove vaccines are “safe and effective.”
Subtle Signs of Vaccine Injury
When I first entered the medical field, a variety of holistic doctors (and other healers) told me they could typically tell if a child had been vaccinated. While I believe this is often possible to do, it requires utilizing a variety of more subtle signs most people would not agree with (excluding say the parents who noticed “something” changed in their child after vaccination).
Note: once you start becoming able to see how vaccine injuries are and how shocked or traumatized many infants look, it gets really depressing (whereas in contrast people are often drawn to unvaccinated babies and comment on how vibrant they are).
In turn, many have asked me what the signs of vaccine injury are. The challenge with this topic is that subtle injuries are dramatically more common than severe injuries (as reactions to toxins tend to follow a bell curve, with the most severe reactions being the rarest). Thus, the more subtle signs are harder to recognize (or prove resulted from vaccination) but simultaneously are by far the most common.
Some of the most common signs we use are:
A new condition developing shortly after vaccination that is known to be linked to vaccination (e.g., those listed in the above surveys such as seizures or autism). Often, there is a fairly consistent pattern in how these injuries form (e.g., they are preceded by severe fevers and crying that immediately follow the vaccination).
Overt changes in the cranial nerves (e.g., the eyes no longer track smoothly, or the facial muscles become asymmetrical). Note: here I explain how vaccine induced microstrokes can commonly cause this to happen.
A subtle change in function to any of the cranial nerves (many of which are detailed in the copy of Coulter’s book included below and in Wilson’s earlier compilation of our first century of forgotten vaccine disasters). Note: if you train yourself to spot these, they become more and more obvious as you become able to notice when something facilitated by a neurological process seems to glitch or misfire (e.g., the eyes lose their smoothness and jump as they move to either side).
Overt (rarer) or subtle (more common) cognitive and neurological changes which can be indicative of brain inflammation or brain damage. Like the cranial nerve changes, they are also discussed in Wilson and Coulter’s book (included below).
In addition to these changes, they are some more subtle “spiritual” changes, which are amongst the most frequent changes observed (and what many of my colleagues eventually default to using to identify vaccine injuries). Given that these signs, while very apparent, are “spiritual” in nature, I went back and forth on if I wanted to discuss them, and eventually felt it needed to be to a limited audience.
Children’s Health Defense embarked on a nine-month journey across America, gathering powerful testimonies from the people. Our interviews ranged from mothers and fathers to teenagers, families, medical professionals, whistleblowers, lawyers, and people from all walks of life.
What we discovered was nothing short of staggering. We listened to harrowing accounts of COVID hospital protocols that shook us to our very core. The consistency of these stories was alarming.
People also shared their experiences after taking the COVID-19 vaccine, revealing tragic outcomes of either death or serious injury. Now, fueled by these powerful firsthand testimonies, we are creating a documentary by the people, for the people.
Learn what we uncovered on the road. You can’t afford to miss it.
For best viewing, click here or click Toggle fullscreen on the PDF tool bar to make the PDF larger. On a mobile device, you should also rotate to landscape mode.